Related Experiment Video
Updated: May 8, 2026


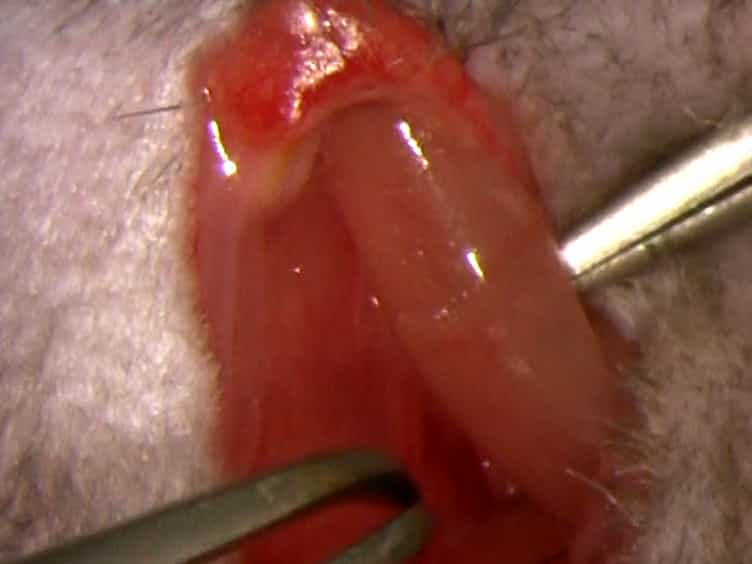
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Timing of arteriovenous fistula creation in patients With CKD: a decision analysis
Steven M Shechter1, M Reza Skandari1, Nadia Zalunardo2
1Sauder School of Business, University of British Columbia, Vancouver, Canada.

Insights
Optimal arteriovenous fistula (AVF) referral for chronic kidney disease (CKD) patients occurs within 12 months of anticipated dialysis. Referral timing should consider individual CKD progression rates and patient age to minimize unnecessary AVF creation.
Area of Science:
- Nephrology
- Vascular Surgery
- Health Economics
Background:
- The optimal timing for arteriovenous fistula (AVF) referral in patients with chronic kidney disease (CKD) remains unclear.
- Timely AVF referral may decrease reliance on central venous catheters (CVCs) for dialysis access.
Purpose of the Study:
- To determine the optimal timing for AVF referral in CKD patients.
- To compare AVF referral strategies based on time frames versus estimated glomerular filtration rate (eGFR) thresholds.
- To evaluate the impact of referral timing on CVC use, unnecessary AVF creation, and patient life expectancy.
Main Methods:
- A Monte Carlo simulation model was employed.
- The study analyzed patients with CKD followed in a multidisciplinary clinic, stratified by age.
- Decision analysis was used to model patient lifetime outcomes based on two referral strategies: a fixed time frame before anticipated hemodialysis or an eGFR threshold.
Main Results:
- Referral within a 12-18 month time frame before dialysis initiation generally yielded favorable outcomes, with approximately 34% incident CVCs and 14% unnecessary AVFs at 15 months.
- Referral at an eGFR threshold of 15-20 mL/min/1.73 m² resulted in lower rates of unnecessary AVFs (10-20%) but potentially higher CVC use.
- CKD progression rate and patient age significantly influenced optimal referral strategy; older patients and slower progressors benefited from later referral to reduce unnecessary AVF creation.
Conclusions:
- AVF referral approximately 12 months before anticipated dialysis initiation appears optimal among time-based strategies.
- Referral at an eGFR threshold below 15-20 mL/min/1.73 m² is effective for minimizing unnecessary AVFs.
- Individualized referral timing, considering CKD progression and patient age, is crucial, particularly for elderly CKD patients to avoid premature and potentially unused AVF creation.
Background:
The optimal time for arteriovenous fistula (AVF) referral is uncertain. Improving the timeliness of referral may reduce central venous catheter (CVC) use.
Study Design:
Monte Carlo simulation model.
Setting & Population:
Patients with chronic kidney disease (CKD) followed up in a multidisciplinary clinic, overall and stratified by age.
Model, Perspective, & Timeframe:
Decision analysis, patient, patient's lifetime.
Intervention:
AVF referral, using 1 of 2 strategies: refer when hemodialysis is anticipated to begin within a certain time frame or refer when estimated glomerular filtration rate (eGFR) drops below a certain threshold.
Outcomes:
A range of values for each strategy are compared to each other with respect to incident vascular access type (AVF or CVC), percentage of patients with an unnecessary AVF creation, and life expectancy after dialysis therapy initiation.
Results:
A 15-month referral time frame gave 34% with incident CVCs, 14% with unnecessary AVFs, and a life expectancy of 1,751 days. Time frames of 12-18 months performed similarly. Referral at eGFR of 20 mL/min/1.73 m(2) gave 38% with incident CVCs, 20% with unnecessary AVFs, and life expectancy of 1,742 days. Using an eGFR threshold of 15 mL/min/1.73 m(2), 10% had an unnecessary AVF. Policy performance was affected by CKD progression rate and age. For fast progressors (ΔeGFR = -7mL/min/1.73 m(2) per year), referral at eGFR of 25 mL/min/1.73 m(2) achieved a similar incident CVC percentage (~40%) as referral at 15 mL/min/1.73 m(2) in slower progressors (ΔeGFR = -2.78 mL/min/1.73 m(2) per year). For patients aged 70-80 and 80-90 years, time frames of 15-18 months yielded 16%-22% with unnecessary AVFs (vs 9%-11% in 50- to 60-year-olds); an eGFR threshold strategy of 20 mL/min/1.73 m(2) yielded 24% unnecessary AVFs in 80- to 90-year-olds versus 16% in 50- to 60-year-olds.
Limitations:
Our model does not consider patients with nonlinear CKD progression or acute kidney injury. We did not include arteriovenous grafts or consider cost or quality of life.
Conclusions:
In general, AVF referral within about 12 months of the estimated time to dialysis performed best among time frame strategies, and referral at eGFR < 15-20 mL/min/1.73 m(2) performed best among threshold strategies. The timing of referral should also be guided by the individual rate of CKD progression. Elderly patients with CKD could be referred later to reduce the risk of creating an AVF that is never used.

Related Concept Videos
 01:25
Hemodialysis I: Introduction
 01:20
Acute Kidney Injury V: Interprofessional Care
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:30
Continuous Renal Replacement Therapy
 01:24
Hemodialysis II: Procedure and Complications