Related Experiment Video
Updated: May 8, 2026


External Cephalic Version: Is it an Effective and Safe Procedure?
Published on: June 6, 2020
Do we need cephalic spread of spinal anaesthesia for caesarean section? A different approach to CSE-EVE for reducing
L K Fabris1, D Belci, K Š Zdravčević
1Department of Anaesthesia and ICU, General Hospital Pula, Pula, Croatia. lada1966@gmail.com

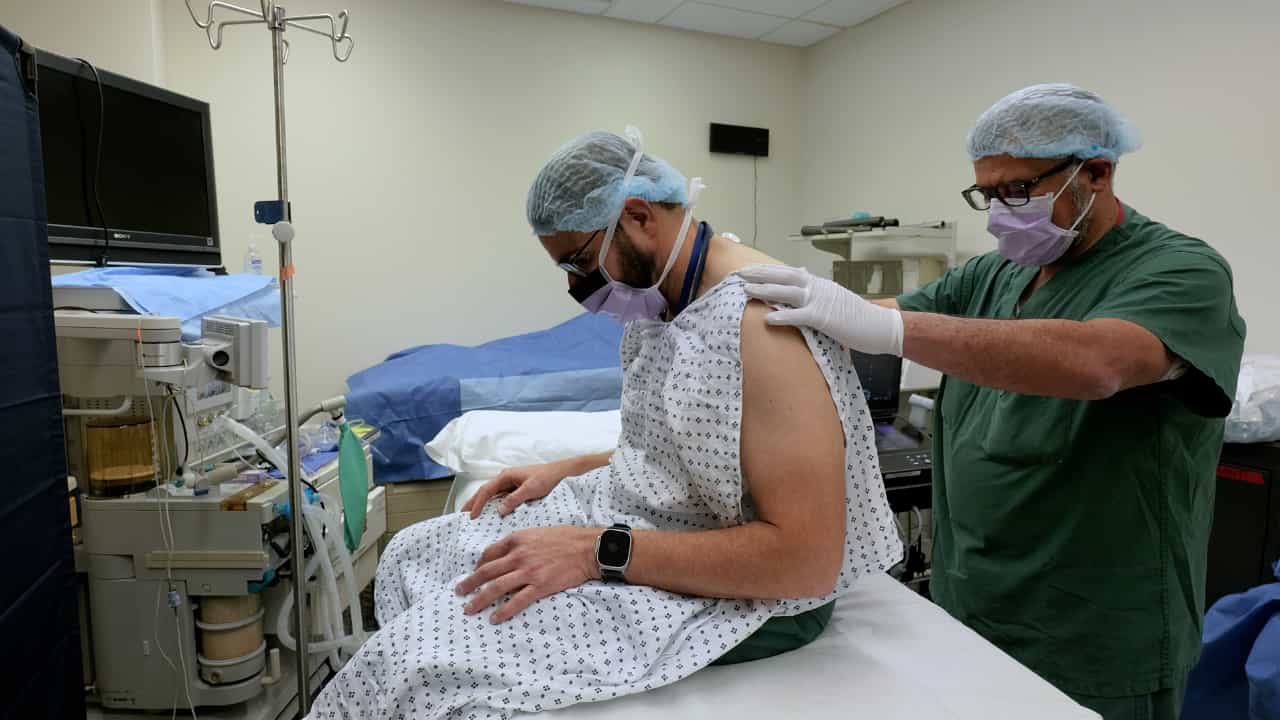
Spinal anaesthesia is the most preferred anaesthetic technique for elective as well as for unplanned Caesarean sections. Spinal-induced hypotension remains the most important side effect with a reported incidence between 20% and 100%. It can cause -maternal discomfort (nausea and vomiting) and impaired utero-placental perfusion. The present study was designed to examine the influence of epidural volume effect on the spread and duration of low-dose hyperbaric levobupivacaine. The aim of this study was to evaluate the influence of epidural restriction (injection of saline) on the distribution of anaesthesia as well as the incidence of hypotension during the spinal anaesthesia.After the approval by the ethics committee, 60 full-term parturient women (ASA I or II) with uncomplicated pregnancies were prospectively randomized into 2 groups: the SA group (single shot spinal anaesthesia) included 37 patients and the CSE-EVR group (combined spinal-epidural anaesthesia) included 39 patients in whom we induced the restriction of the spinal space by epidural volume compression. The blocks were performed at the L2/3 or L3/4 level in a sitting position, in the CSE-EVR group using the needle-through-needle technique. The initial dose for CSE-EVR was exactly half of the SA dose (0.5 mg per 10 cm height of hyperbaric levobupivacaine and 20 microg fentanyl). After spinal injection, an epidural catheter was located in the CSE-EVR and a volume of 20 mL saline solution injected. After injection, the women were turned supine with a left uterine displacement. Surgery was allowed when a sensory block at or above the T8 dermatome was established. We evaluated the height of the block by the pinprick method and the motor block by the Bromage scale, 10 min after spinal injection, during the operation time and at the end of surgery. Haemodynamic monitoring (NIBP, HR) was assessed every 2 min until the childbirth, then every 5 min during operative time. Anaesthetic efficacy was evaluated for breakthrough pain by visual analogue pain score (VAPS), Apgar score at birth, umbilical artery pH, and epinephrine consumption.The level of anaesthesia 10 min after the induction was significantly higher in the spinal group (SA) than in the CSE-EVR T5 (T4-T7) vs. T7 (T6-T8) group.The SA group experienced complete motor block during the time of anaesthesia, while the CSE-EVR group demonstrated significantly faster motor recovery. The incidence of hypotension and ephedrine supplementation was significantly lower in the CSE-EVR group (19 vs. 35 patients) than in the SA group (p<0.05).The neonatal outcome and umbilical artery pH were higher in the CSE-EVR group. Both groups were comparable in demographic data, VAS scores, preloading and infusion volume, atropine or ephedrine use, and adverse effects such as nausea or skin pruritus.We demonstrated a possible restriction of the spread of spinal anaesthesia by using epidural volume restriction with 20 mL saline as part of a combined spinal epidural technique. The study shows that CSE with EVR using only 50% of the levobupivacaine dose provided adequate anaesthesia for elective Caesarean delivery, as well as better maternal haemodynamic stability.
Spinal anaesthesia is the most preferred anaesthetic technique for elective as well as for unplanned Caesarean sections. Spinal-induced hypotension remains the most important side effect with a reported incidence between 20% and 100%. It can cause -maternal discomfort (nausea and vomiting) and impaired utero-placental perfusion. The present study was designed to examine the influence of epidural volume effect on the spread and duration of low-dose hyperbaric levobupivacaine. The aim of this study was to evaluate the influence of epidural restriction (injection of saline) on the distribution of anaesthesia as well as the incidence of hypotension during the spinal anaesthesia.After the approval by the ethics committee, 60 full-term parturient women (ASA I or II) with uncomplicated pregnancies were prospectively randomized into 2 groups: the SA group (single shot spinal anaesthesia) included 37 patients and the CSE-EVR group (combined spinal-epidural anaesthesia) included 39 patients in whom we induced the restriction of the spinal space by epidural volume compression. The blocks were performed at the L2/3 or L3/4 level in a sitting position, in the CSE-EVR group using the needle-through-needle technique. The initial dose for CSE-EVR was exactly half of the SA dose (0.5 mg per 10 cm height of hyperbaric levobupivacaine and 20 microg fentanyl). After spinal injection, an epidural catheter was located in the CSE-EVR and a volume of 20 mL saline solution injected. After injection, the women were turned supine with a left uterine displacement. Surgery was allowed when a sensory block at or above the T8 dermatome was established. We evaluated the height of the block by the pinprick method and the motor block by the Bromage scale, 10 min after spinal injection, during the operation time and at the end of surgery. Haemodynamic monitoring (NIBP, HR) was assessed every 2 min until the childbirth, then every 5 min during operative time. Anaesthetic efficacy was evaluated for breakthrough pain by visual analogue pain score (VAPS), Apgar score at birth, umbilical artery pH, and epinephrine consumption.The level of anaesthesia 10 min after the induction was significantly higher in the spinal group (SA) than in the CSE-EVR T5 (T4-T7) vs. T7 (T6-T8) group.The SA group experienced complete motor block during the time of anaesthesia, while the CSE-EVR group demonstrated significantly faster motor recovery. The incidence of hypotension and ephedrine supplementation was significantly lower in the CSE-EVR group (19 vs. 35 patients) than in the SA group (p<0.05).The neonatal outcome and umbilical artery pH were higher in the CSE-EVR group. Both groups were comparable in demographic data, VAS scores, preloading and infusion volume, atropine or ephedrine use, and adverse effects such as nausea or skin pruritus.We demonstrated a possible restriction of the spread of spinal anaesthesia by using epidural volume restriction with 20 mL saline as part of a combined spinal epidural technique. The study shows that CSE with EVR using only 50% of the levobupivacaine dose provided adequate anaesthesia for elective Caesarean delivery, as well as better maternal haemodynamic stability.
More Related Videos

Related Concept Videos
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...
 01:30
Local Anesthetics: Clinical Application as Surface, Infiltration, and Conduction Block Anesthesia
 01:24
Parenteral Anesthetics: Overview