Related Experiment Video
Updated: May 7, 2026
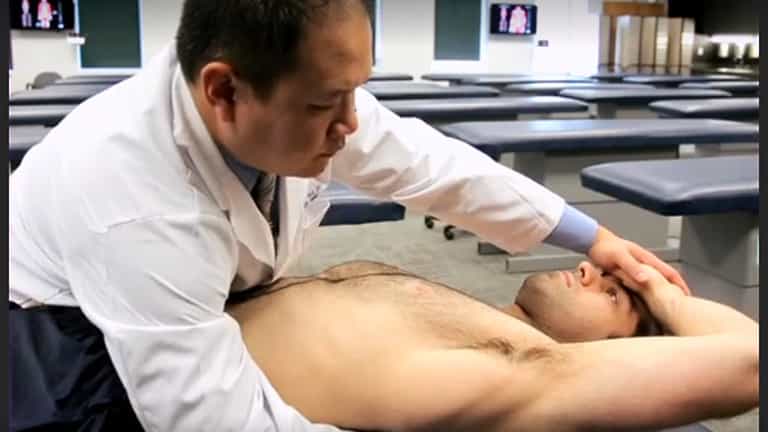

Osteopathic Manipulative Treatment as a Useful Adjunctive Tool for Pneumonia
Published on: May 6, 2014
Obesity and overweight as a risk factor for pneumonia in polytrauma patients: a retrospective cohort study
Ladislav Mica1, Catharina Keller, Jindřich Vomela
1From the Division of Trauma Surgery (L.M., M.P.), and Department of Trauma Surgery (O.T.), University Hospital of Zürich, Zürich; and University Hospital of Othopedic Surgery (M.J.K.), Inselspital Bern, Bern, Switzerland; Department of Neurology (C.K.), University Hospital of Cologne, Cologne, Germany; and Department of Thoracic Surgery (J.V.), University Hospital of Brno, Czech Republic.

Background:
Obesity is a growing problem in western societies. The aim of this retrospective cohort study was to determine the association between the overweight and obese polytrauma patients and pneumonia after injury.
Methods:
A total of 628 patients with an Injury Severity Score (ISS) of 16 or greater and 16 years or older were included in this retrospective study. The sample was subdivided into three groups as follows: body mass index (BMI) of less than 25 kg/m2; BMI of 25 kg/m2 to 30 kg/m2; and BMI more than 30 kg/m2. The Murray score was assessed at admission and at its maximum during hospitalization to determine pulmonary problems. Pneumonia was defined as bacteriologically positive sputum with appropriate radiologic and laboratory changes (C-reactive protein and interleukin 6). Data are given as mean ± SEM. One-way analysis of variance and the Kruskal-Wallis test were used for the analyses, and the significance level was set at p < 0.05; Bonferroni-Dunn test was performed as post hoc analysis.
Results:
The Abbreviated Injury Scale (AIS) score for the thorax was 3.2 ± 0.1 in the group with a BMI of less than 25 kg/m2, 3.3 ± 0.1 in the group with a BMI of 25 kg/m2 to 30 kg/m2, and 2.8 ± 0.2 in the group with BMI of more than 30 kg/m2 (p = 0.044). The Murray score at admission was elevated with increasing BMI (0.8 ± 0.8 for BMI < 25 kg/m2, 0.9 ± 0.9 for BMI 25–30 kg/m2, and 1.0 ± 0.8 for BMI > 30 kg/m2; p = 0.137); the maximum Murray score during hospitalization revealed significant differences (1.2 ± 0.9 for BMI < 25 kg/m2, 1.6 ± 1.0 for BMI 25–30 kg/m2, and 1.5 ± 0.9 for BMI > 30 kg/m2; p < 0.001). The incidence of pneumonia also increased with increasing BMI (1.6% for BMI < 25 kg/m2, 2.0% for BMI 25–30 kg/m2, and 3.1% for BMI > 30 kg/m2; p = 0.044).
Conclusion:
Obesity leads to an increased incidence of pneumonia in a polytrauma situation.
Level Of Evidence:
Prognostic/epidemiologic study, level IV.
Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:29
Pneumonia I: Introduction
 01:30
Pneumonia III: Complications and Assessment
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed.
 01:08
Pneumothorax II: Pathophysiology
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include: