Related Experiment Video
Updated: May 7, 2026
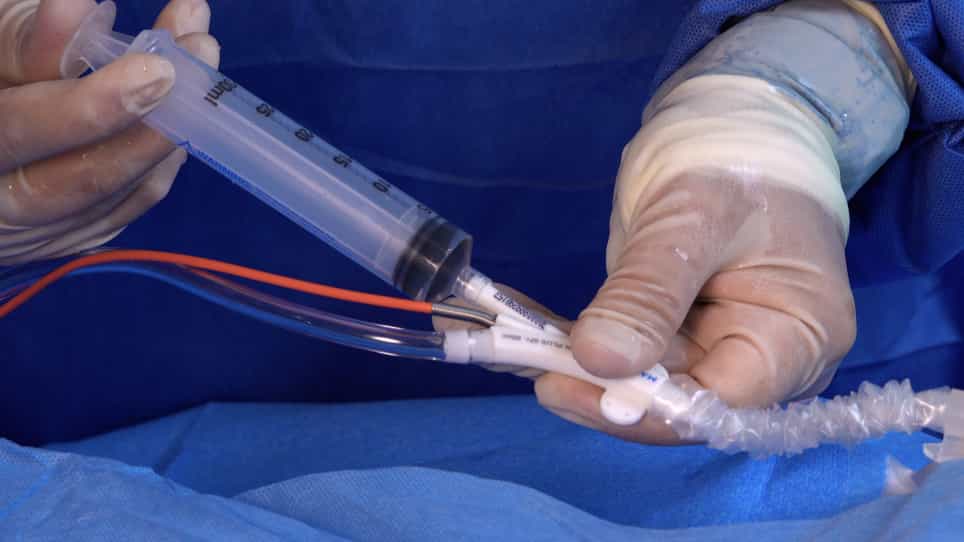
The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Have we given up on intra-aortic balloon counterpulsation in post-myocardial infarction cardiogenic shock?
Subasit Acharji1, Atish Mathur, Umashankar Lakshmanadoss
1Division of Cardiology, Robert Packer Hospital, Guthrie Health Services, Sayre, Pennsylvania.

Insights
The IABP-SHOCK II trial found intra-aortic counterpulsation (IACP) ineffective for cardiogenic shock (CS) post-myocardial infarction (MI). However, methodological limitations suggest IACP may still benefit select patients, especially younger ones, before or during percutaneous coronary intervention.
Area of Science:
- Cardiology
- Interventional Cardiology
- Critical Care Medicine
Background:
- The Intra-aortic Balloon Pump in Cardiogenic Shock II (IABP-SHOCK II) trial questioned the efficacy of intra-aortic counterpulsation (IACP) in acute myocardial infarction (AMI) patients with cardiogenic shock (CS).
- The trial's findings led to a downgrade in IACP recommendations by organizations like the European Society of Cardiology for post-AMI CS.
- Significant methodological shortcomings in the IABP-SHOCK II trial necessitate a re-evaluation of IACP's role in managing CS.
Purpose of the Study:
- To critically analyze the IABP-SHOCK II trial's methodology and conclusions regarding IACP in CS complicating AMI.
- To reassess the indications and optimal timing for IACP initiation in hemodynamically compromised AMI patients.
- To advocate for IACP's continued role as a first-line mechanical circulatory support in specific AMI patient populations.
Main Methods:
- Review and critique of the IABP-SHOCK II trial's design, patient selection, intervention timing, and outcome adjudication.
- Analysis of subgroup data, particularly concerning the impact of IACP on mortality in younger patients.
- Comparison of IACP initiation timing (pre-PCI, during PCI, post-PCI) and its potential influence on outcomes.
Main Results:
- The IABP-SHOCK II trial reported no significant reduction in 30-day mortality with IACP in the overall CS patient cohort.
- A high percentage of patients in the IABP-SHOCK II trial received IACP post-percutaneous coronary intervention (PCI) or did not receive it.
- A potential survival benefit of IACP was observed in younger patients within the trial cohort.
Conclusions:
- The IABP-SHOCK II trial's conclusions should not be generalized due to its focus on post-PCI IACP and methodological limitations.
- Intra-aortic counterpulsation (IACP) should remain the primary mechanical circulatory support for hemodynamically unstable AMI patients undergoing primary PCI.
- Consideration for early escalation to advanced mechanical support is crucial for patients with refractory CS despite revascularization and IACP.
Abstract:
The recently published Intra-aortic Balloon Pump in Cardiogenic Shock II (IABP-SHOCK II) trial concluded that intra-aortic counterpulsation (IACP) does not reduce 30-day mortality in patients with cardiogenic shock (CS) complicating acute myocardial infarction (AMI) for whom early revascularization strategy was planned. The study resulted in downgrading IACP in post-AMI CS patients by certain professional organizations like the European Society of Cardiology. Although this is the largest and most important CS study of this decade, it suffers from considerable shortcomings: (1) time intervals from chest-pain onset or AMI recognition to revascularization, enrollment, and IACP initiation are not disclosed; (2) 86.6% of the treatment arm initiated IACP only post-percutaneous coronary intervention (PCI), and 4.3 % did not receive IACP at all; (3) 17.4% of the control arm crossed over to IACP or other mechanical support, mostly due to protocol violations; (4) there is no adjudication of the mortality events; (5) follow-up is limited to 30 days; and (5) both methodology (especially IACP device size) and quality of IACP are not evaluated and documented. Because the study assessed mostly the efficacy and safety of IACP initiated post-PCI, the study conclusions should not be extrapolated to IACP pre-PCI or during PCI in CS. Moreover, IACP had a favorable effect on the mortality of younger patients. Intra-aortic counterpulsation should remain the first line of mechanical circulatory support for the hemodynamically compromised AMI patients with or without CS who are undergoing primary PCI. Early upgrade to more advanced mechanical circulatory support should be considered for selective suitable candidates who remain in refractory CS despite revascularization and IACP.
More Related Videos
 06:10
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
 07:39
Use of a Percutaneous Ventricular Assist Device/Left Atrium to Femoral Artery Bypass System for Cardiogenic Shock
Published on: August 16, 2021
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Heart Failure VI: Adjunct Therapies
 01:28
Acute Coronary Syndrome IV: Interprofessional Care