Related Experiment Video
Updated: May 7, 2026


High-Throughput Cardiotoxicity Screening Using Mature Human Induced Pluripotent Stem Cell-Derived Cardiomyocyte Monolayers
Published on: March 24, 2023
hERG inhibitors with similar potency but different binding kinetics do not pose the same proarrhythmic risk:
Giovanni Y DI Veroli1, Mark R Davies, Henggui Zhang
1Institute of Cardiovascular Sciences, University of Manchester, Manchester, UK; Translational Safety, Drug Safety & Metabolism, AstraZeneca, Manchester, UK.

Introduction:
Since the discovery of the link that exists between drug-induced hERG inhibition and Torsade de Pointes (TdP), extreme attention has been given to avoid new drugs inhibiting this channel. hERG inhibition is routinely screened for in new drugs and, typically, IC50 values are compared to projected plasma concentrations to define a safety margin.
Methods And Results:
We aimed to show that drugs with similar hERG potency are not uniformly pro-arrhythmic-this depends on the drug binding kinetics and mode of action (trapped or not) rather than the IC50 value only. We used a mathematical model of hERG and its related encoded current IKr to simulate drug binding in different configurations. Expression systems mimicking the screening process were first investigated. hERG model was then incorporated into a canine action potential (AP) and tissue model to study the impact of drug binding configurations on AP and pseudo-ECG (QT interval prolongation). Our data show that: (1) trapped and not trapped configurations and different binding kinetics could be identified during hERG screening; (2) slow binding, not trapped drugs, induced less AP prolongation and minimal QT interval prolongation (4.7%) at a concentration equal to the IC50 whereas maximal pro-arrhythmic risk was observed for trapped drugs at the same concentration (QT interval prolongation, 23.1%).
Conclusion:
Our study demonstrates the need for screening for hERG binding configurations rather than potency alone. It also demonstrates the potential link between hERG, drug mode of action and TdP, and the need to question the current regulatory guidance.
More Related Videos


Related Concept Videos
 01:24
Antiarrhythmic Drugs: Class II Agents as β-Adrenergic Blockers
 01:12
Antiarrhythmic Drugs: Class III Agents as Potassium Channel Blockers
 01:22
Antiarrhythmic Drugs: Class I Agents as Sodium Channel Blockers
Class 1A Antiarrhythmic Drugs: These drugs work by moderately blocking sodium channels,...
 01:22
Dose-Response Relationship: Potency and Efficacy
 01:29
Drug-Receptor Interactions
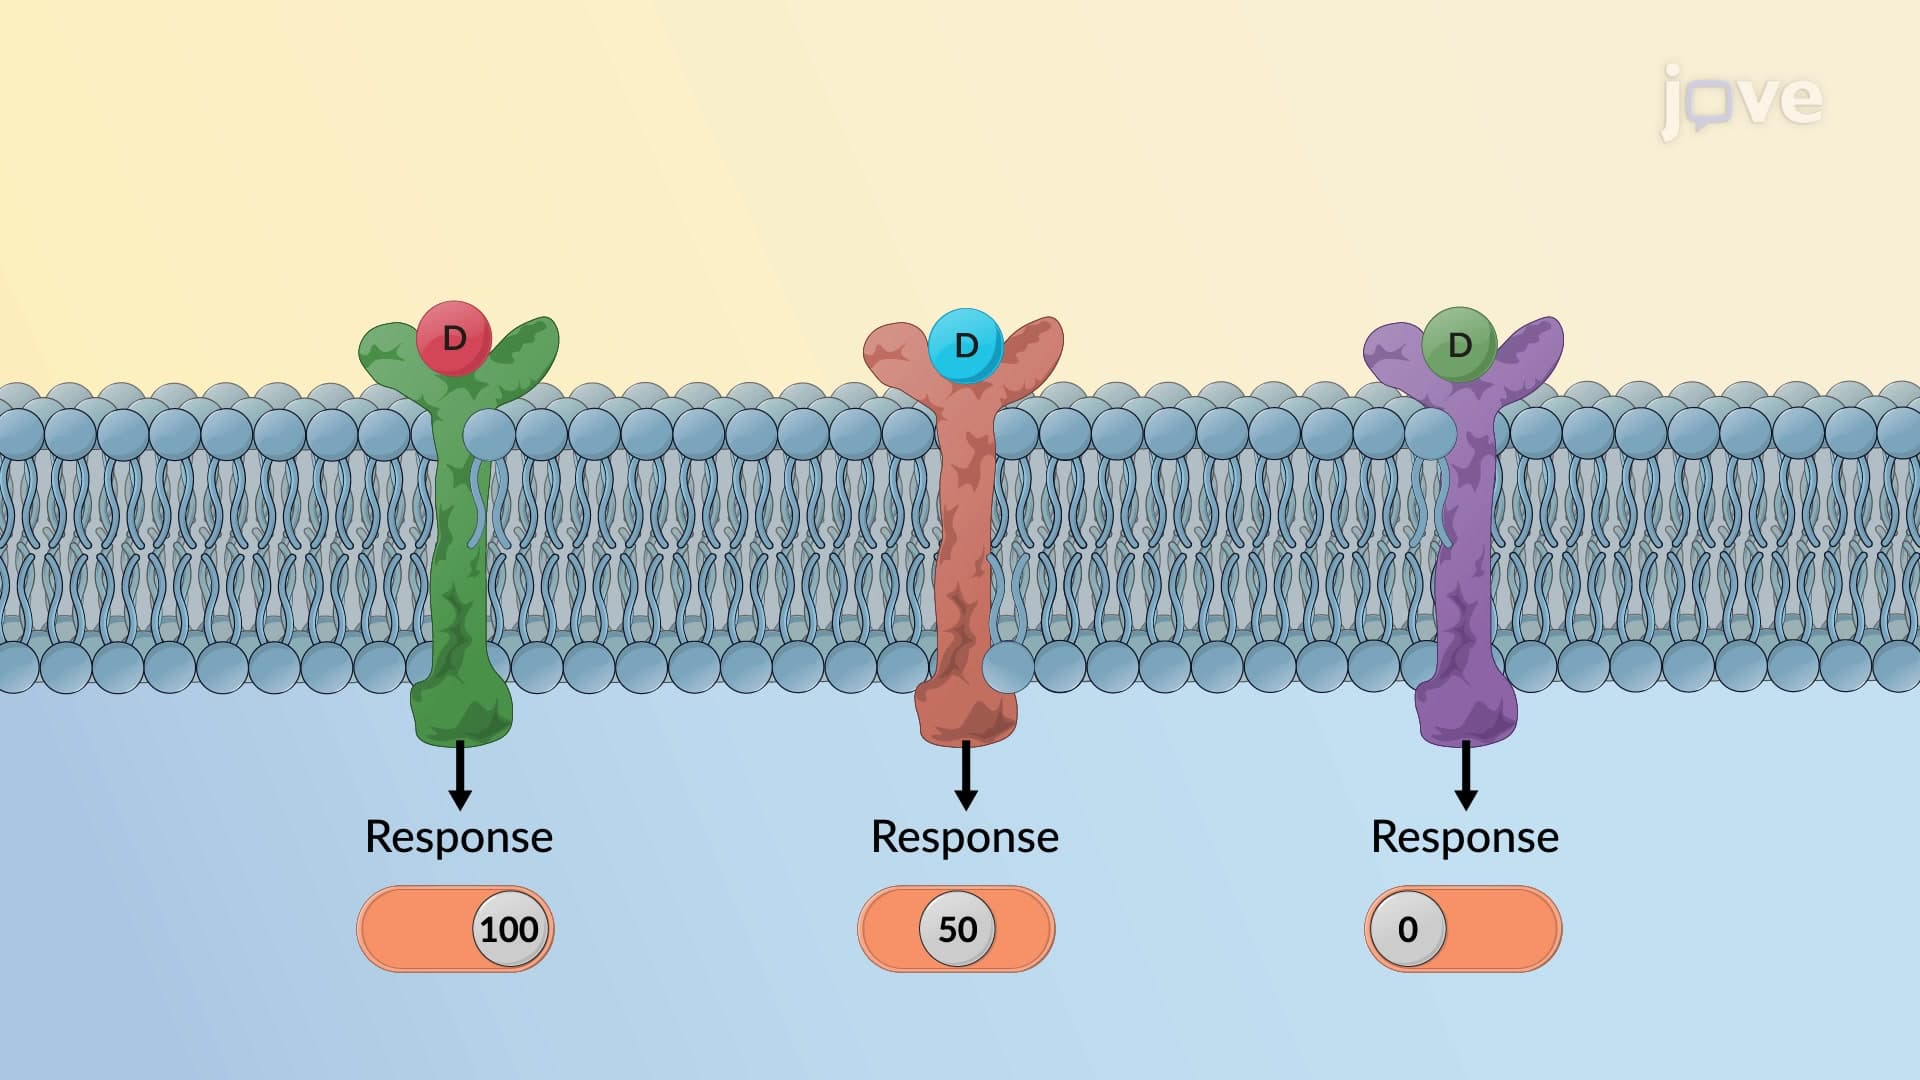
Several parameters, such as the drug's affinity for its receptor and its efficacy, which is its ability to activate the receptor, determine the drug's effect on the tissue....
 01:25
Pharmacokinetics: Drug–Drug Interactions