Related Experiment Video
Updated: May 6, 2026


Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Totally endoscopic congenital heart surgery compared with the traditional heart operation in children
Yunge Cheng1, Huaidong Chen, Wener Mohl
1Department of Cardiovascular Surgery, Shanghai Yodac Cardio-thoracic Hospital, 201900, Shanghai, China.

Insights
Totally endoscopic heart surgery in children is safe and effective for congenital heart diseases. This minimally invasive approach offers comparable or better outcomes than conventional surgery, with reduced complications and shorter hospital stays.
Area of Science:
- Pediatric Cardiac Surgery
- Minimally Invasive Cardiac Surgery
- Congenital Heart Disease Treatment
Background:
- Conventional open-heart surgery for congenital heart diseases (CHDs) in children involves median sternotomy.
- Minimally invasive techniques are being explored to improve outcomes and reduce morbidity.
Purpose of the Study:
- To compare the efficacy and safety of totally endoscopic surgery versus conventional surgery for CHDs in pediatric patients.
- To determine if endoscopic surgery offers advantages in terms of outcomes, complications, and recovery time.
Main Methods:
- A study involving 708 children with CHDs, divided into endoscopic and conventional surgery groups.
- Endoscopic procedures utilized peripheral cardiopulmonary bypass and transthoracic aortic cross-clamp via three 1-2 cm intercostal ports.
- Conventional group underwent traditional median sternotomy.
Main Results:
- No hospital mortality in either group. Endoscopic surgery had a 98.5% success rate with fewer major postoperative complications (2.3% vs 5.1%).
- Endoscopic procedures showed significantly shorter intensive care unit (ICU) stay, reduced postoperative drainage, and shorter overall hospital time.
- While operation duration was longer in the endoscopic group, key bypass and cross-clamp times were comparable or shorter.
Conclusions:
- Totally endoscopic closed-chest surgery is a feasible and safe option for pediatric congenital heart disease.
- Endoscopic surgery demonstrated superior outcomes, including reduced blood product usage and shorter hospital stays, compared to conventional sternotomy.
- High patient satisfaction with cosmetic results and comfort suggests endoscopic surgery will be a preferred choice for select CHD patients.
Objective:
Totally endoscopic surgery compared with the conventional heart operation in children is described in this article to find a preferable treatment for congenital heart diseases.
Methods:
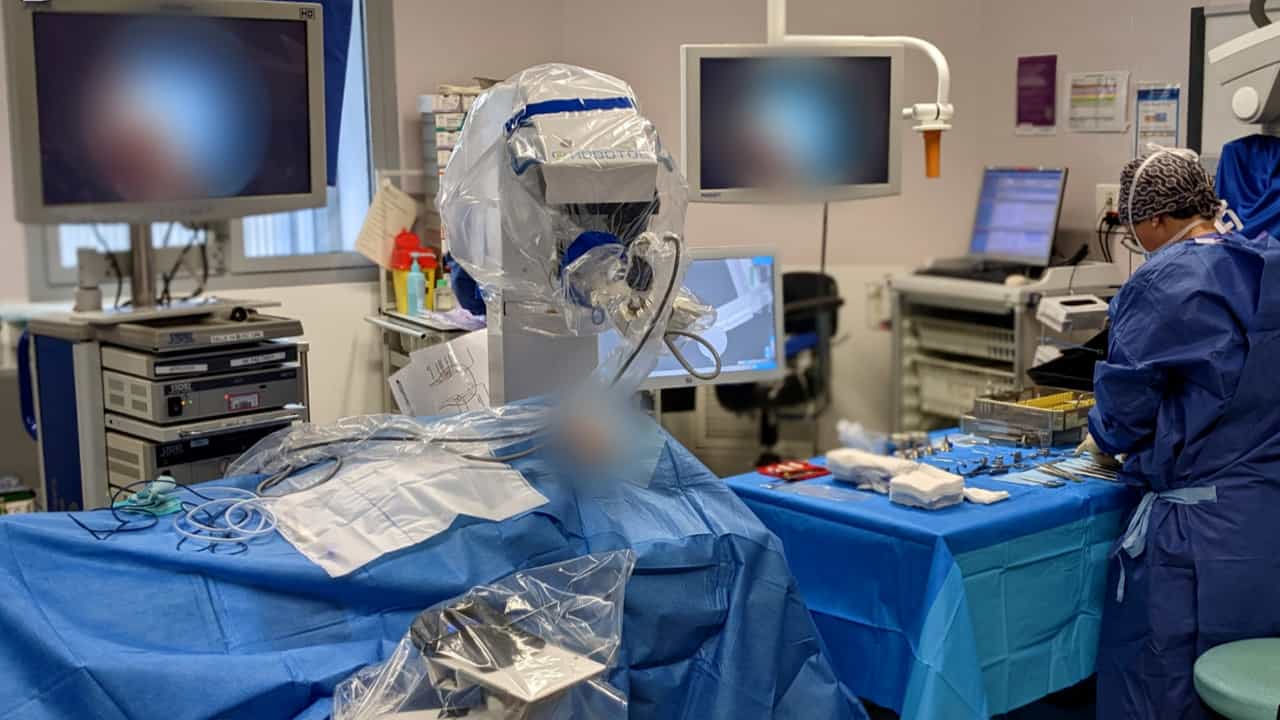
Between May 2000 and December 2007, 708 children with congenital heart disease were divided into two groups: endoscopic group and conventional group. For the endoscopic group, all children underwent total endoscopic procedures with peripheral cardiopulmonary bypass, transthoracic aortic cross-clamp, and antegrade cardioplegia, whereas for the conventional group, all children were operated in traditional way. Three 1-2-cm intercostal ports in the right chest were used for access in the endoscopic group. The intrathoracic part of the operation was performed completely under two-dimensional video, using conventional instruments. Directly closureed of the atrial septal defect was performed in 74 cases, patch closureed of the atrial septal defect in 48 cases, directly closureed of the ventricular septal defect in 158 cases, patch closureing of the ventricular septal defect in 116 cases. For the conventional group, all operations were done with traditional median sternotomy. Directed closureing of the atrial septal defect was performed in 38 cases, patch closed of the atrial septal defect in 56 cases, directly closureed of the ventricular septal defect in 76 cases, patch closureed of the ventricular septal defect in 142 cases.
Results:
There was no hospital mortality in both groups. For the endoscopic group, operations were performed successfully in 390 (98.5 %) patients, enlarging a port to a 5-cm incision in 4 children. Reoperation was necessary in two children, and no conversion to median sternotomy incision was necessary. The mean duration of operation was 132 ± 48 min, and cardiopulmonary bypass and aortic cross-clamp times were 54 ± 16 min and 25 ± 8 min, respectively. Major postoperative complications occurred in nine (2.3 %, p < 0.05) cases. For the conventional group, all children were operated by median sternotomy, and the mean duration of operation was 118 ± 41 min (p < 0.05); cardiopulmonary bypass and aortic cross-clamp times were 51 ± 13 min and 21 ± 6 min (p < 0.05), respectively. Major postoperative complications occurred in 16 (5.1 %) cases. Also, the intensive care unit stay time (8.3 ± 2.8 h versus 8.9 ± 2.9 h, p < 0.01), postoperative drainage (120 ± 21 ml versus 433 ± 140 ml, p < 0.05), and hospital time (8.6 ± 1.8 days versus 11.5 ± 1.9 days, p < 0.05) were statistically different.
Conclusions:
Totally endoscopic closed chest congenital heart surgery in children was feasible and safe. The results were similar or even superior to the traditional operations due to the decreased use of blood products and shortened hospital time. Degree of satisfaction with cosmetic result and postoperative comfort were very high. Therefore, endoscopic surgery will become a new popular choice for some congenital heart disease patients in the future.