Related Experiment Video
Updated: May 6, 2026
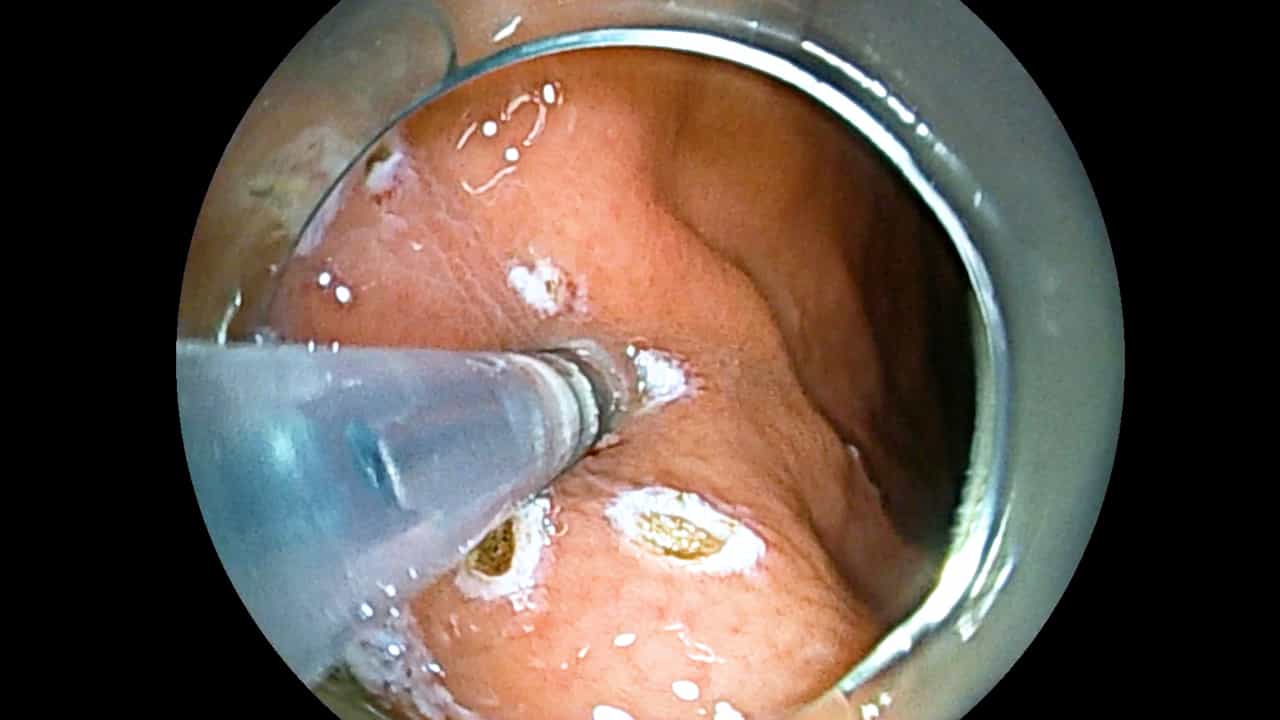
Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
An upper gastrointestinal ulcer still bleeding after endoscopy: what comes next?

Introduction:
Recurrent bleeding from an upper gastrointestinal ulcer when endoscopy fails is a reason for radiological or surgical treatment, both of which have their advantages and disadvantages.
Case:
Based on a patient with recurrent gastrointestinal bleeding, we reviewed the available evidence regarding the efficacy and safety of surgical treatment and embolisation, respectively.
Discussion:
Transarterial embolisation (TAE) and surgical treatment are both options for recurrent gastrointestinal bleeding when endoscopy fails. Both therapies have serious complications and a risk of rebleeding. Choosing the therapy depends on the capability of the patient to tolerate haemodynamic instability, resuscitation and hypotension.
Conclusion:
Choosing between TAE and surgery depends a great deal on the case presented, haemodynamic stability and the skills and tools available at that moment.

Related Concept Videos
 01:27
Peptic Ulcer
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications