Related Experiment Video
Updated: May 6, 2026
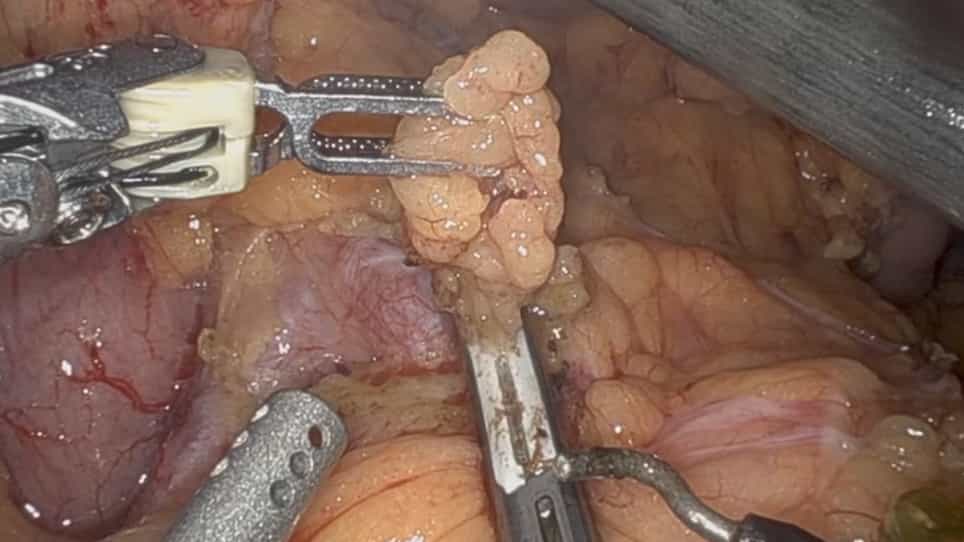

Robot Assisted Distal Pancreatectomy with Celiac Axis Resection DP-CAR for Pancreatic Cancer: Surgical Planning and Technique
Published on: August 14, 2021
Defining optimum treatment of patients with pancreatic adenocarcinoma using regret-based decision curve analysis
Jonathan M Hernandez1, Athanasios Tsalatsanis, Leigh Ann Humphries
1*Department of Surgery, Division of General Surgery, University of South Florida, Tampa, FL †Center for Evidence-Based Medicine, University of South Florida, Tampa, FL ‡Department of Internal Medicine, Division of Evidence-Based Medicine, Tampa, FL §Department of Hematology and Health Outcomes and Behavior, H. Lee Moffitt Cancer Center & Research Institute, Tampa, FL.

Objective:
To use regret decision theory methodology to assess three treatment strategies in pancreatic adenocarcinoma.
Background:
Pancreatic adenocarcinoma is uniformly fatal without operative intervention. Resection can prolong survival in some patients; however, it is associated with significant morbidity and mortality. Regret theory serves as a novel framework linking both rationality and intuition to determine the optimal course for physicians facing difficult decisions related to treatment.
Methods:
We used the Cox proportional hazards model to predict survival of patients with pancreatic adenocarcinoma and generated a decision model using regret-based decision curve analysis, which integrates both the patient's prognosis and the physician's preferences expressed in terms of regret associated with a certain action. A physician's treatment preferences are indicated by a threshold probability, which is the probability of death/survival at which the physician is uncertain whether or not to perform surgery. The analysis modeled 3 possible choices: perform surgery on all patients; never perform surgery; and act according to the prediction model.
Results:
The records of 156 consecutive patients with pancreatic adenocarcinoma were retrospectively evaluated by a single surgeon at a tertiary referral center. Significant independent predictors of overall survival included preoperative stage [P = 0.005; 95% confidence interval (CI), 1.19-2.27], vitality (P < 0.001; 95% CI, 0.96-0.98), daily physical function (P < 0.001; 95% CI, 0.97-0.99), and pathological stage (P < 0.001; 95% CI, 3.06-16.05). Compared with the "always aggressive" or "always passive" surgical treatment strategies, the survival model was associated with the least amount of regret for a wide range of threshold probabilities.
Conclusions:
Regret-based decision curve analysis provides a novel perspective for making treatment-related decisions by incorporating the decision maker's preferences expressed as his or her estimates of benefits and harms associated with the treatment considered.

Related Concept Videos
 01:21
Cancer Survival Analysis
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:24
Kaplan-Meier Approach