Fecal incontinence, sexual complaints, and anorectal function after third-degree obstetric anal sphincter injury (OASI): 5-year follow-up
Related Experiment Video
Updated: May 6, 2026

Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
A P Visscher1, T J Lam, N Hart
1Department of Gastroenterology and Hepatology, VU University Medical Center, Amsterdam, The Netherlands, ap.visscher@vumc.nl.

Introduction And Hypothesis:
Our aim was to evaluate alterations in anorectal function after anal sphincteroplasty for third-degree obstetric anal sphincter injury (OASI) in relation to clinical outcome.
Methods:
In this retrospective, descriptive, cross-sectional study conducted between 1998 and 2008, women with persisting fecal incontinence (FI) after 3a OASI and all women with grade 3b or 3c OASI were sent for anorectal function evaluation (AFE) consisting of anal manometry and endosonography 3 months after sphincteroplasty. In 2011, questionnaires regarding FI (Vaizey/Wexner), urinary incontinence (UI) [International Consultation on Incontinence Questionnaire Short Form (ICIQ-SF)], sexual function [Female Sexual Function Index (FSFI)], and quality of life (QOL) (Rand-36) were sent and women were asked to undergo additional AFE.
Results:
Sixty-six women underwent AFE. Mean follow-up was 5.0 years. Forty (61%) patients returned questionnaires regarding FI and UI. Prevalence of FI was 63% flatus, 50% liquid stool, and 20% solid stool. Thirty-two of 40 also reported on QOL and SF. Sexual dysfunction was present in the majority of women (cutoff value 26.55) and more pronounced in larger OASI. Sixteen of 40 women underwent additional AFE. Women with combined internal (IAS) and external (EAS) anal sphincter injury (n = 6) had worse FI (P < 0.050) and lower anal pressures (P = 0.040) than women with isolated EAS injury (n = 10).
Conclusion:
Follow-up after third-degree OASI suggests poor anorectal and sexual function. Women with combined external and internal OASI show more deterioration in anorectal function and experience worse FI. Therefore, special attention should be paid to these women in order to mitigate these symptoms later in life.


Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:26
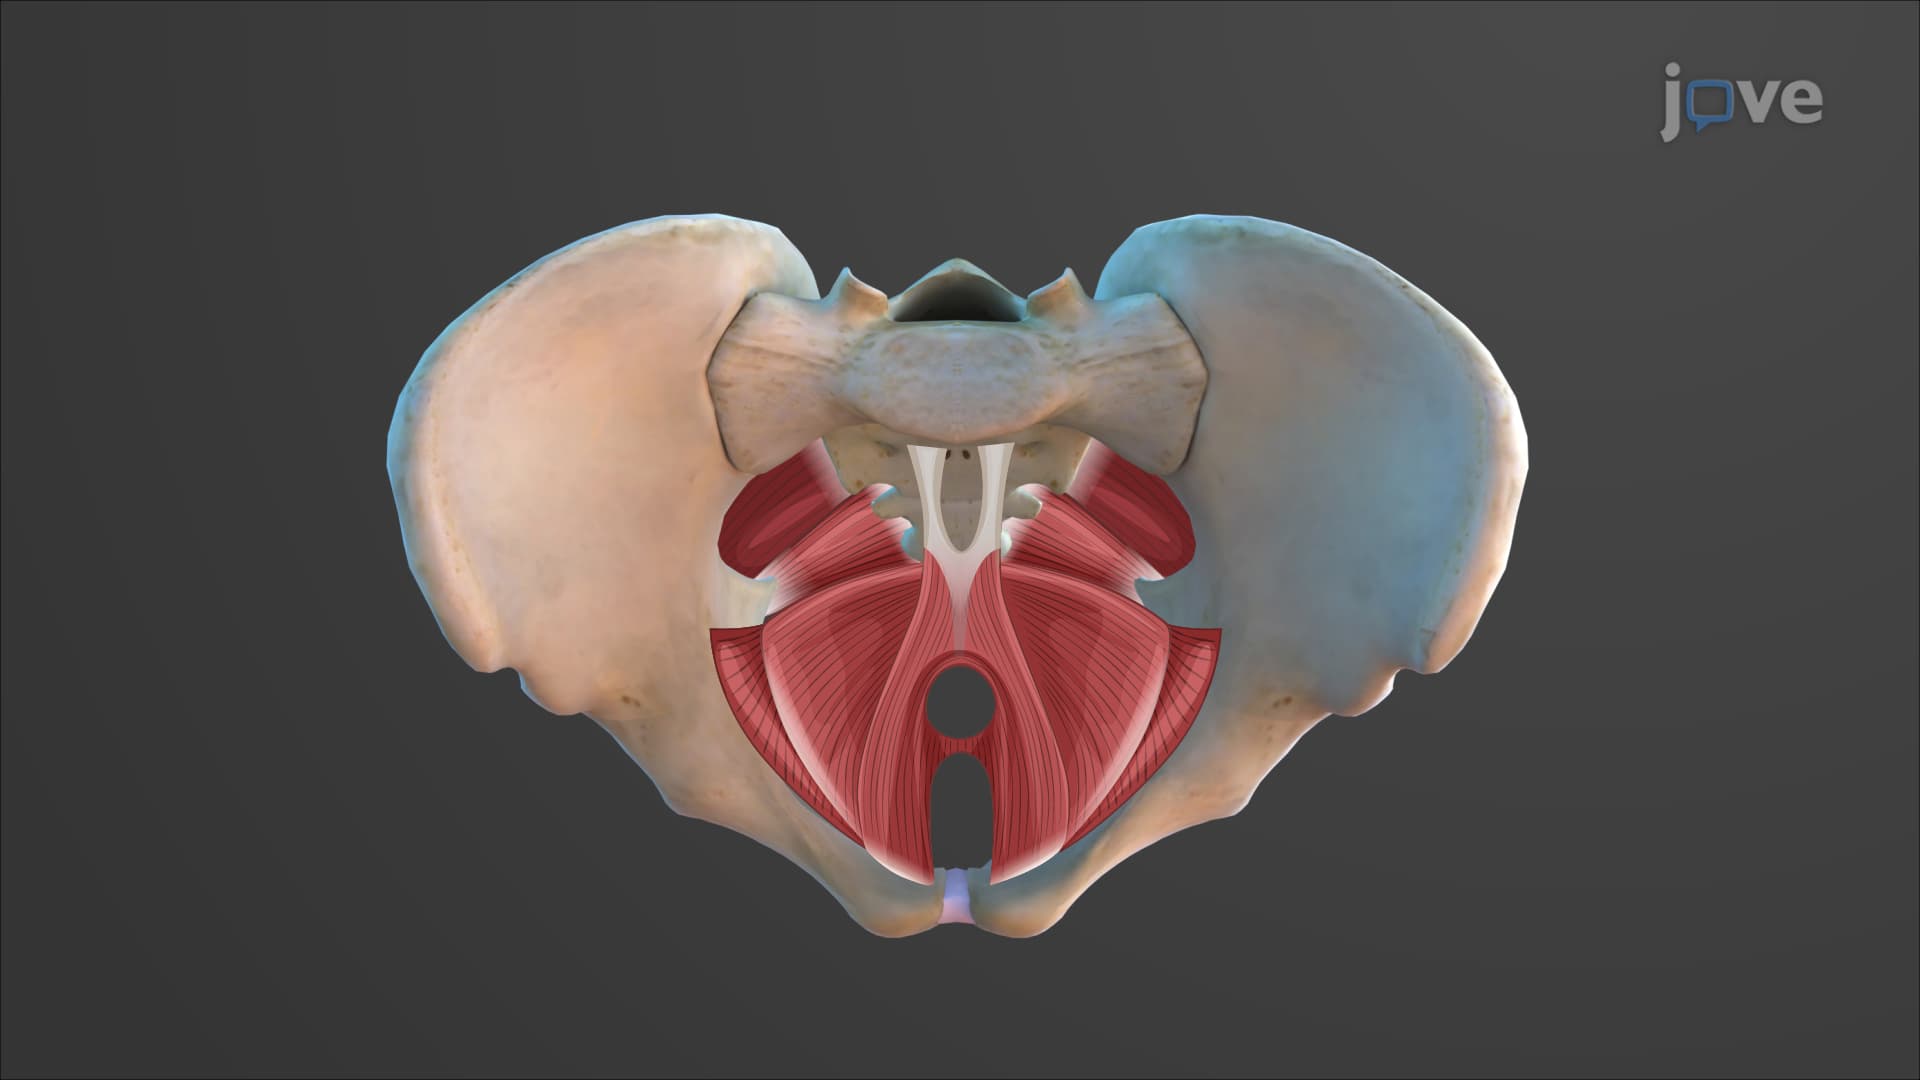
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...