Related Experiment Video
Updated: May 5, 2026


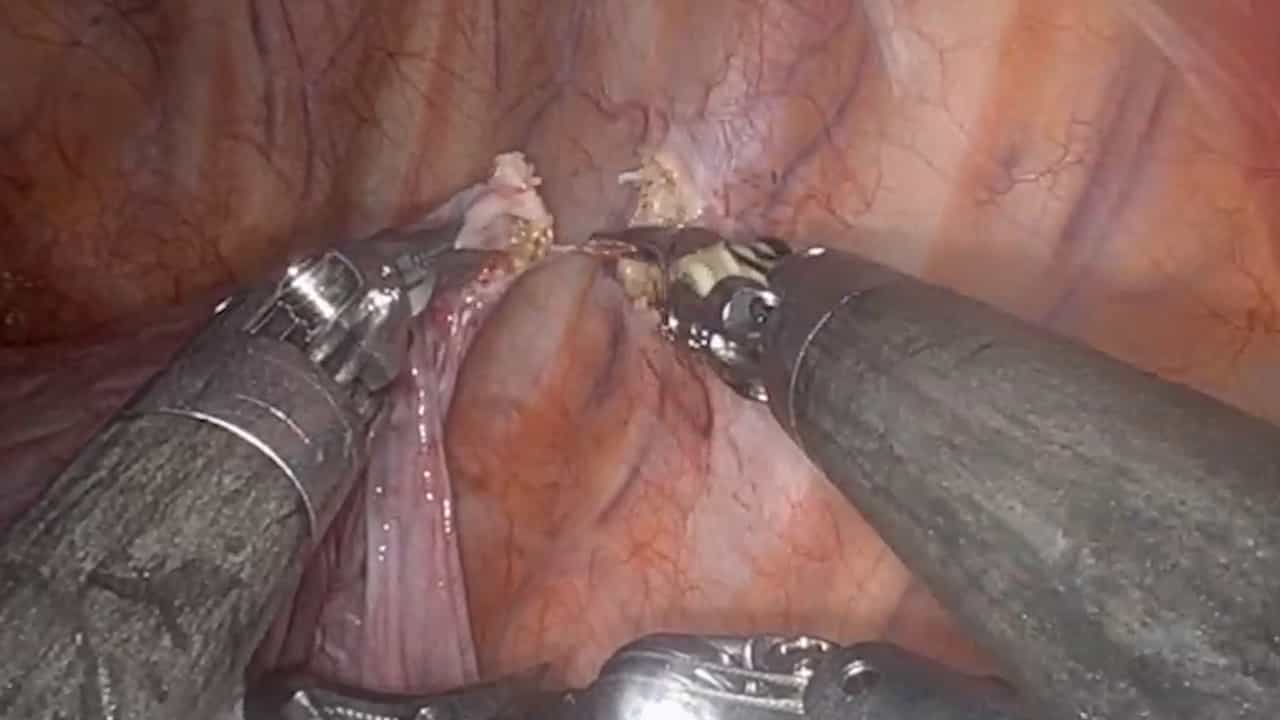
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Transitioning from video-assisted thoracic surgical lobectomy to robotics for lung cancer: are there outcomes
Benjamin E Lee1, Robert J Korst1, Elaine Kletsman1
1Daniel and Gloria Blumenthal Cancer Center, Paramus, NJ; Division of Thoracic Surgery, Department of Surgery, The Valley Hospital/Valley Health System, Ridgewood, NJ.

Objectives:
To determine if there are advantages to transitioning to robotics by a surgeon who is already proficient in performing video-assisted thoracic surgical (VATS) lobectomy.
Methods:
A single surgeon proficient in VATS lobectomy initiated a robotic lobectomy program, and a retrospective review was conducted of his patients undergoing minimally invasive lobectomy (robotics or VATS) for lung cancer between 2011 and 2012. Data collected included patient/tumor characteristics, morbidity, mortality, operative times, and length of hospital stay.
Results:
Over a 24-month period, a total of 69 patients underwent minimally invasive lobectomy (35 robotic, 34 VATS). Patients in each group were similar in age and clinical stage. Robotic upper lobectomy operative times were longer than VATS (172 vs 134 minutes; P = .001), with no significant difference in lower lobectomies noted (140 vs 123 minutes; P = .1). Median length of stay was 3 days in both groups, and the median number of lymph nodes harvested was 18 (robotic) versus 16 (VATS; P = .42). Morbidity and mortality for robotic versus VATS were 11% versus 18% (P = .46) and 0% versus 3% (P = .49), respectively.
Conclusions:
There does not seem to be a significant advantage for an established VATS lobectomy surgeon to transition to robotics based on clinical outcomes. The learning curve for robotic upper lobectomies seems to be more significant than that for lower lobectomies.