Related Experiment Video
Updated: May 4, 2026
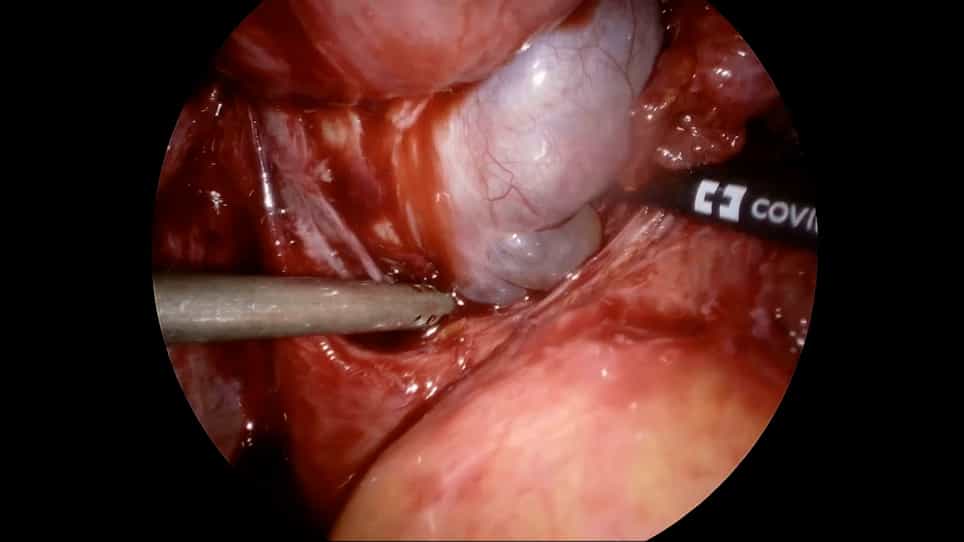
Surgical Techniques to Optimize Ovarian Reserve during Laparoscopic Cystectomy for Ovarian Endometrioma
Published on: January 22, 2022
Pathophysiology proposed as the basis for modern management of the ovarian endometrioma
Ivo Brosens1, Stephan Gordts1, Patrick Puttemans1
1Leuven Institute for Fertility and Embryology, Leuven, Belgium.

Abstract:
Present management of the ovarian endometrioma focuses on the size of the cyst and dictates that surgery should not be performed unless this exceeds 3 cm, which neglects the complex pathology of this condition. Studies of ovaries with the endometrioma in situ show progressive smooth muscle cell metaplasia and fibrosis of the cortical layer as the main ovarian lesion. There is no correlation between the size of the endometrial cyst and the degree of ovarian pathology: it is the mere presence of an ovarian endometrioma that has a detrimental impact on the cortical layer's follicle reserve. Cystectomy in young patients with an endometrioma may be particularly detrimental to follicle reserve, with the ovarian parenchyma loss at the time of surgery being related to the cyst's diameter. An underutilized diagnostic procedure, transvaginal hydrolaparoscopy with in-situ inspection of the cyst wall by ovarioscopy, allows careful diagnosis of ovarian pathology and selection of appropriate surgery with minimal invasiveness. Thus, available evidence shows that expectant management may not be the best choice when an endometrioma is suspected. On the contrary, early diagnosis through a minimally invasive technique, followed by early ablative surgery whenever indicated, represents the management of choice to preserve normal ovarian function. Present management of ovarian endometriomata is based on the size of the cyst and dictates that surgery should not be performed unless this exceeds 3cm. We argue that this approach neglects the true pathology of the ovary, since pioneers have studied ovaries with the endometrioma in situ and demonstrated that progressive smooth muscle cell metaplasia and fibrosis in the cortical layer constitute the main features of an endometrioma. There is no correlation between the size of the endometrial cyst and the degree of ovarian pathology: it is in the first place the mere presence of an ovarian endometrioma that has a detrimental impact on follicle reserve. It has been shown that cyst ablation in young patients with an endometrioma may be particularly detrimental to follicle reserve. An underutilized diagnostic procedure, transvaginal needle endoscopy with in-situ inspection after injection of saline suspension into the peritoneal cavity (hydrolaparoscopy) allows careful diagnosis of ovarian cortical pathology by colour changes from pearl-white to dark fibrotic. Thus, available evidence shows that expectant management may not be the best choice when an endometrioma is suspected: the delay in diagnosis causes delay in treatment and progression of the process leading to loss of follicles. On the contrary, early diagnosis through a minimally invasive technique, followed by early ablative surgery whenever indicated, represents the management of choice to preserve normal ovarian function.

Related Concept Videos
 02:07
Oogenesis
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:27
Ovarian Cycle