Related Experiment Video
Updated: May 4, 2026


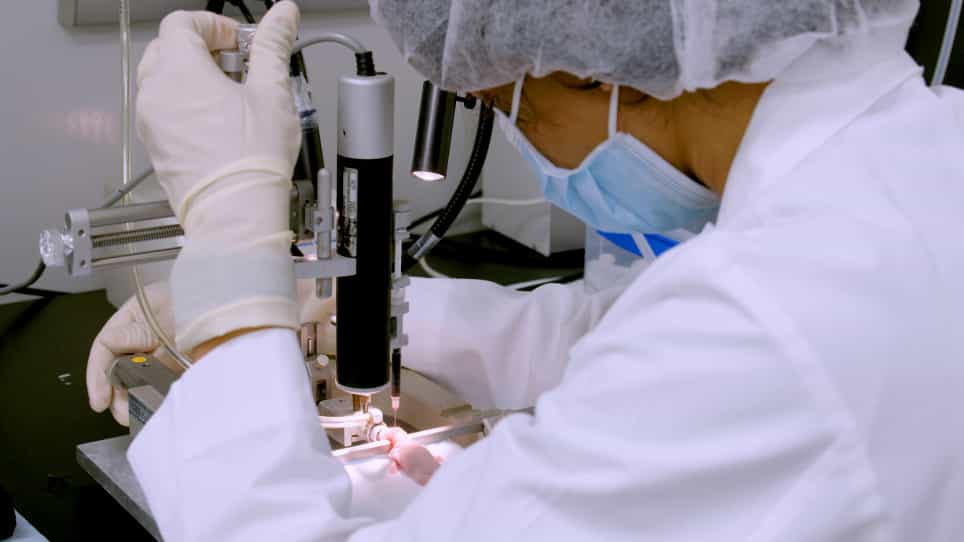
Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
Outcomes of extremely preterm infants following severe intracranial hemorrhage
A S Davis1, S R Hintz1, R F Goldstein2
1Division of Neonatal and Developmental Medicine, Department of Pediatrics, Stanford University, Palo Alto, CA, USA.

Insights
Bilateral intracranial hemorrhage (ICH) and hemorrhagic parenchymal infarction (HPI) in extremely preterm infants are linked to poor outcomes. The significance of these findings varies by birth weight and gestational age.
Area of Science:
- Neonatal neurology
- Pediatric neuroimaging
- Perinatal medicine
Background:
- Severe intracranial hemorrhage (ICH) is a critical factor influencing outcomes in extremely preterm (EPT) infants.
- Identifying predictors of adverse outcomes in this vulnerable population is essential for clinical management.
Purpose of the Study:
- To investigate imaging and clinical variables that predict outcomes in EPT infants diagnosed with severe ICH.
- To determine the association of unilateral vs. bilateral ICH and the presence/absence of hemorrhagic parenchymal infarction (HPI) with mortality and neurodevelopmental impairment (NDI).
Main Methods:
- Retrospective analysis of 353 EPT infants with severe ICH.
- Comparison of outcomes based on ICH laterality (unilateral vs. bilateral) and HPI presence.
- Regression analyses to identify independent predictors of death or NDI.
Main Results:
- Bilateral ICH and HPI were independently associated with increased rates of death and NDI.
- HPI was a significant predictor in lower birth weight infants, while bilateral ICH was more critical in larger EPT infants.
- Among survivors reaching 36 weeks, shunt placement correlated with higher rates of death/NDI.
Conclusions:
- Bilateral ICH and HPI are significant indicators of adverse outcomes in EPT infants with severe ICH.
- The prognostic importance of these findings is modulated by infant birth weight and postmenstrual age at 36 weeks.
Objective:
Severe intracranial hemorrhage (ICH) is an important prognostic variable in extremely preterm (EPT) infants. We examined imaging and clinical variables that predict outcomes in EPT infants with severe ICH.
Study Design:
Retrospective analysis of 353 EPT infants with severe ICH. Outcomes were compared by examining: (i) unilateral vs bilateral ICH; and (ii) presence vs absence of hemorrhagic parenchymal infarction (HPI). Regression analyses identified variables associated with death or neurodevelopmental impairment (NDI).
Result:
Bilateral ICH and HPI had higher rates of adverse outcomes and were independently associated with death/NDI. HPI was the most important variable for infants of lower birth weight, and bilateral ICH for larger infants. For infants surviving to 36 weeks, shunt placement was most associated with death/NDI.
Conclusion:
Bilateral ICH and the presence of HPI in EPT infants with severe ICH are associated with death/NDI, though the importance depends on birth weight and survival to 36 weeks.
More Related Videos

Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:28
Traumatic Brain Injury l: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology