Extremely high levels of C-reactive protein in patients with acute lupus serositis

K Ueki1, H Ikeuchi, F Ota

  • 1Third Department of Internal Medicine, Gunma University School of Medicine , 3-39-15 Showa, Maebashi 371-8511 , Japan.

Modern Rheumatology
|January 7, 2014
PubMed

Related Concept Videos

Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers01:19

Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers

Cardiac biomarkers are critical in diagnosing, prognosing, and managing cardiovascular diseases. Routine measurement of specific biomarkers such as B-type natriuretic peptide (BNP), C-reactive protein (CRP), and homocysteine (Hcy) is common practice in clinical settings to evaluate heart function and predict cardiovascular events.
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
765
Acute Inflammation II: Local and Systemic Effects01:25

Acute Inflammation II: Local and Systemic Effects
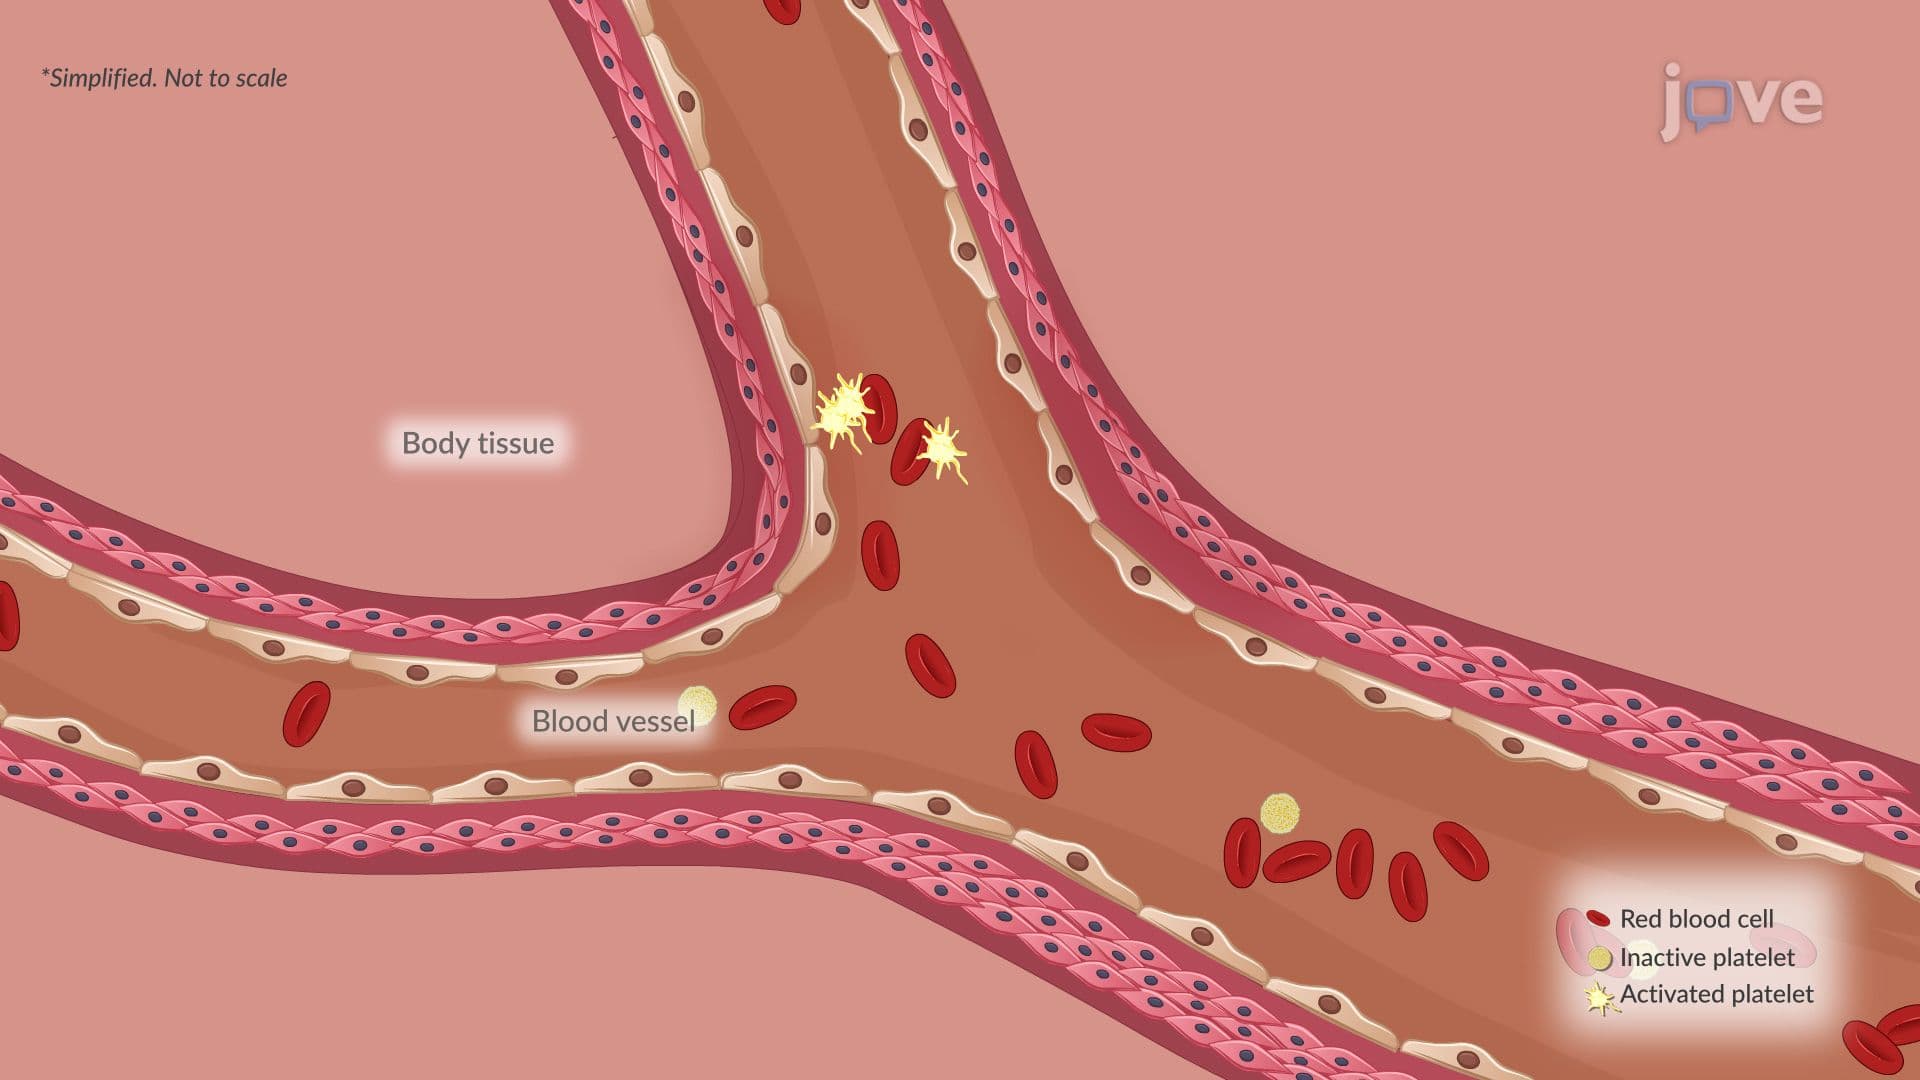
Acute inflammation produces a coordinated set of local and systemic changes that limit injury, eliminate pathogens, and initiate repair. These responses arise within minutes of infection, trauma, or chemical insult and are driven by vascular alterations and leukocyte-derived mediators. When the stimulus resolves, the reaction typically abates within days.Local EffectsAt the site of injury, arteriolar vasodilation increases blood flow, resulting in redness and warmth. Simultaneously, increased...
56
Hypersensitivity Reactions: Immune-Complex Reactions01:19

Hypersensitivity Reactions: Immune-Complex Reactions

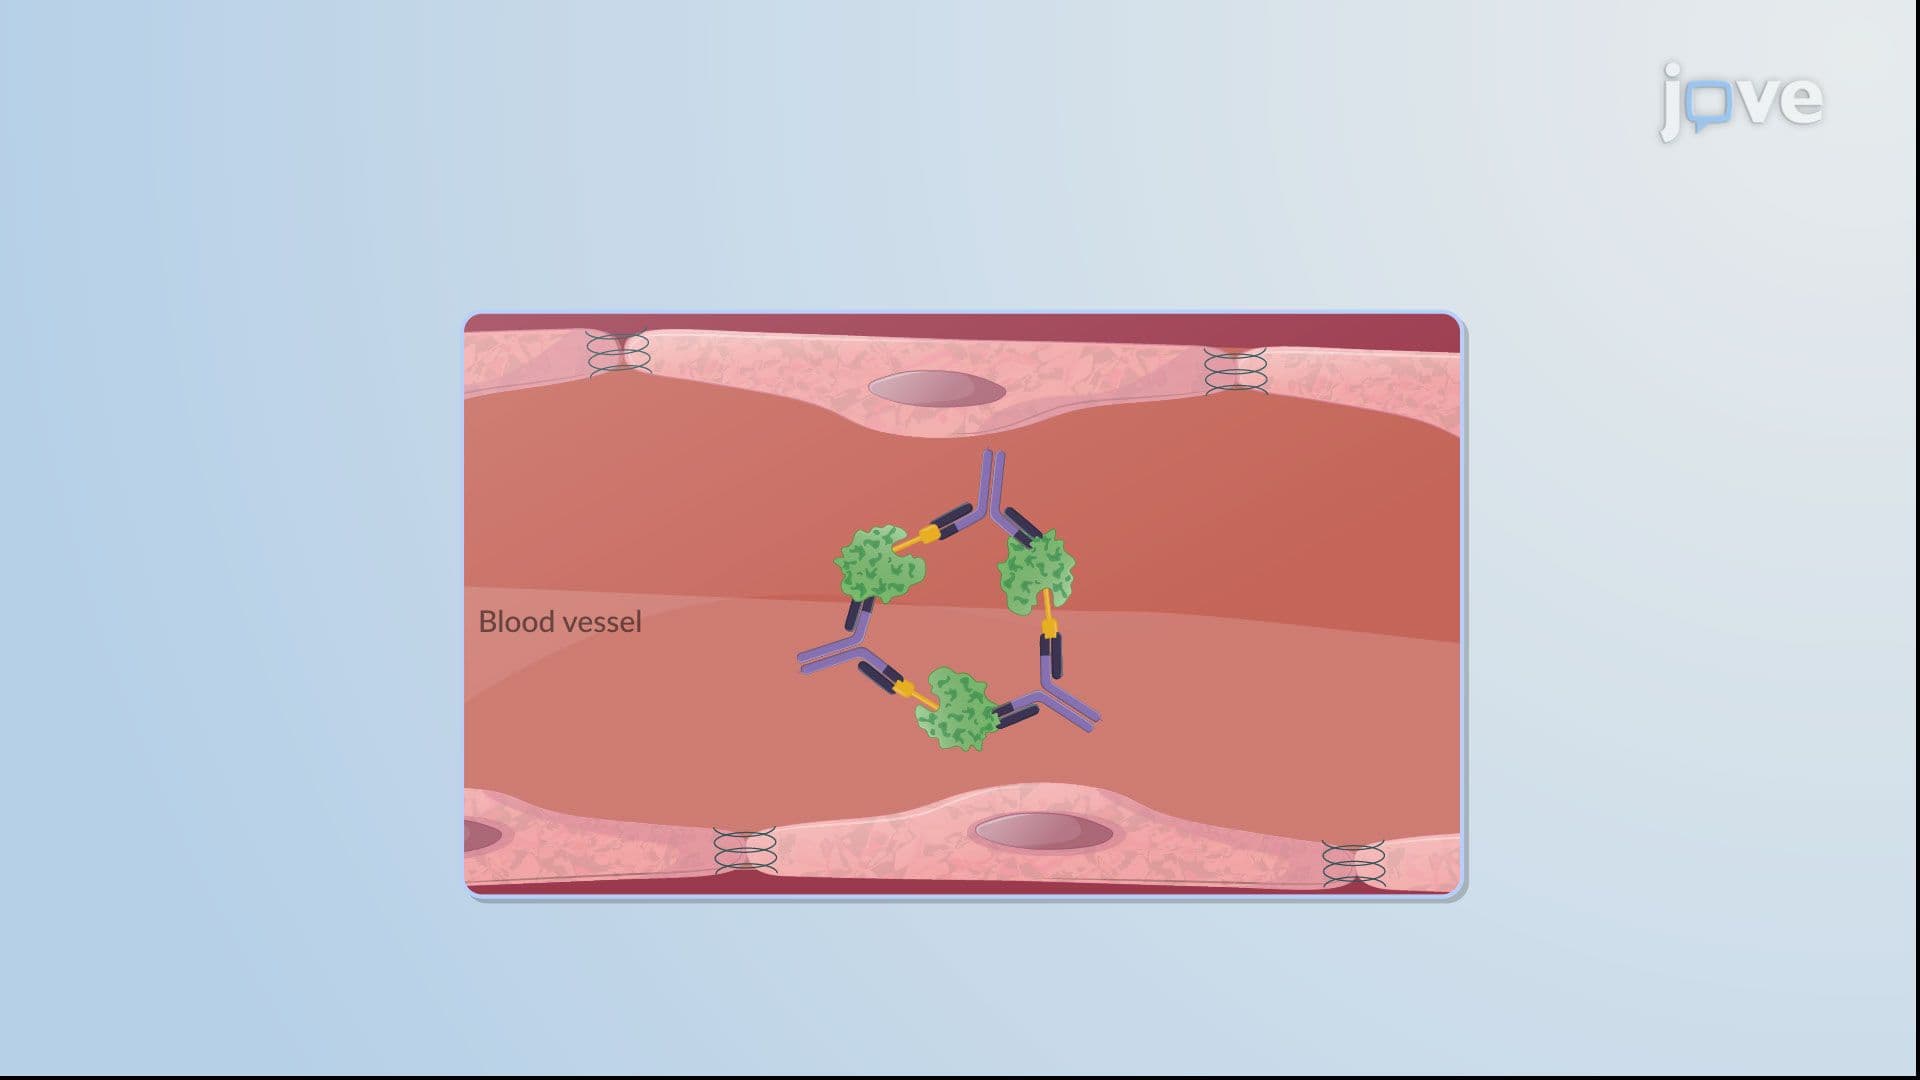
Type III hypersensitivity reactions occur when antigen–antibody complexes form and activate the complement system. Normally, these complexes help the clearance of antigens by phagocytes and red blood cells. However, when large numbers of immune complexes are present, they can deposit in tissues—particularly in the walls of blood vessels—leading to inflammation and tissue injury. These deposits trigger complement activation and neutrophil recruitment, resulting in serum...
269
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies01:22

Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies

The key clinical manifestations of Rheumatic heart disease (RHD) include several distinct cardiac symptoms.Carditis, a hallmark of acute rheumatic fever, involves inflammation of the heart's endocardium, myocardium, and pericardium. Chronic RHD often results from recurrent episodes of carditis. Its symptoms include the following:Murmurs are caused by valvular damage, especially to the mitral and aortic valves. Mitral stenosis or regurgitation is common, with characteristic heart murmurs...
1.3K
Chronic Inflammation: Introduction01:12

Chronic Inflammation: Introduction

Chronic inflammation is a prolonged, dysregulated immune response that persists for weeks to years when the inciting stimulus is difficult to eradicate or when self‑antigens drive ongoing reactivity. Morphologically, it is defined by mononuclear cell infiltration, progressive tissue destruction, and concurrent attempts at healing via angiogenesis and fibrosis. Compared with acute inflammation, edema is less prominent while cellular infiltration predominates; triggers include persistent...
41
Cushing Syndrome II: Pathophysiology01:19

Cushing Syndrome II: Pathophysiology

Cortisol production is normally governed by the hypothalamic–pituitary–adrenal (HPA) axis, which maintains hormonal balance through tightly regulated feedback mechanisms. Disruption of this regulatory system is central to the development of Cushing syndrome, whether the excess cortisol originates from external medications or internal pathology. Persistent cortisol elevation alters metabolism, immune function, and endocrine signaling, producing the characteristic clinical features...
24