Related Experiment Video
Updated: May 4, 2026
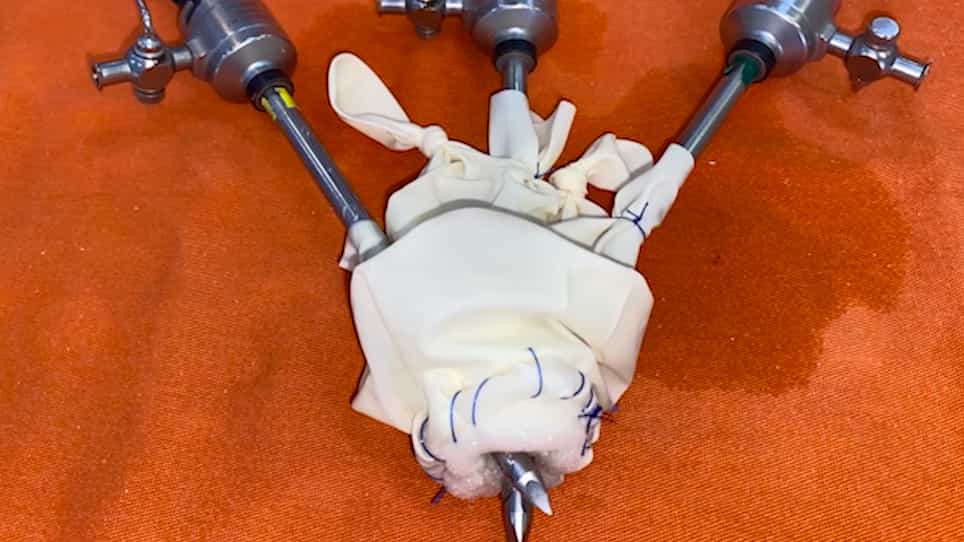
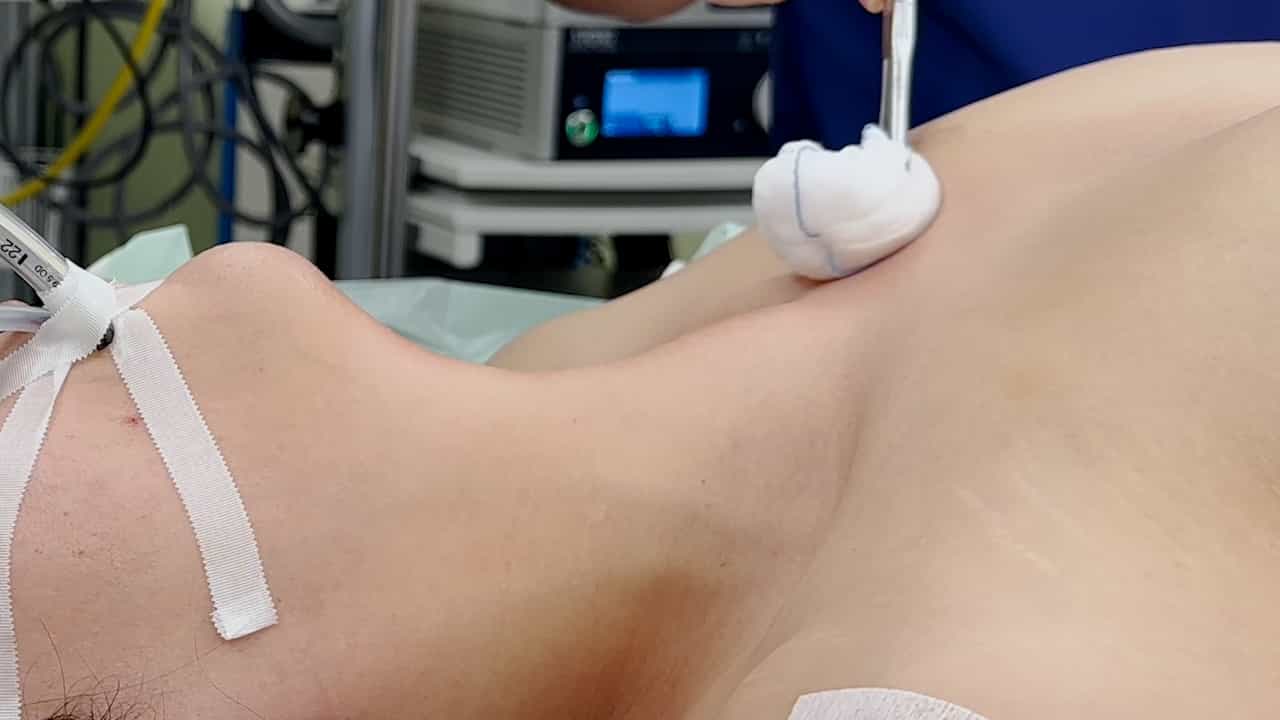
Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Minimally-invasive subtotal oesophagectomy: three-stage thoracoscopic, laparoscopic subtotal oesophagectomy with
1Peninsula Oesophagogastric Cancer Centre, Derriford Hospital, Crownhill, Plymouth, Devon PL6 8DH, UK.

Abstract:
This contribution describes a minimally-invasive approach to subtotal oesophagectomy. Indications, pre-emptive ischaemic conditioning and feeding jejunostomy are discussed. In the lateral position, the oesophagus is mobilized thoracoscopically in a specific order, formally identifying 'at risk' structures. A radical en bloc dissection is performed with formal lymphadenectomy. Slings are placed around proximal and distal oesophagus and a paravertebral catheter is inserted for postoperative analgesia. In the supine position, the stomach is mobilized laparoscopically, preserving the gastroepiploic arcade and the right gastric artery. Kocher's manoeuvre is undertaken. Lymphadenectomy is performed around the coeliac axis, common hepatic, left gastric and splenic arteries. The proximal oesophagus is delivered through a cervical approach and transected, suturing the distal end to a delivery system to facilitate passage of the conduit through the mediastinum. The mobilized stomach is delivered through a 6-cm right paramedian minilaparotomy and a wide gastric conduit formed, preserving collateral supply and venous drainage from the distal lesser curve. The conduit is passed to the neck using a vacuum/camera sleeve technique and anastomosed to the transected cervical oesophagus with a semi-mechanical technique. The paramedian minilaparotomy is closed with a local anaesthetic catheter in the posterior sheath and the conduit brought back into an anatomical position laparoscopically. Postoperative care is described.