Related Experiment Video
Updated: May 3, 2026


Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
CT findings of gastric and intestinal anisakiasis
Eisuke Shibata1, Takuya Ueda, Gensuke Akaike
1Department of Radiology, Tokyo Metropolitan Police Hospital, 4-22-1 Nakano, Nakano-ku, Tokyo, 164-8541, Japan, eisuke.shibata1130@gmail.com.

Purpose:
To illustrate the CT findings of gastrointestinal anisakiasis.
Subjects And Methods:
The Institutional Review Board approving this retrospective study waived the requirement for informed consent. Review of our emergency department's clinical records from September 2008 to January 2012 identified 41 consecutive patients who were diagnosed with gastrointestinal anisakiasis. 20 patients were diagnosed with gastric anisakiasis with endoscopically proven Anisakis larvae, and 21 patients were diagnosed with intestinal anisakiasis with positive test results for anti-anisakidae antibody and the presence of intestinal lesions on CT. Two radiologists retrospectively assessed the CT findings.
Results:
The mean time delay from raw fish ingestion to symptom onset was 5.2 h (range 0.5-24 h) in gastric anisakiasis and 39 h (range 12-120 h) in intestinal anisakiasis. Gastric anisakiasis showed marked submucosal edema of the gastric wall (20/20 patients, 100%), increased attenuation of adjacent fat (19/20, 95%), and ascites (14/20, 70%) on CT. Intestinal anisakiasis showed marked submucosal edema of the intestine (21/21 patients, 100%) without showing complete intraluminal occlusion, ascites (21/21, 100%), increased attenuation of adjacent fat (19/21, 90%), and fluid collection in the distal segment of the constricted small intestine (13/21, 62%) on CT.
Conclusion:
Severe submucosal edema with ascites is a characteristic finding of gastrointestinal anisakiasis when compared with other forms of gastroenteritis. When CT shows the typical findings of gastrointestinal anisakiasis, radiologists may suggest the possibility of clinically undiagnosed anisakiasis, especially in intestinal anisakiasis as the diagnosis is sometimes difficult due to the long interval between food intake and symptom onset.


Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:26
Gastritis II: Pathophysiology
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:27
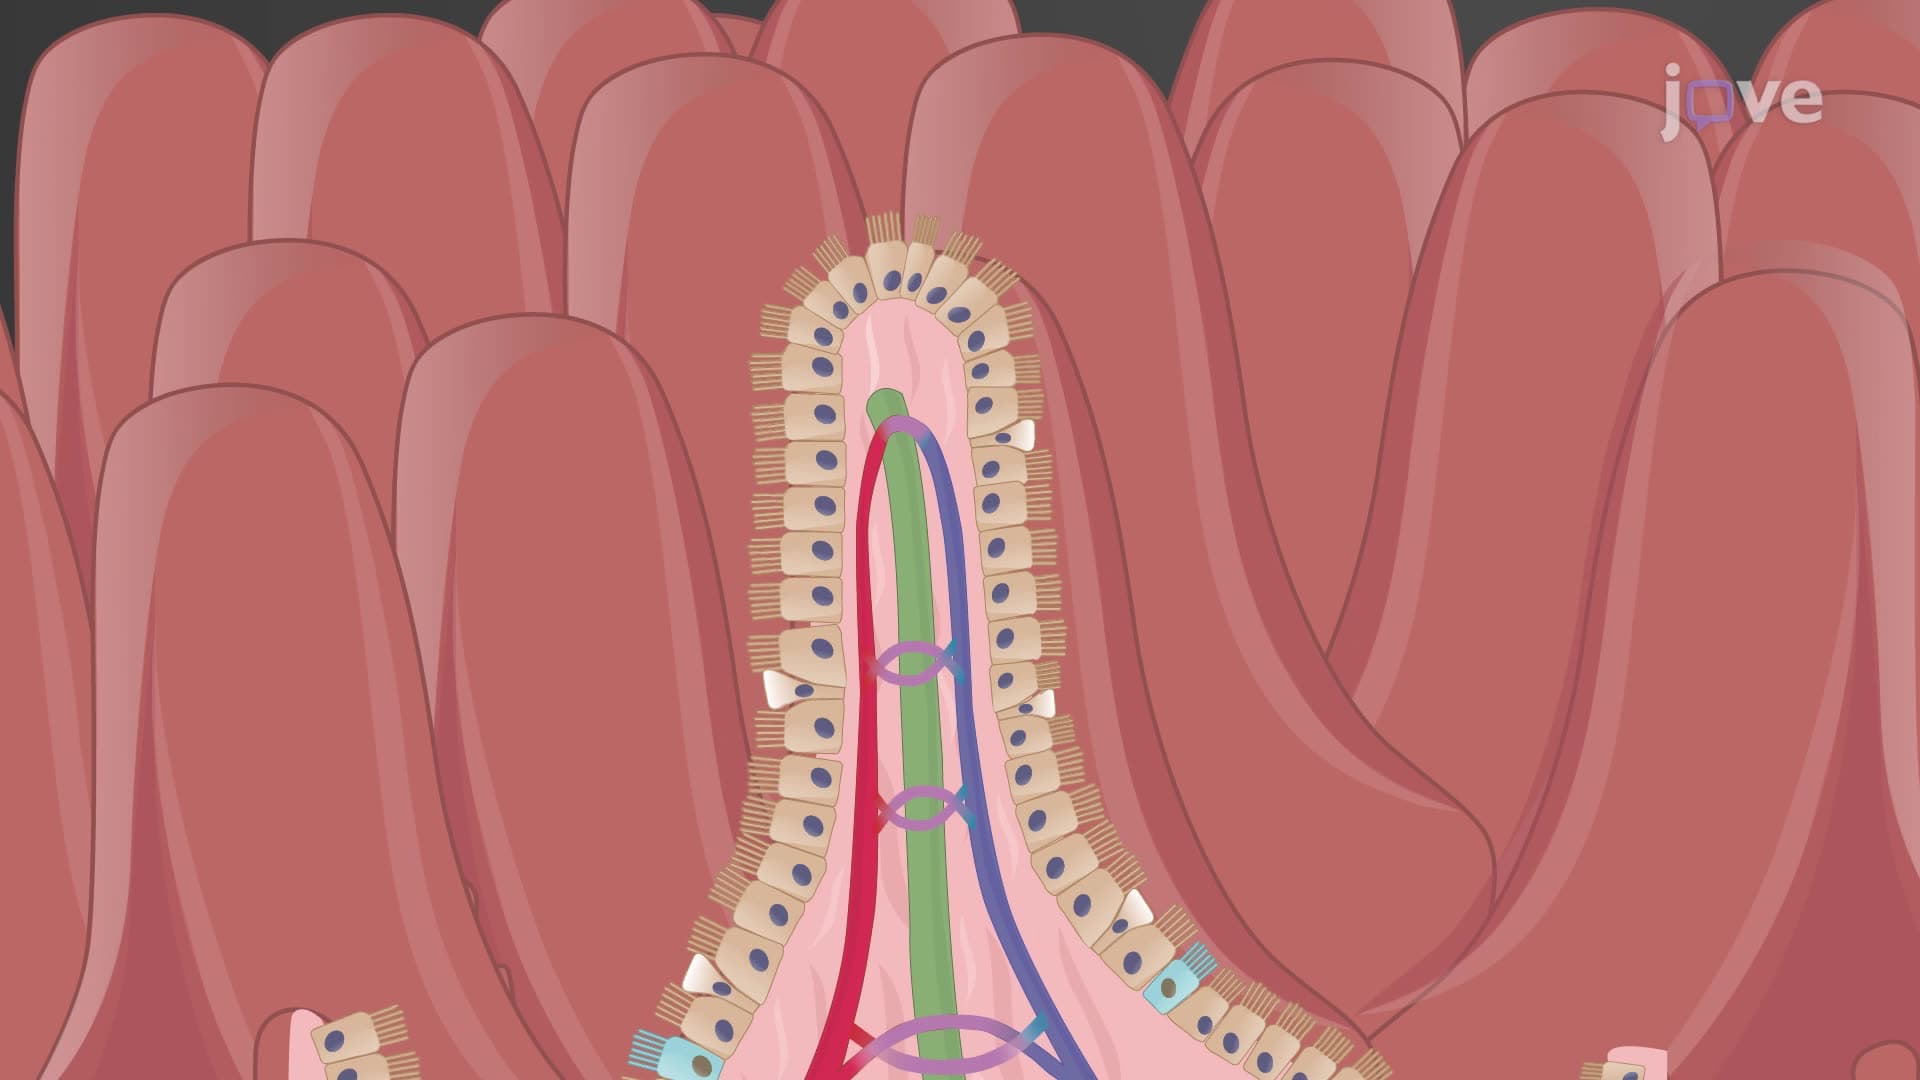
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...