Related Experiment Video
Updated: Sep 20, 2026

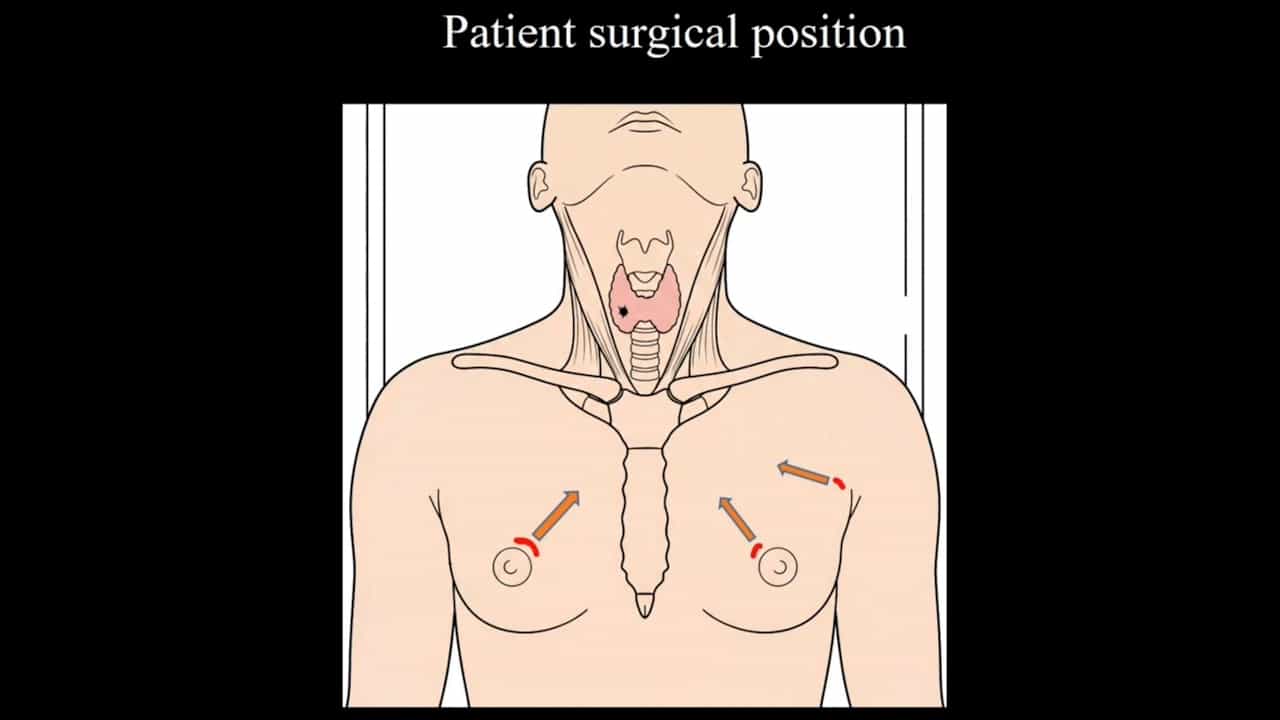
Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Dual-theatre high-intensity lists (HIT) for day-case minimally invasive parathyroidectomy: a prospective service
Christian Chess1, Laura Bateman2, Catherine Ashworth2
1Ear, Nose and Throat, Royal United Hospital Bath NHS Trust, Bath, UK christian.chess@btinternet.com.

Background:
Elective ENT waiting lists and constrained theatre capacity require pathway redesign that increases surgical throughput without compromising safety. At our trust, patients awaiting minimally invasive parathyroidectomy faced waits of approximately 52 weeks, while routine intraoperative frozen-section confirmation created predictable theatre downtime.
Local Problem:
Minimally invasive parathyroidectomy is well suited to day-case high-intensity theatre delivery because selected patients follow a standardised pathway. However, evidence for dual-theatre models in this setting is limited.
Methods:
We conducted a prospective registered service evaluation of two dual-theatre, 5 hour morning high-intensity theatre sessions for day-case minimally invasive parathyroidectomy at a UK NHS trust. Predefined timings, throughput and safety/balancing outcomes were collected prospectively from routine theatre documentation.
Intervention:
Two adjacent theatres were allocated by operative side with staggered starts. One consultant surgeon alternated between rooms while assistants completed haemostatic checks and wound closure under supervision. Six selected day-case patients were scheduled per session; eligibility required concordant imaging and suitability for day-case surgery.
Results:
Twelve patients underwent successful minimally invasive parathyroidectomy across two morning sessions. Six cases were completed within each 5 hour session, and all procedures were completed by 13:00 on both days. Mean knife-to-specimen time was 18.4 min, mean frozen-section duration was 24.1 min, mean incision-to-closure time was 42.9 min, and mean call-to-incision time was 42.2 min. All patients had histological confirmation of parathyroid adenoma and postoperative biochemical improvement.
Conclusions:
A dual-theatre high-intensity theatre model can convert frozen-section waiting time into productive operating time and substantially increase throughput for carefully selected day-case parathyroidectomy pathways. Wider implementation requires careful patient selection, operational planning, pathology availability, staff engagement and prospective monitoring of safety, cost and workforce impact.