Related Experiment Video
Updated: May 3, 2026
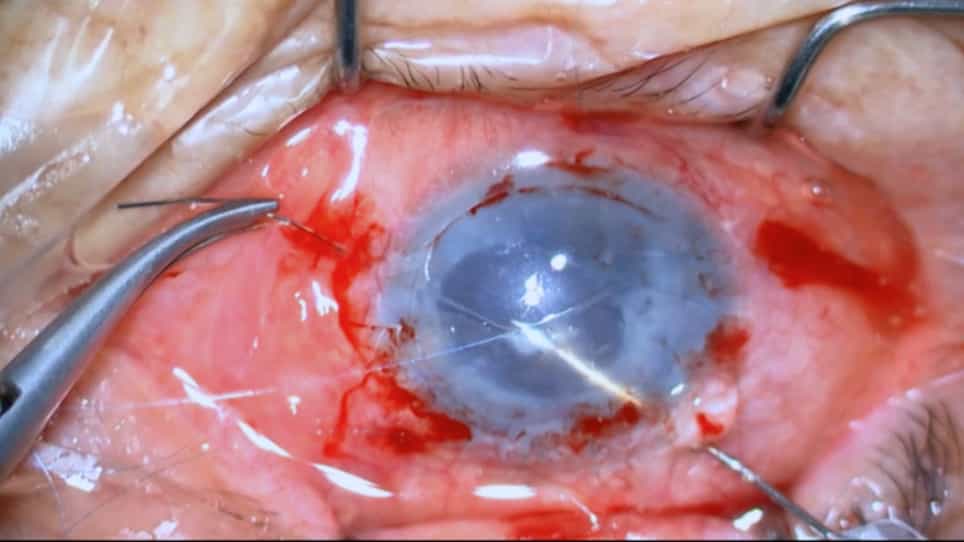

Iris Fixation via External Pentagram Suturing
Published on: May 5, 2022
Orbital cellulitis presenting as a first sign of incomplete kawasaki disease
Eren Cerman1, Muhsin Eraslan1, Semra Akkaya Turhan1
1Department of Ophthalmology, Marmara University School of Medicine, Istanbul, Turkey.

Abstract:
A 6-year-old boy was referred to our hospital with orbital cellulitis. He had a history of 7 days of fever despite antibiotherapy. At first, he only had pharyngitis and conjunctivitis, but then an orbital mass evolved which restricted the movement of his right eye and there was also periorbital inflammation resembling orbital cellulitis. Examination at presentation revealed conjunctivitis with secretion, periocular inflammation and edema, right-preauricular lymphadenopathy and restriction of upgaze in the right eye. Laboratory findings included a white blood cell count of 19,000 cells per mm3, with 81.5% neutrophils, 15.0% lymphocytes, 1.2% monocytes and 0.4% basophils. The erythrocyte sedimentation rate was 52 mm/h and the C-reactive protein level was 46.3 mg/dl. Magnetic resonance imaging confirmed orbital cellulitis and pansinusitis. Vancomycin (60 mg/kg/day) and meropenem (100 mg/kg/day) were administered, but desquamation on his fingertips and a rash appeared on the tenth day. A pediatric consultation resulted in a diagnosis of incomplete Kawasaki disease (KD). After administration of aspirin, the orbital inflammation regressed in 3 days. No coronary artery lesions were detected on the first echocardiography, but these did appear 6 weeks later. This confirmed the KD diagnosis.

Related Concept Videos
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:22
Pericarditis I: Introduction
 01:26
Brain Abscess l: Introduction
 01:19
Pericarditis II: Clinical Features and Diagnostic Tests
 01:24
Chronic Kidney Disease II: Clinical Manifestations