Mechanisms of drug-induced pulmonary disease

J A Cooper1, R J Zitnik, R A Matthay

  • 1Pulmonary Division, West Haven Veterans Administration Medical Center 06516.

Related Concept Videos

Chronic Obstructive Pulmonary Disease-II: Pathophysiology01:20

Chronic Obstructive Pulmonary Disease-II: Pathophysiology

Chronic Obstructive Pulmonary Disease (COPD) pathophysiology is intricate and multifaceted, involving a complex interplay of physiological processes. Understanding these mechanisms is crucial for effectively managing and treating COPD. Here is an in-depth look at the critical elements in the pathophysiology of COPD:
Chronic Inflammation
Drug Toxicity: Allergic Reactions01:30

Drug Toxicity: Allergic Reactions

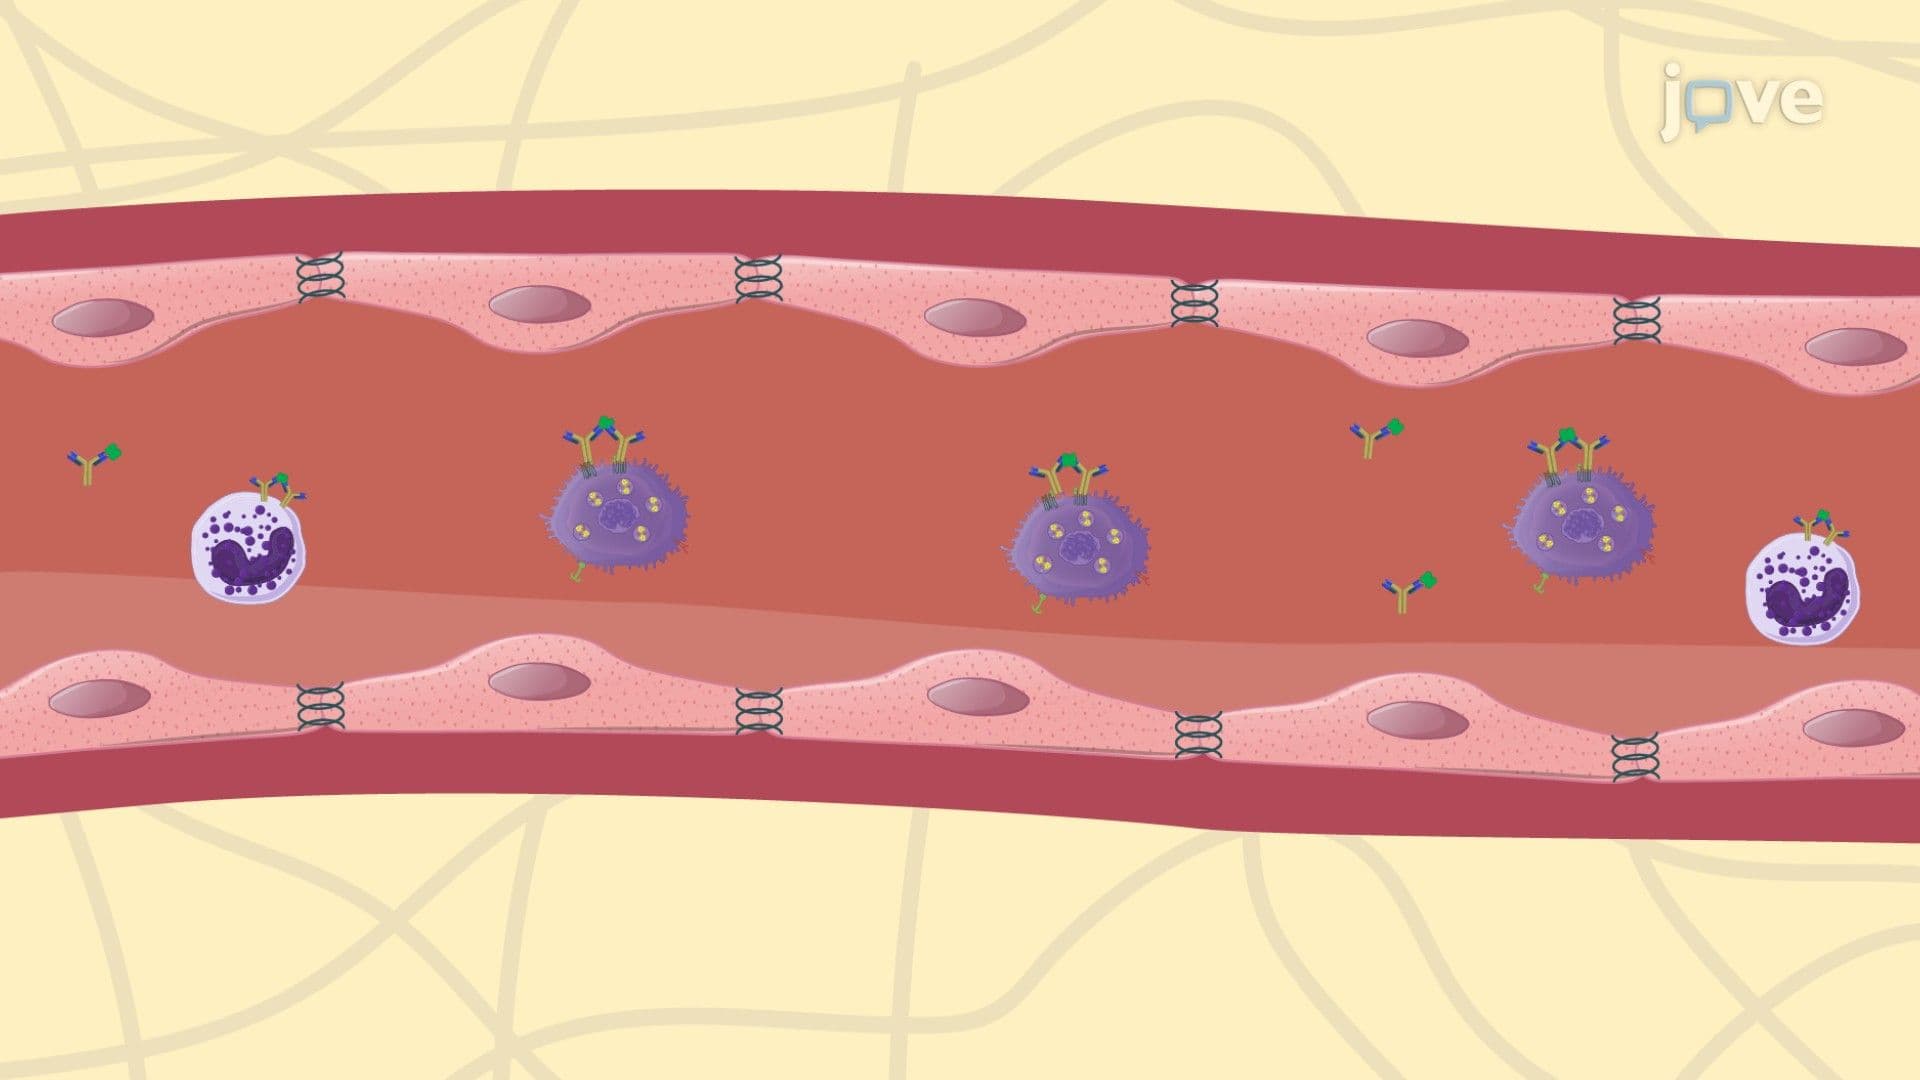
Drug-related allergies are immune-mediated responses triggered by the administration of pharmacological agents. These hypersensitivity reactions are classified based on the immune mechanisms involved. The four primary types—Type I, II, III, and IV—are mediated by different immunological pathways and exhibit distinct clinical manifestations.Type I Hypersensitivity/ IgE-Mediated Reactions: Immunoglobulin E (IgE) immediately mediates Type I hypersensitivity reactions. Upon initial exposure to a...
Drug toxicity: Idiosyncratic Reactions01:16

Drug toxicity: Idiosyncratic Reactions

Idiosyncratic drug reactions represent abnormal chemical responses that vary significantly among individuals, ranging from extreme sensitivity to low doses to insensitivity to high doses. These reactions often occur due to the drug's covalent binding with serum proteins, forming a foreign hapten that triggers an immunotoxicological response. The variability in drug reactions has a strong pharmacogenetic foundation, with genetic differences crucial in how individuals metabolize drugs. For...
Drug toxicity: Drug–Drug Interaction01:30

Drug toxicity: Drug–Drug Interaction
Drug–drug interactions can precipitate toxicity through multiple mechanisms. Absorption interactions alter how drugs enter the body, exemplified when ranitidine increases the absorption of basic drugs, while cholestyramine decreases the levels of propranolol. Protein binding interactions occur when drugs share the same binding sites on plasma proteins. Drugs like aspirin and warfarin, when bound in excess, can lead to increased free drug concentrations, enhancing the potential for...
Chronic Obstructive Pulmonary Disease I: Introduction01:23

Chronic Obstructive Pulmonary Disease I: Introduction

Chronic obstructive pulmonary disease is a common, preventable, and treatable respiratory disorder characterized by persistent symptoms and progressive airflow limitation. This limitation results from a combination of small-airway disease (obstructive bronchiolitis) and parenchymal destruction (emphysema), both driven by chronic inflammation from exposure to harmful particles or gases.The disease includes two main pathological entities: emphysema, marked by destruction of alveolar walls and...
Pulmonary Edema II: Pathophysiology01:18

Pulmonary Edema II: Pathophysiology

Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...