Related Experiment Video
Updated: May 2, 2026


Author Spotlight: Advancements in Multiplex Detection of Respiratory Viruses
Published on: November 10, 2023
Severe acute respiratory syndrome vs. the Middle East respiratory syndrome
David S Hui1, Ziad A Memish, Alimuddin Zumla
1aDepartment of Medicine & Therapeutics, Stanley Ho Center for Emerging Infectious Diseases, The Chinese University of Hong Kong, Shatin, New Territories, Hong Kong bMinistry of Health, Al-Faisal University, Riyadh, Kingdom of Saudi Arabia cDivision of Infection and Immunity, Department of Infection, Centre for Clinical Microbiology, University College London dNIHR Biomedical Research Centre, University College London Hospitals, London, UK.

Purpose Of Review:
This review compares the clinical features, laboratory aspects and treatment options of severe acute respiratory syndrome (SARS) and the Middle East respiratory syndrome (MERS).
Recent Findings:
Bats are the natural reservoirs of SARS-like coronaviruses (CoVs) and are likely the reservoir of MERS coronavirus (MERS-CoV). Although a small number of camels have been found to have positive nasal swabs by real-time polymerase chain reaction and to carry antibody against MERS-CoV, the transmission route and the intermediary animal source remain uncertain amongst the sporadic primary cases. Both SARS-CoV and MERS-CoV may cause severe respiratory failure and extrapulmonary features such as diarrhoea, whereas mild or asymptomatic cases also occur in both conditions. In comparison with SARS, patients with MERS are older with male predominance, more comorbid illness and relatively lower human-to-human transmission potential. Although the viral kinetics of MERS-CoV remain unknown, nosocomial infections of MERS occur early within the first week of illness of the index case, whereas those of SARS occurred mainly in the second week of illness when the patient's upper airway viral load peaks on day 10 of illness. In-vitro data suggest that interferon (IFN) with or without ribavirin and mycophenolic acid may inhibit MERS-CoV, whereas protease inhibitors and IFN have inhibitory activity against SARS-CoV.
Summary:
Although there are some similarities in the clinical features, MERS progresses to respiratory failure much more rapidly than SARS. The higher case fatality rate of MERS is likely related to older age and comorbid illness. More studies are needed to understand MERS-CoV in order to guide public health infection control measures and treatment.
More Related Videos
 08:41
Live Imaging and Quantification of Viral Infection in K18 hACE2 Transgenic Mice Using Reporter-Expressing Recombinant SARS-CoV-2
Published on: November 5, 2021
 08:05
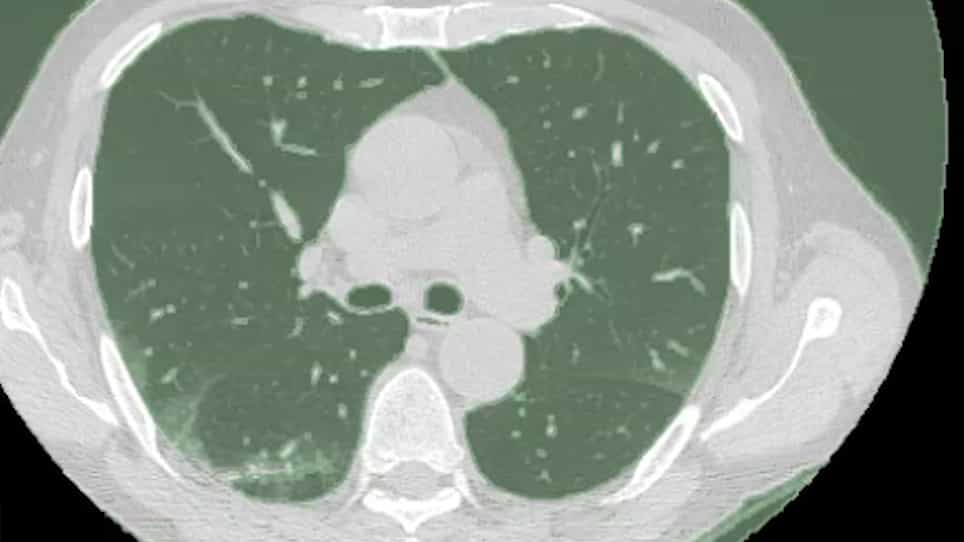
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:18
Viral Meningitis
 01:14
Atypical Pneumonia
 01:23
Acute Respiratory Failure-IV
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...