Related Experiment Video
Updated: May 2, 2026

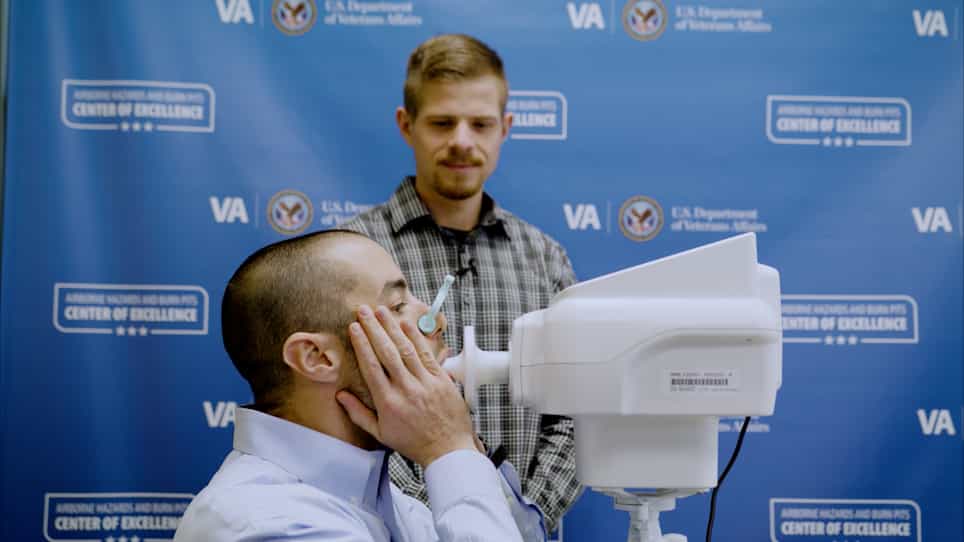
Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Inspiratory high frequency airway oscillation attenuates resistive loaded dyspnea and modulates respiratory function
Theresa Morris1, David Paul Sumners2, David Andrew Green1
1Centre of Human & Aerospace Physiological Sciences, King's College London, London, United Kingdom.

Abstract:
Direct chest-wall percussion can reduce breathlessness in Chronic Obstructive Pulmonary Disease and respiratory function may be improved, in health and disease, by respiratory muscle training (RMT). We tested whether high-frequency airway oscillation (HFAO), a novel form of airflow oscillation generation can modulate induced dyspnoea and respiratory strength and/or patterns following 5 weeks of HFAO training (n = 20) compared to a SHAM-RMT (conventional flow-resistive RMT) device (n = 15) in healthy volunteers (13 males; aged 20-36 yrs). HFAO causes oscillations with peak-to-peak amplitude of 1 cm H2O, whereas the SHAM-RMT device was identical but created no pressure oscillation. Respiratory function, dyspnoea and ventilation during 3 minutes of spontaneous resting ventilation, 1 minute of maximal voluntary hyperventilation and 1 minute breathing against a moderate inspiratory resistance, were compared PRE and POST 5-weeks of training (2 × 30 breaths at 70% peak flow, 5 days a week). Training significantly reduced NRS dyspnoea scores during resistive loaded ventilation, both in the HFAO (p = 0.003) and SHAM-RMT (p = 0.005) groups. Maximum inspiratory static pressure (cm H2O) was significantly increased by HFAO training (vs. PRE; p<0.001). Maximum inspiratory dynamic pressure was increased by training in both the HFAO (vs. PRE; p<0.001) and SHAM-RMT (vs. PRE; p = 0.021) groups. Peak inspiratory flow rate (L.s(-1)) achieved during the maximum inspiratory dynamic pressure manoeuvre increased significantly POST (vs. PRE; p = 0.001) in the HFAO group only. HFAO reduced inspiratory resistive loading-induced dyspnoea and augments static and dynamic maximal respiratory manoeuvre performance in excess of flow-resistive IMT (SHAM-RMT) in healthy individuals without the respiratory discomfort associated with RMT.
Related Concept Videos
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:24
Factors Affecting Respiration
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:26
Respiratory Volumes and Capacities I
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...