Related Experiment Video
Updated: May 1, 2026
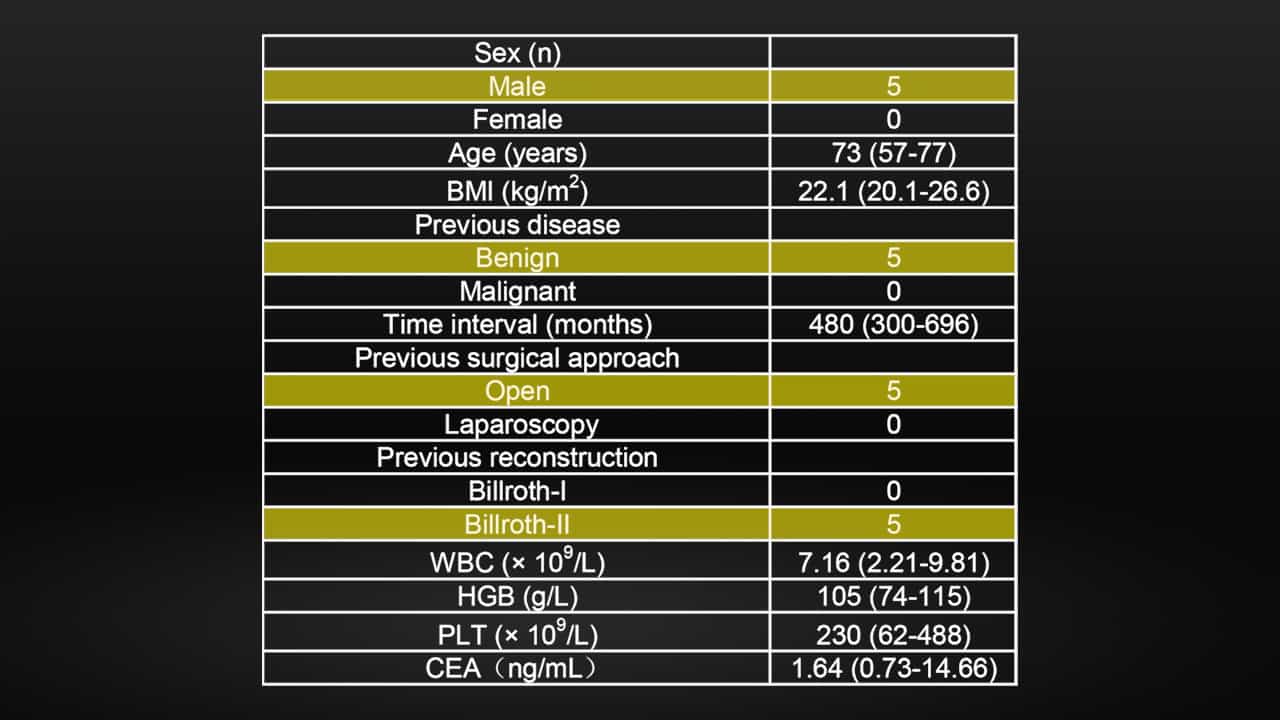

Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Retrospective analysis of adjuvant chemotherapy for curatively resected gastric cancer
Wei Deng1, Qi-Wei Wang1, Xiao-Tian Zhang1
1Wei Deng, Qi-Wei Wang, Xiao-Tian Zhang, Ming Lu, Jie Li, Yan Li, Ji-Fang Gong, Jun Zhou, Zhi-Hao Lu, Lin Shen, Key Laboratory of Carcinogenesis and Translational Research (Ministry of Education), Department of Gastrointestinal Oncology, Peking University Cancer Hospital and Institute, Beijing 100142, China.

Aim:
To determine the efficacy of adjuvant chemotherapy for gastric cancer in clinical practice, a retrospective analysis was conducted in a high-volume Chinese cancer center.
Methods:
Between November 1995 and June 2007, a total of 423 gastric or esophagogastric adenocarcinoma patients who did (Arm A, n = 300) or did not (Arm S, n = 123) receive radical gastrectomy followed by postoperative chemotherapy were enrolled in this retrospective analysis. In Arm A, monotherapy(fluoropyrimidines, n = 25), doublet (platinum/fluoropyrimidines, n = 164), or triplet regimens [docetaxel/cisplatin/5FU (DCF), or modified DCF, epirubicin/cisplatin/5FU (ECF) or modified ECF, etoposide/cisplatin/FU, n = 111] were administered. Disease-free survival (DFS) and overall survival (OS) were compared between the two arms. A subgroup analysis was carried out in Arm A. A multivariate analysis of prognostic factors was conducted.
Results:
Stage I, II and III cancers accounted for 9.7%, 35.7% and 54.6% of the cases, respectively, according to the American Joint Committee on Cancer (AJCC) staging system, 7(th) edition. Only 178 (42.1%) patients had more than 15 lymph nodes harvested. Hazard ratio estimates for Arm A compared with Arm S were 0.47 (P < 0.001) for OS and 0.59 (P < 0.001) for DFS. The 5-year OS rate was 52% in Arm A vs 36% in Arm S (P = 0.01); the adverse events in Arm A were mild and easily controlled. Ultimately, 73 patients (26.5%) who received doublet or triplet regimens switched to monotherapy with fluoropyrimidines. The OS and DFS did not differ between monotherapy and the combination regimens, however, both were statistically improved in the subgroup of patients who were switched to monotherapy with fluoropyrimidines after doublet or triplet regimens as well as patients who received ≥ 8 cycles of chemotherapy.
Conclusion:
In clinical practice, platinum/fluoropyrimidines with adequate treatment duration is recommended for stage II/III gastric cancer patients according to the 7(th) edition of the AJCC staging system after curative gastrectomy even with limited lymphadenectomy.
More Related Videos
 08:59
Looking for Driver Pathways of Acquired Resistance to Targeted Therapy: Drug Resistant Subclone Generation and Sensitivity Restoring by Gene Knock-down
Published on: December 11, 2017
 10:28
Gene Regulation and Targeted Therapy in Gastric Cancer Peritoneal Metastasis: Radiological Findings from Dual Energy CT and PET/CT
Published on: January 22, 2018
