Related Experiment Video
Updated: May 1, 2026
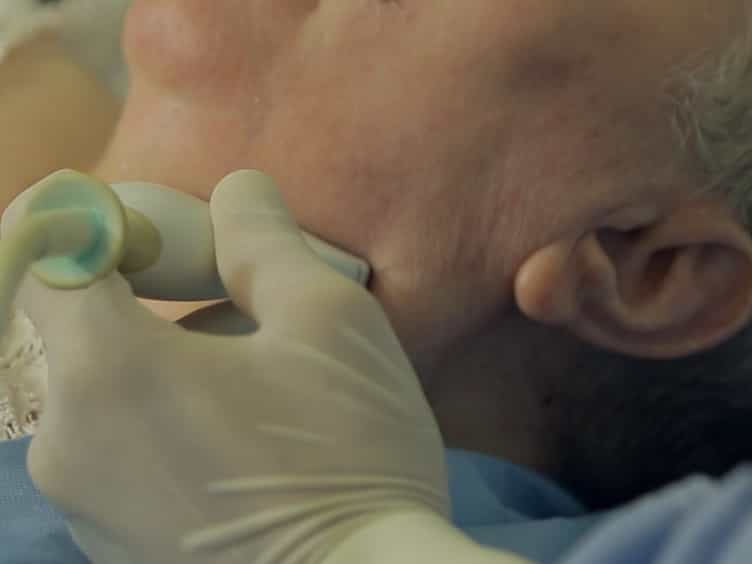

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Use of botulinum toxin in musculoskeletal pain
1Medicine Service and Center for Surgical Medical Acute Care Research and Transitions (C-SMART), Birmingham Veterans Affairs Medical Center, Birmingham AL, 35294, USA ; Department of Medicine at School of Medicine, and Division of Epidemiology at School of Public Health, University of Alabama, Birmingham AL, 35294, USA ; Department of Orthopedic Surgery, Mayo Clinic College of Medicine, Rochester MN, 55123, USA.

Abstract:
Chronic musculoskeletal pain is a common cause of chronic pain, which is associated with a total cost of $635 billion per year in the U.S. Emerging evidence suggests an anti-nociceptive action of botulinum toxin, independent of its muscle paralyzing action. This review provides a summary of data from both non-randomized and randomized clinical studies of botulinum toxin in back pain and various osteoarticular conditions, including osteoarthritis, tennis elbow, low back pain and hand pain. Three randomized controlled trials (RCTs) of small sizes provide evidence of short-term efficacy of a single intra-articular injection of 100 units of botulinum toxin A (BoNT/A) for the relief of pain and the improvement of both function and quality of life in patients with chronic joint pain due to arthritis. Three RCTs studied intramuscular BoNT/A for tennis elbow with one showing a significant improvement in pain relief compared with placebo, another one showing no difference from placebo, and the third finding that pain and function improvement with BoNT/A injection were similar to those obtained with surgical release. One RCT of intramuscular BoNT/A for low back pain found improvement in pain and function compared to placebo. Single RCTs using local injections of BoNT in patients with either temporomandibular joint (TMJ) pain or plantar fasciitis found superior efficacy compared to placebo. One RCT of intramuscular BoNT/B in patients with hand pain and carpal tunnel syndrome found improvement in pain in both BoNT/B and placebo groups, but no significant difference between groups. Most evidence is based on small studies, but the use of BoNT is supported by a single, and sometimes up to three, RCTs for several chronic musculoskeletal pain conditions. This indicates that botulinum toxin may be a promising potential new treatment for chronic refractory musculoskeletal pain. Well-designed large clinical trials are needed.

Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
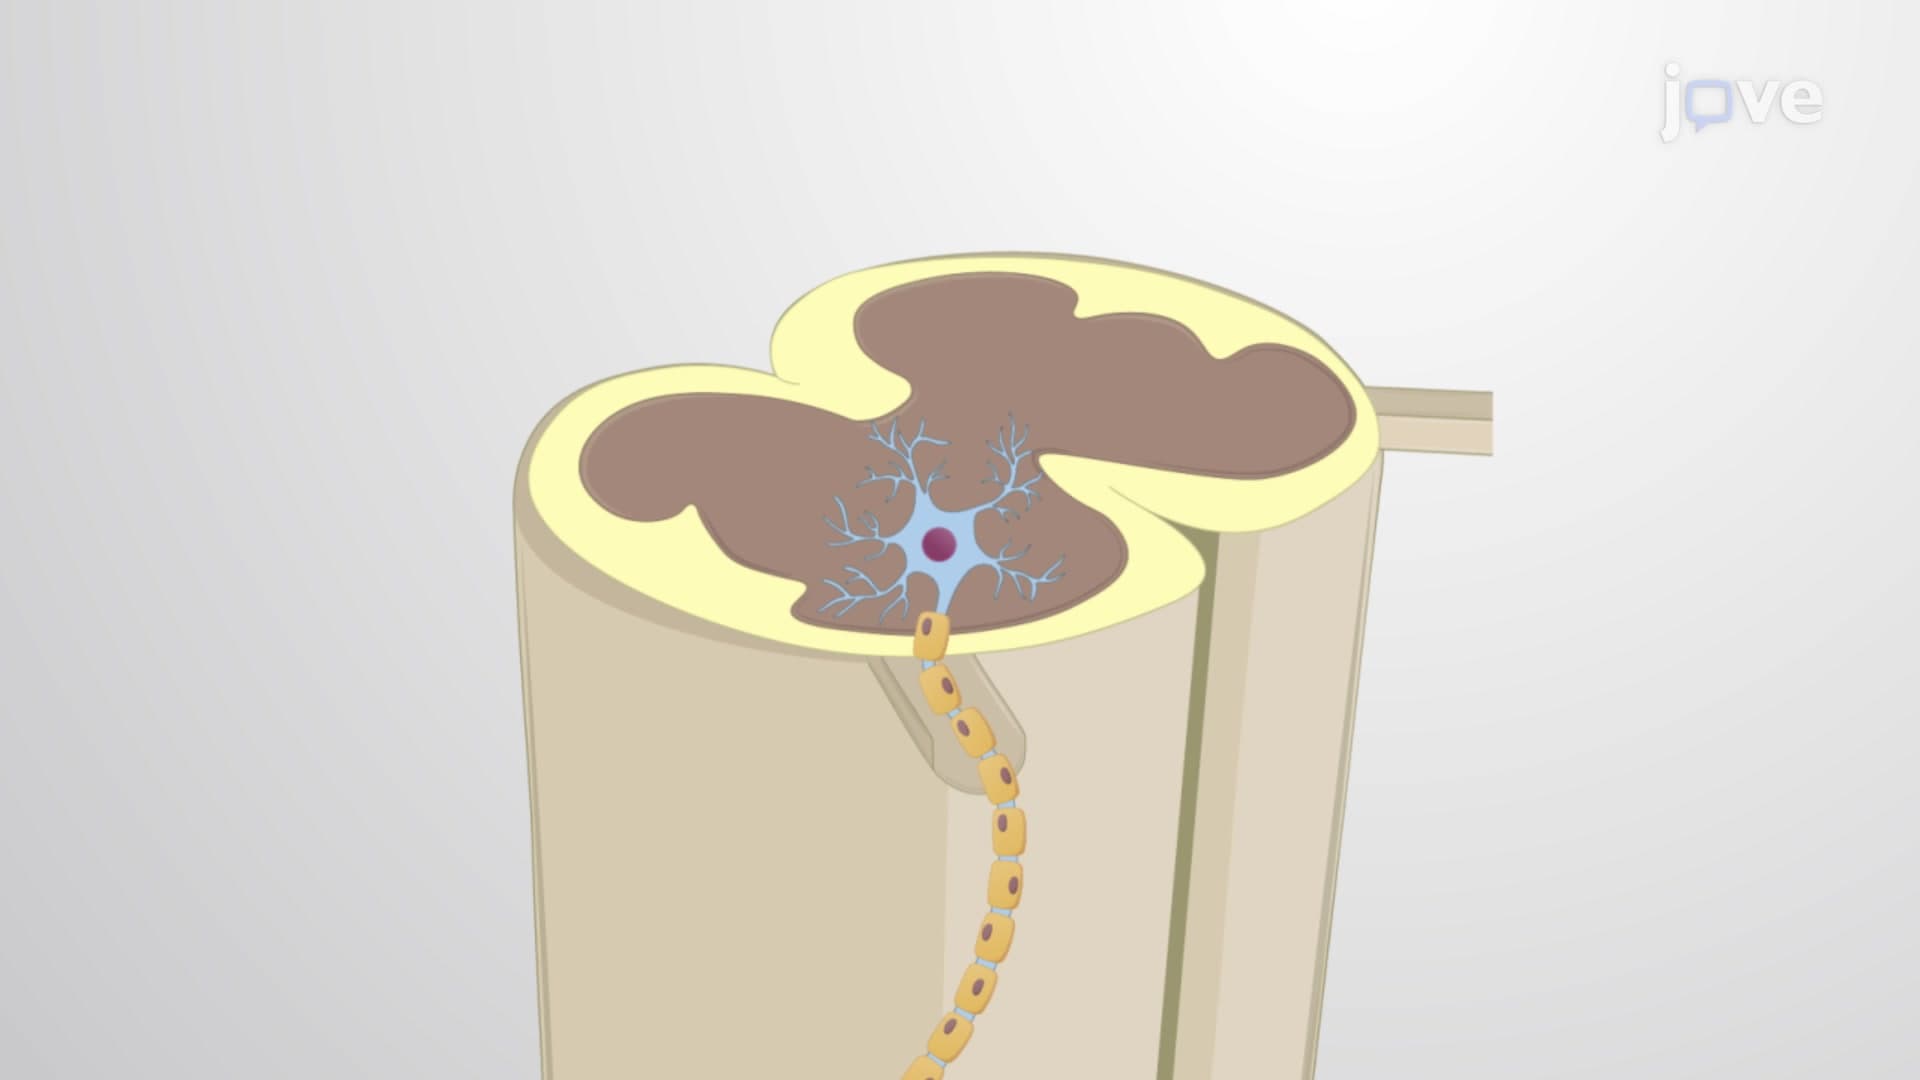
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:24
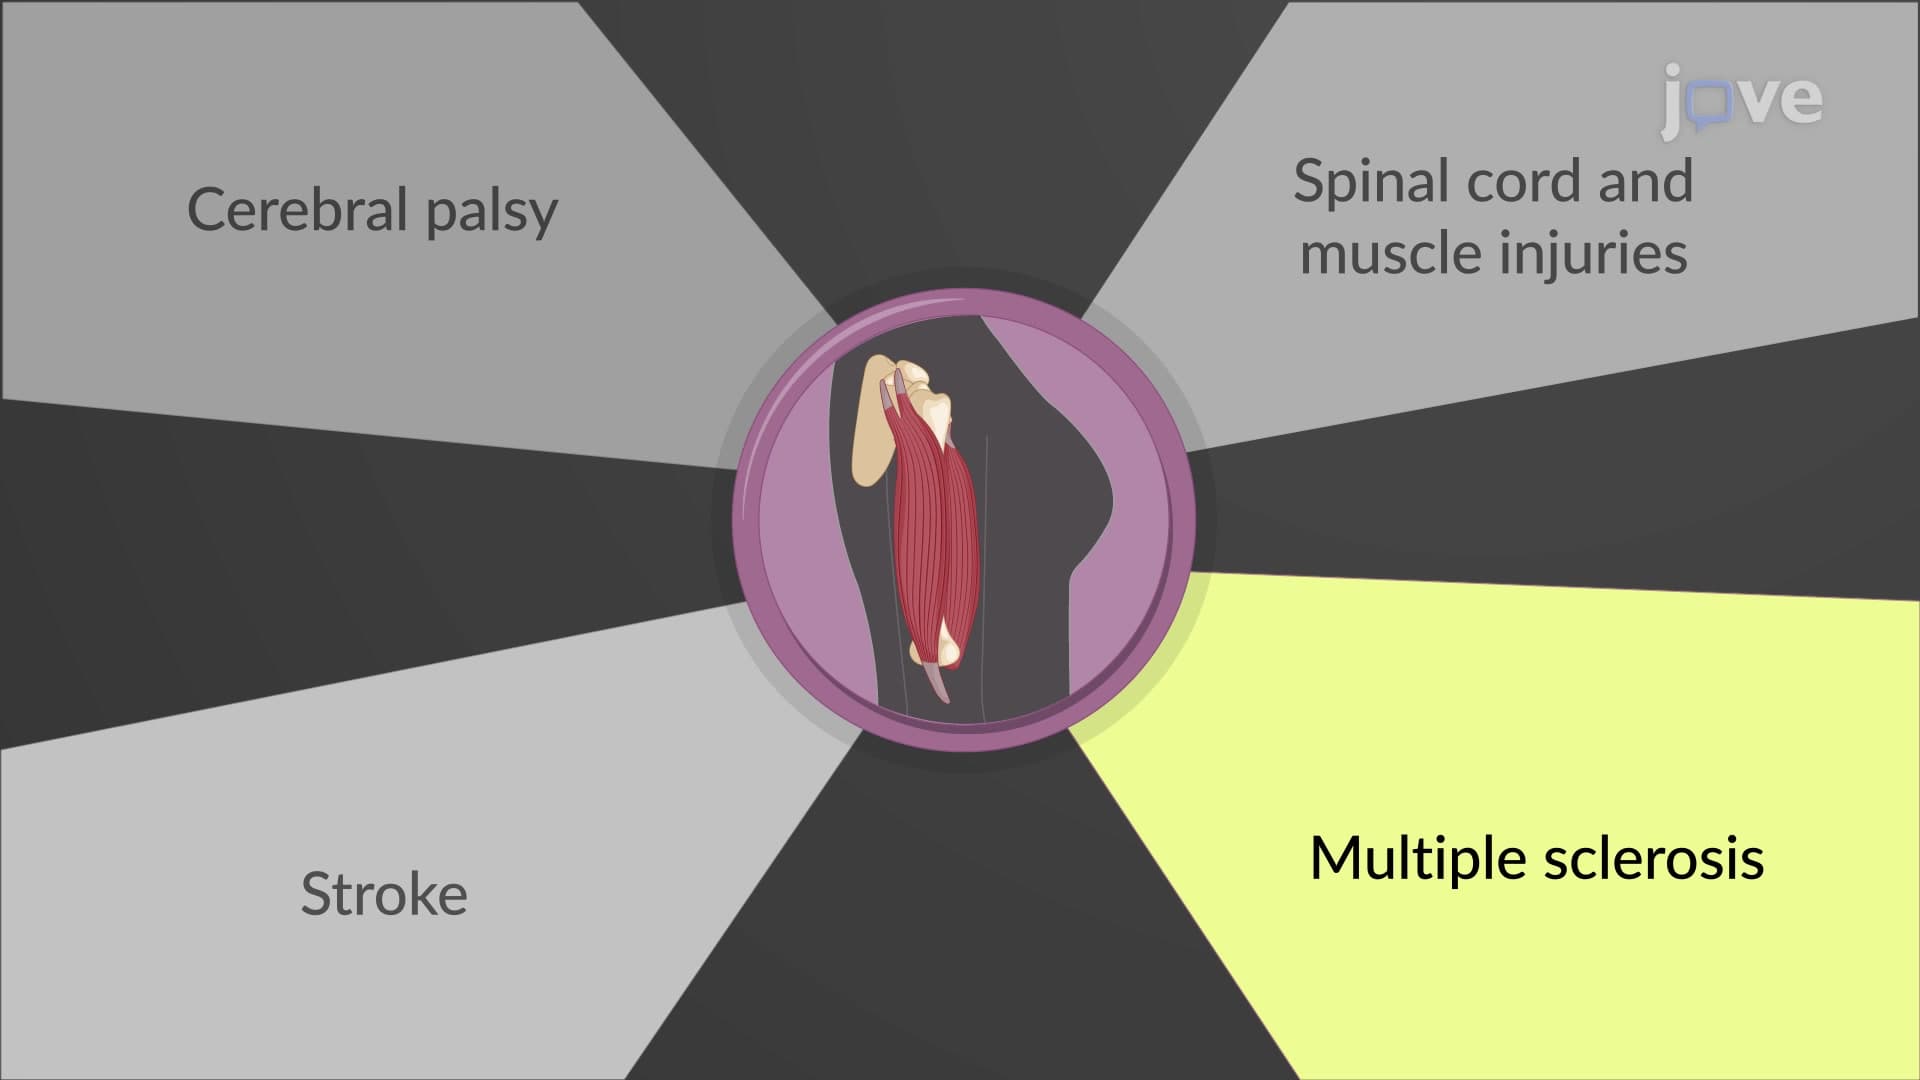
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...