Related Experiment Video
Updated: Apr 30, 2026
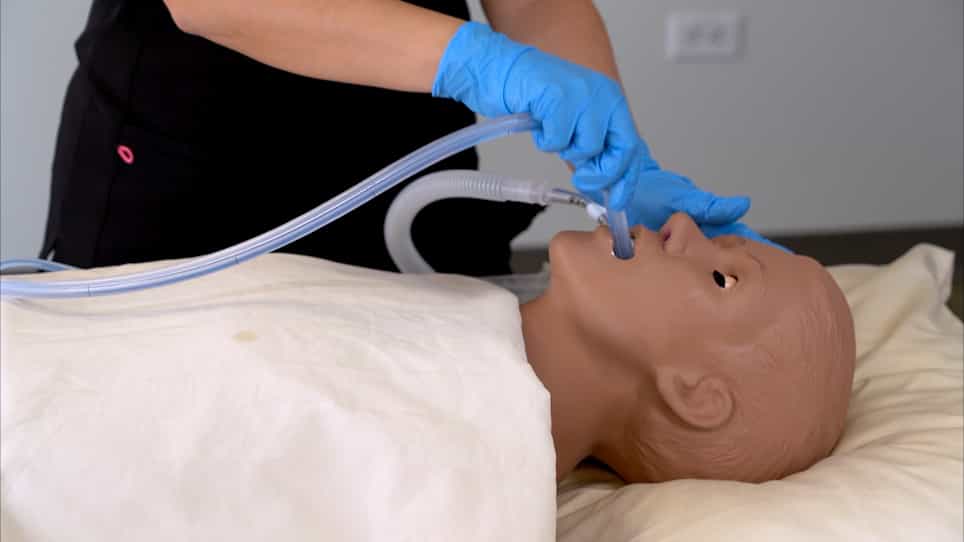

Reduced Procedure Time and Variability with Active Esophageal Cooling During Radiofrequency Ablation for Atrial Fibrillation
Published on: August 25, 2022
Durability and predictors of successful radiofrequency ablation for Barrett's esophagus
Sarina Pasricha1, William J Bulsiewicz1, Kelly E Hathorn1
1Center for Esophageal Diseases and Swallowing, Division of Gastroenterology and Hepatology, University of North Carolina at Chapel Hill, Chapel Hill, North Carolina.

Background & Aims:
After radiofrequency ablation (RFA), patients may experience recurrence of Barrett's esophagus (BE) after complete eradication of intestinal metaplasia (CEIM). Rates and predictors of recurrence after successful eradication have been poorly described.
Methods:
We used the US RFA Registry, a nationwide registry of BE patients receiving RFA, to determine rates and factors that predicted recurrence of intestinal metaplasia (IM). We assessed recurrence by Kaplan-Meier analysis for the overall cohort and by worst pretreatment histology. Characteristics associated with recurrence were included in a logistic regression model to identify independent predictors.
Results:
Among 5521 patients, 3728 had biopsies 12 months or more after initiation of RFA. Of these, 3169 (85%) achieved CEIM, and 1634 (30%) met inclusion criteria. The average follow-up period was 2.4 years after CEIM. IM recurred in 334 (20%) and was nondysplastic or indefinite for dysplasia in 86% (287 of 334); the average length of recurrent BE was 0.6 cm. In Kaplan-Meier analysis, more advanced pretreatment histology was associated with an increased yearly recurrence rate. Compared with patients without recurrence, patients with recurrence were more likely, based on bivariate analysis, to be older, have longer BE segments, be non-Caucasian, have dysplastic BE before treatment, and require more treatment sessions. In multivariate analysis, the likelihood for recurrence was associated with increasing age and BE length, and non-Caucasian race.
Conclusions:
BE recurred in 20% of patients followed up for an average of 2.4 years after CEIM. Most recurrences were short segments and were nondysplastic or indefinite for dysplasia. Older age, non-Caucasian race, and increasing length of BE length were all risk factors. These risk factors should be considered when planning post-RFA surveillance intervals.
More Related Videos
 06:25
Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
 05:43
Author Spotlight: Improving Lesion Contiguity in Pulmonary Vein Isolation via Proactive Esophageal Cooling
Published on: April 19, 2024
Related Concept Videos
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Gastroesophageal Reflux Disease