Postoperative intussusception in a neonate with congenital cutis laxa and huge hiatal hernia

Mohajerzadeh Leily1, Sadeghian Naser1, Mirshemirani Aliraza1

  • 1Pediatric Surgery Research Center, Shahid Beheshti University of Medical Sciences, Tehran, Iran.

Related Concept Videos

Hiatal Hernia01:25

Hiatal Hernia

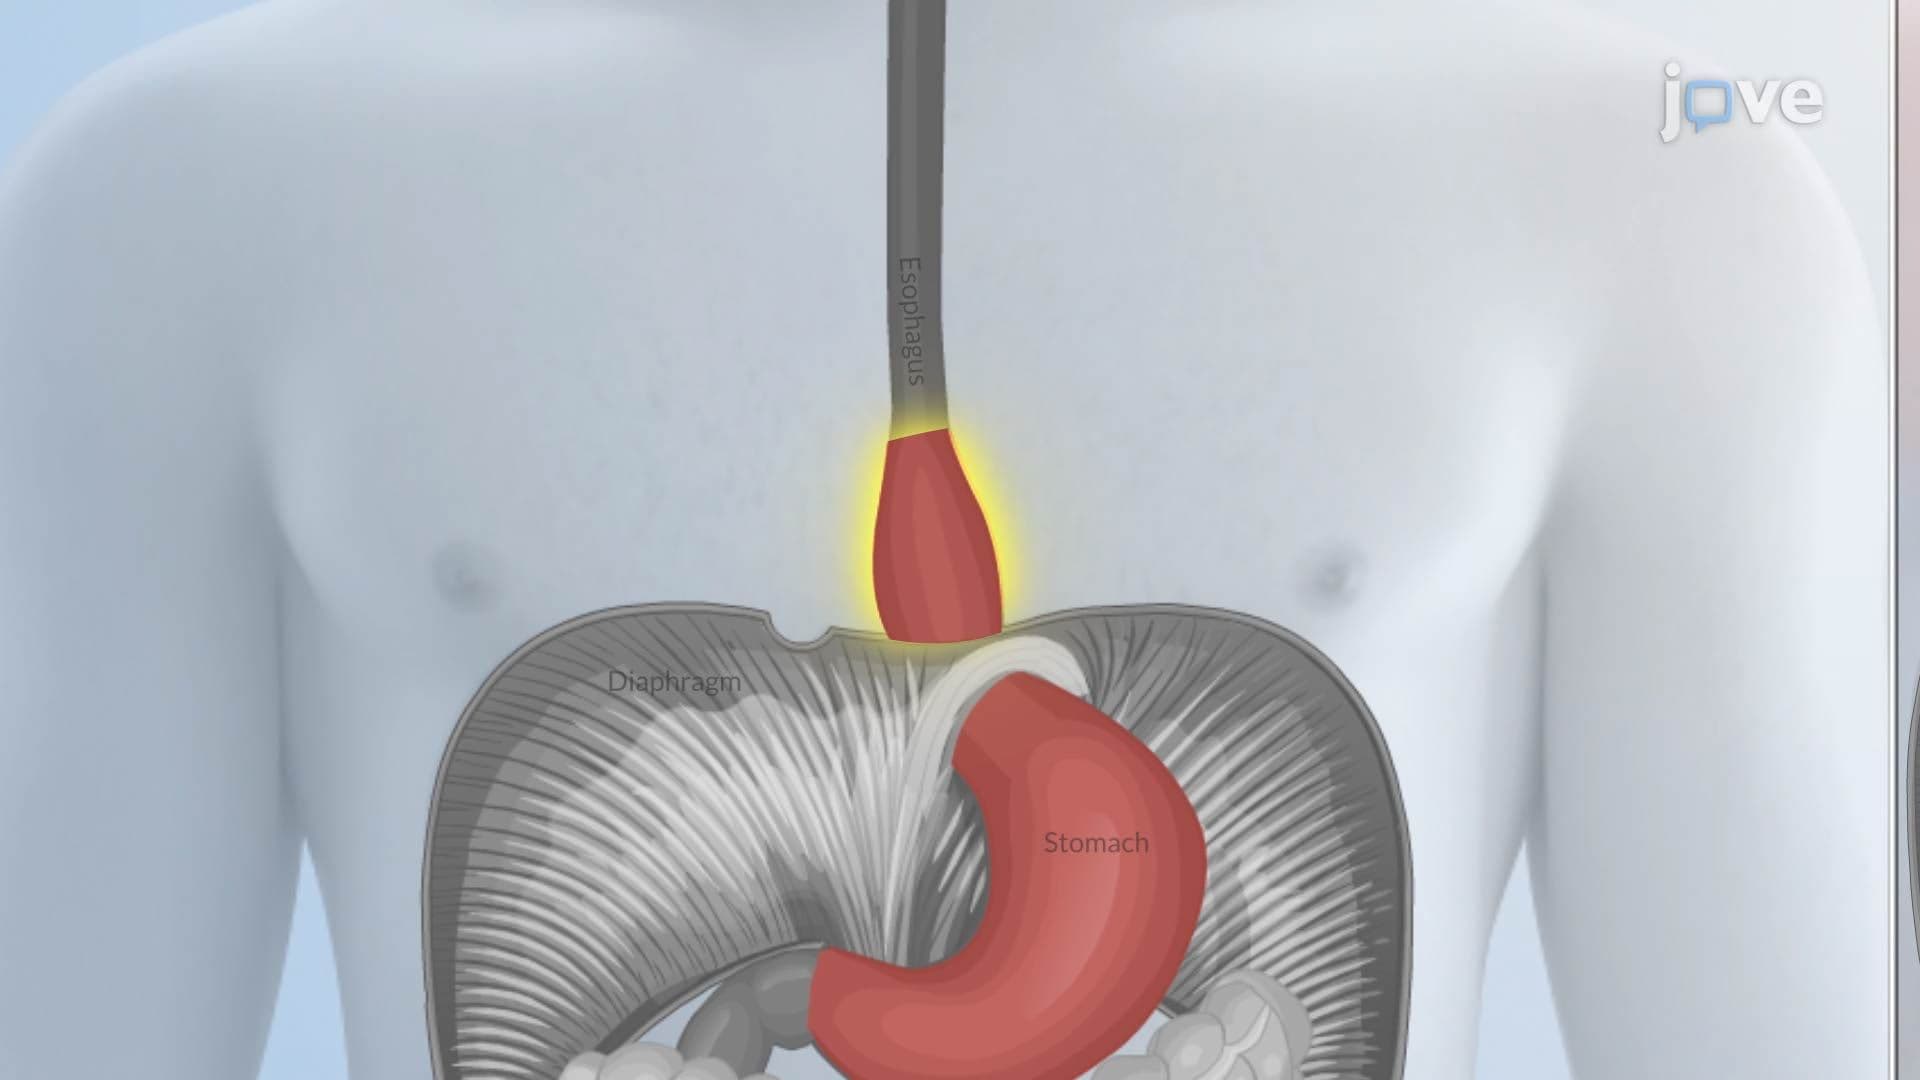
A hiatal hernia is the abnormal protrusion of the stomach or other abdominal organs through the esophageal hiatus of the diaphragm into the thoracic cavity.Normally, the gastroesophageal junction (GEJ) lies below the diaphragm and is supported by the phrenoesophageal membrane, the diaphragmatic crura, and connective tissues. Weakening of these structures—due to aging, congenital defects like a short esophagus, or increased intra-abdominal pressure from coughing, obesity, pregnancy, or...
80
Inflammatory Bowel Disease V: Surgical Management01:21

Inflammatory Bowel Disease V: Surgical Management

Surgical interventions for inflammatory bowel disease (IBD), which includes ulcerative colitis and Crohn's disease, are essential in managing symptoms and addressing complications. The selection of surgical procedures is contingent upon the specific conditions and complications that stem from these illnesses.
Here are some common surgical interventions for IBD:
915
Intestinal Obstruction I: Introduction01:29

Intestinal Obstruction I: Introduction

Intestinal obstruction is a partial or complete blockage of the small or large intestine that disrupts the normal flow of intestinal contents through the lumen. This interruption impairs digestion, absorption, and fluid balance, and may lead to serious complications if not treated promptly.Mechanical ObstructionMechanical obstruction occurs when a physical blockage prevents intestinal contents from passing, arising from within the lumen or the bowel wall, or from external compression.Adhesions,...
48
Intestinal Obstruction II: Pathophysiology01:07

Intestinal Obstruction II: Pathophysiology

Intestinal obstruction triggers a series of physiological responses, starting with gas and fluid accumulation in the bowel segment proximal to the obstruction, leading to distension. This distended intestine compresses the diaphragm, hindering lung expansion and potentially leading to reduced respiratory effort, atelectasis, and pneumonia.To overcome the blockage, the gut intensifies contractions, causing colicky abdominal pain, nausea, and vomiting, which reduces fluid and food intake and...
42
Esophageal Strictures-I: Introduction01:30

Esophageal Strictures-I: Introduction

Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
1.3K
Esophageal Strictures-II: Clinical Features and Management01:26

Esophageal Strictures-II: Clinical Features and Management

Patients with esophageal strictures often experience a range of symptoms. Initially, they may have difficulty swallowing solid foods, which can progress to include liquids. Additional symptoms may involve chest pain or discomfort, regurgitating food and fluids, heartburn, unintentional weight loss, coughing or choking during meals, and hoarseness.
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
1.1K