Related Experiment Video
Updated: Apr 28, 2026
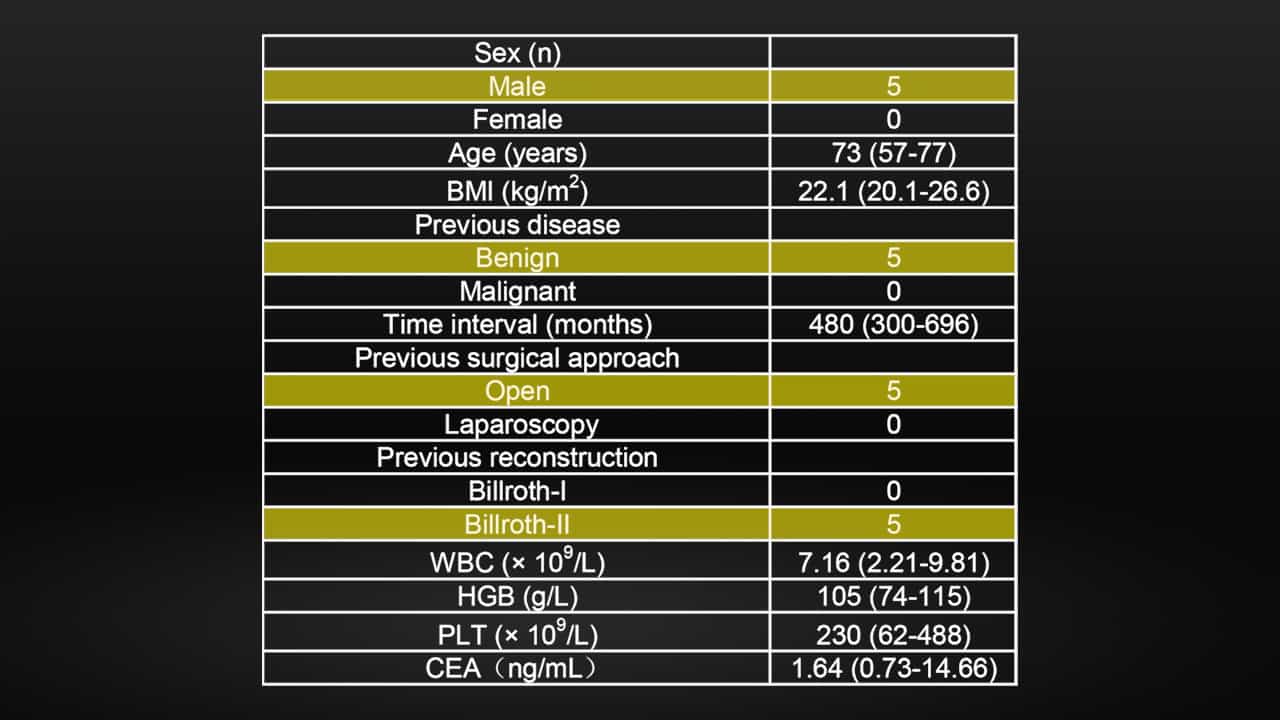

Laparoscopic Radical Gastrectomy for Remnant Gastric Cancer
Published on: October 31, 2025
Should peri-gastrectomy gastric acidity be our focus among gastric cancer patients?
Lei Huang1, A-Man Xu1, Tuan-Jie Li1
1Lei Huang, A-Man Xu, Wen-Xiu Han, Jing Xu, Department of General Surgery, the First Affiliated Hospital of Anhui Medical University, Hefei 230022, Anhui Province, China.

Aim:
To investigate the necessity and correctness of acid suppression pre- and post-gastrectomy among gastric carcinoma (GC) patients.
Methods:
From June 2011 to April 2013, 99 patients who were diagnosed with GC or adenocarcinoma of the gastroesophageal junction (type II or III) and needed surgical management were enrolled. They all underwent gastrectomy by the same operators [35 undergoing total gastrectomy (TG) plus Roux-en-Y reconstruction, 34 distal gastrectomy (DG) plus Billroth I reconstruction, and 30 proximal gastrectomy (PG) plus gastroesophagostomy]. We collected and analyzed their gastrointestinal juice and tissues from the pre-operational day to the 5(th) day post-operation, and 6 mo post-surgery. Gastric pH was detected with a precise acidity meter. Gastric juice contents including potassium, sodium and bicarbonate ions, urea nitrogen, direct and indirect bilirubin, and bile acid were detected using Automatic Biochemical Analyzer. Data regarding tumor size, histological type, tumor penetration and tumor-node-metastasis (TNM) stage were obtained from the pathological records. Reflux symptoms pre- and 6 mo post-gastrectomy were evaluated by reflux disease questionnaire (RDQ) and gastroesophageal reflux disease questionnaire (GERD-Q). SPSS 16.0 was applied to analyze the data.
Results:
Before surgery, gastric pH was higher than the threshold of hypoacidity (4.25 ± 1.45 vs 3.5, P = 0.000), and significantly affected by age, tumor size and differentiation grade, and potassium and bicarbonate ions; advanced malignancies were accompanied with higher pH compared with early ones (4.49 ± 1.31 vs 3.66 ± 1.61, P = 0.008). After operation, gastric pH in all groups was of weak-acidity and significantly higher than that pre-gastrectomy; on days 3-5, comparisons of gastric pH were similar between the 3 groups. Six months later, gastric pH was comparable to that on days 3-5; older patients were accompanied with higher total bilirubin level, indicating more serious reflux (r = 0.238, P = 0.018); the TG and PG groups had higher RDQ (TG vs DG: 15.80 ± 5.06 vs 12.26 ± 2.14, P = 0.000; PG vs DG: 15.37 ± 3.49 vs 12.26 ± 2.14, P = 0.000) and GERD-Q scores (TG vs DG: 10.54 ± 3.16 vs 9.15 ± 2.27, P = 0.039; PG vs DG: 11.00 ± 2.07 vs 9.15 ± 2.27, P = 0.001) compared with the DG group; all gastric juice contents except potassium ion significantly rose; reflux symptom was significantly associated with patient's body mass index, direct and indirect bilirubin, and total bile acid, while pH played no role.
Conclusion:
Acidity is not an important factor causing unfitness among GC patients. There is no need to further alkalify gastrointestinal juice both pre- and post-gastrectomy.
More Related Videos
 05:16
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
 03:32
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:26
Gastritis II: Pathophysiology
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:29
Gastroesophageal Reflux Disease I: Meaning and Pathophysiology