Related Experiment Video
Updated: Apr 27, 2026
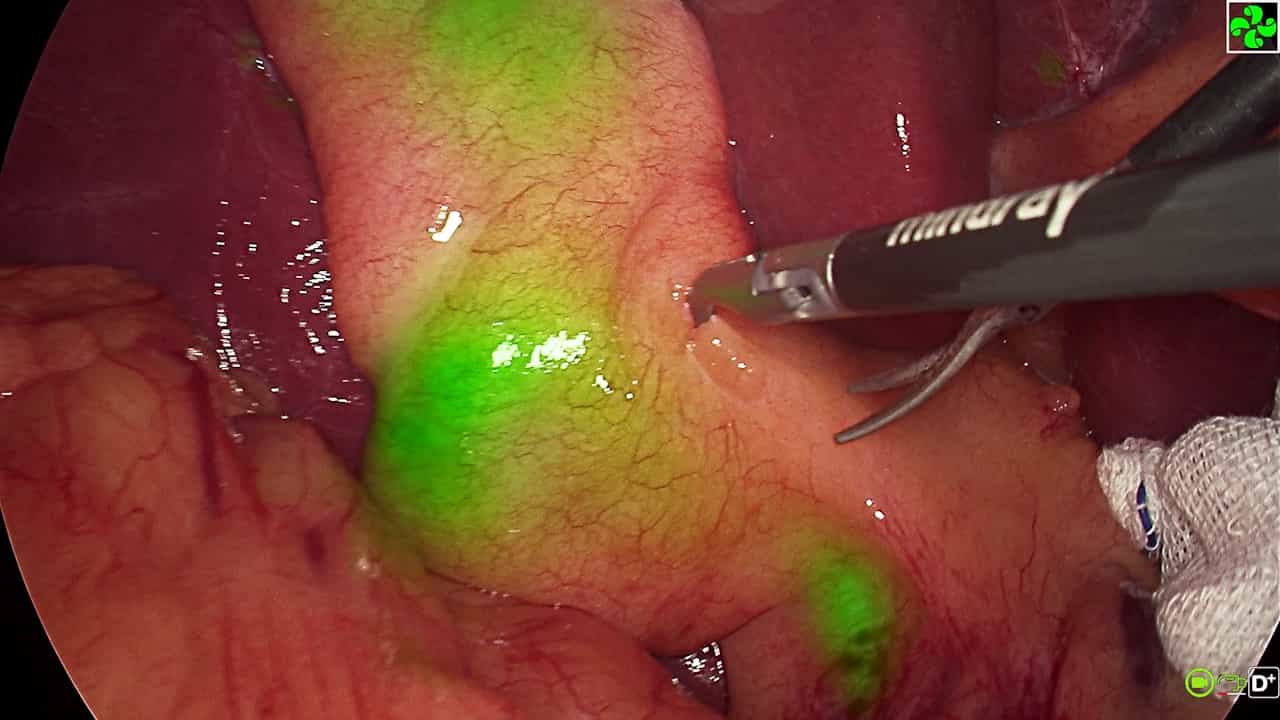

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Identifying patients most likely to have a common bile duct stone after a positive intraoperative cholangiogram
Raja Vadlamudi1, Jason Conway1, Girish Mishra1
1Dr Vadlamudi is a gastroenterology fellow in the Department of Medicine at SUNY Upstate Medical University in Syracuse, New York. Drs Conway, Mishra, Gilliam, Fernandez, and Evans are affiliated with the Wake Forest School of Medicine in Winston-Salem, North Carolina. Dr Conway is an assistant professor of internal medicine, director of Endoscopic Ultrasound Services and the Advanced Endoscopy Fellowship Program in the Department of Internal Medicine; Dr Mishra is an associate professor of medicine, director of Endoscopy & Clinical Services, and vice chief of the Division of Gastroenterology; Drs Gilliam and Evans are assistant professors of medicine in the Division of Gastroenterology; and Dr Fernandez is an associate professor of surgery in the Department of General Surgery. Dr Baillie is the director of medical gastro-enterology at the Carteret Medical Group in Morehead City, North Carolina.

Abstract:
The false-positive rates of a positive intraoperative cholangiogram (IOC) are as high as 60%. Endoscopic retrograde cholangiopancreatography (ERCP) for stone removal is required after a positive IOC. It is unclear which clinical factors identify patients most likely to have a stone after a positive IOC. This study was conducted to identify factors predictive of common bile duct (CBD) stone(s) on ERCP after a positive IOC. A retrospective review of our endoscopic database identified all ERCP and/or endoscopic ultrasound (EUS) procedures performed for a positive IOC between August 2003 and August 2009. Collected data included patient demographics; indication for cholecystectomy; IOC findings; blood tests before and after cholecystectomy, including liver function tests, complete blood count, and amylase and lipase measurements; and ERCP and/or EUS results. Patients who had a negative EUS for CBD stones and no subsequent ERCP were contacted by phone to see if they eventually required an ERCP. Univariate and multi-variable analyses were performed. A total of 114 patients were included in the study. IOC findings included a single stone, multiple stones, nonpassage of contrast into the duodenum, dilated CBD, and poor visualization of the bile duct. Eighty-four percent of patients had ERCP only, 9% had EUS only, and 7% had EUS followed by ERCP. Sixty-five patients (57%) had CBD stones on ERCP or EUS. Older age, multiple stones, dilated CBD on IOC, and elevated postcholecystectomy bilirubin levels were the clinical variables with statistically significant differences on univariate analysis. On multivariable analysis, older age and elevated postcholecystectomy total bilirubin levels correlated with the presence of CBD stones on ERCP. Fifty-seven percent of patients referred for endoscopic evaluation after a positive IOC had CBD stones on ERCP. Patients with CBD stones after a positive IOC were more likely to be older with elevated post-cholecystectomy total serum bilirubin levels.

Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:20
Cholecystitis