Related Experiment Video
Updated: Apr 26, 2026


Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Electrocardiographic difference between ventricular arrhythmias from the right ventricular outflow tract and
1Cardiac Arrhythmia Center, State Key Laboratory of Cardiovascular Disease, Fuwai Hospital, National Center for Cardiovascular Diseases, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, People's Republic of China.

Background:
Ventricular arrhythmias (VA) arising from arrhythmogenic right ventricular dysplasia/cardiomyopathy (ARVD/C) and idiopathic right ventricular outflow tract ventricular arrhythmias (RVOT-VA) share the pattern of left bundle branch block (LBBB)/inferior axis. The existence of QRS notching showed a discriminating effect of the two conditions in recent research; however, there are little data regarding the difference in the distribution of QRS notching. The aim of this study was to compare the VA morphology between the two conditions, especially evaluating the diagnostic role of QRS notching.
Methods:
Electrocardiographic (ECG) recordings of VA episode with LBBB/inferior axis of 16 ARVD/C and 45 idiopathic RVOT-VA patients (30 originated from the septum, 15 from the free-wall) were gathered and compared.
Results:
ARVD/C had longer mean QRS duration in all 12 leads, and significant differences existed in leads Ⅰ,Ⅱ,Ⅲ, aVL, aVF, and V1 (P < 0.05). Lead Ⅰ had the largest mean difference of 25.1 ± 5.8 ms. In addition, ARVD/C had more R-wave transition in lead V5 or later (37.5% vs 8.9%, P < 0.01).The presence of QRS notching (15/16 [93.8%] vs 36/45 [80.0%], P = 0.20) and the total number of leads expressing notching (2.88 ± 2.0 vs 2.80 ± 2.0, P = 0.90) were not different between ARVD/C and idiopathic RVOT-VA. However, QRS notching existing simultaneously in leads I and aVL was more common in ARVD/C (43.8% vs13.3%, P = 0.011).
Conclusion:
Longer QRS duration, later precordial R/S transition, and QRS notching in lateral leads (leads Ⅰ and aVL) are useful in discriminating ARVD/C from idiopathic RVOT-VA.
More Related Videos
 08:19
Electrophysiological Assessment of Murine Atria with High-Resolution Optical Mapping
Published on: February 22, 2018
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:28
Mechanism of Cardiac Arrhythmias
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
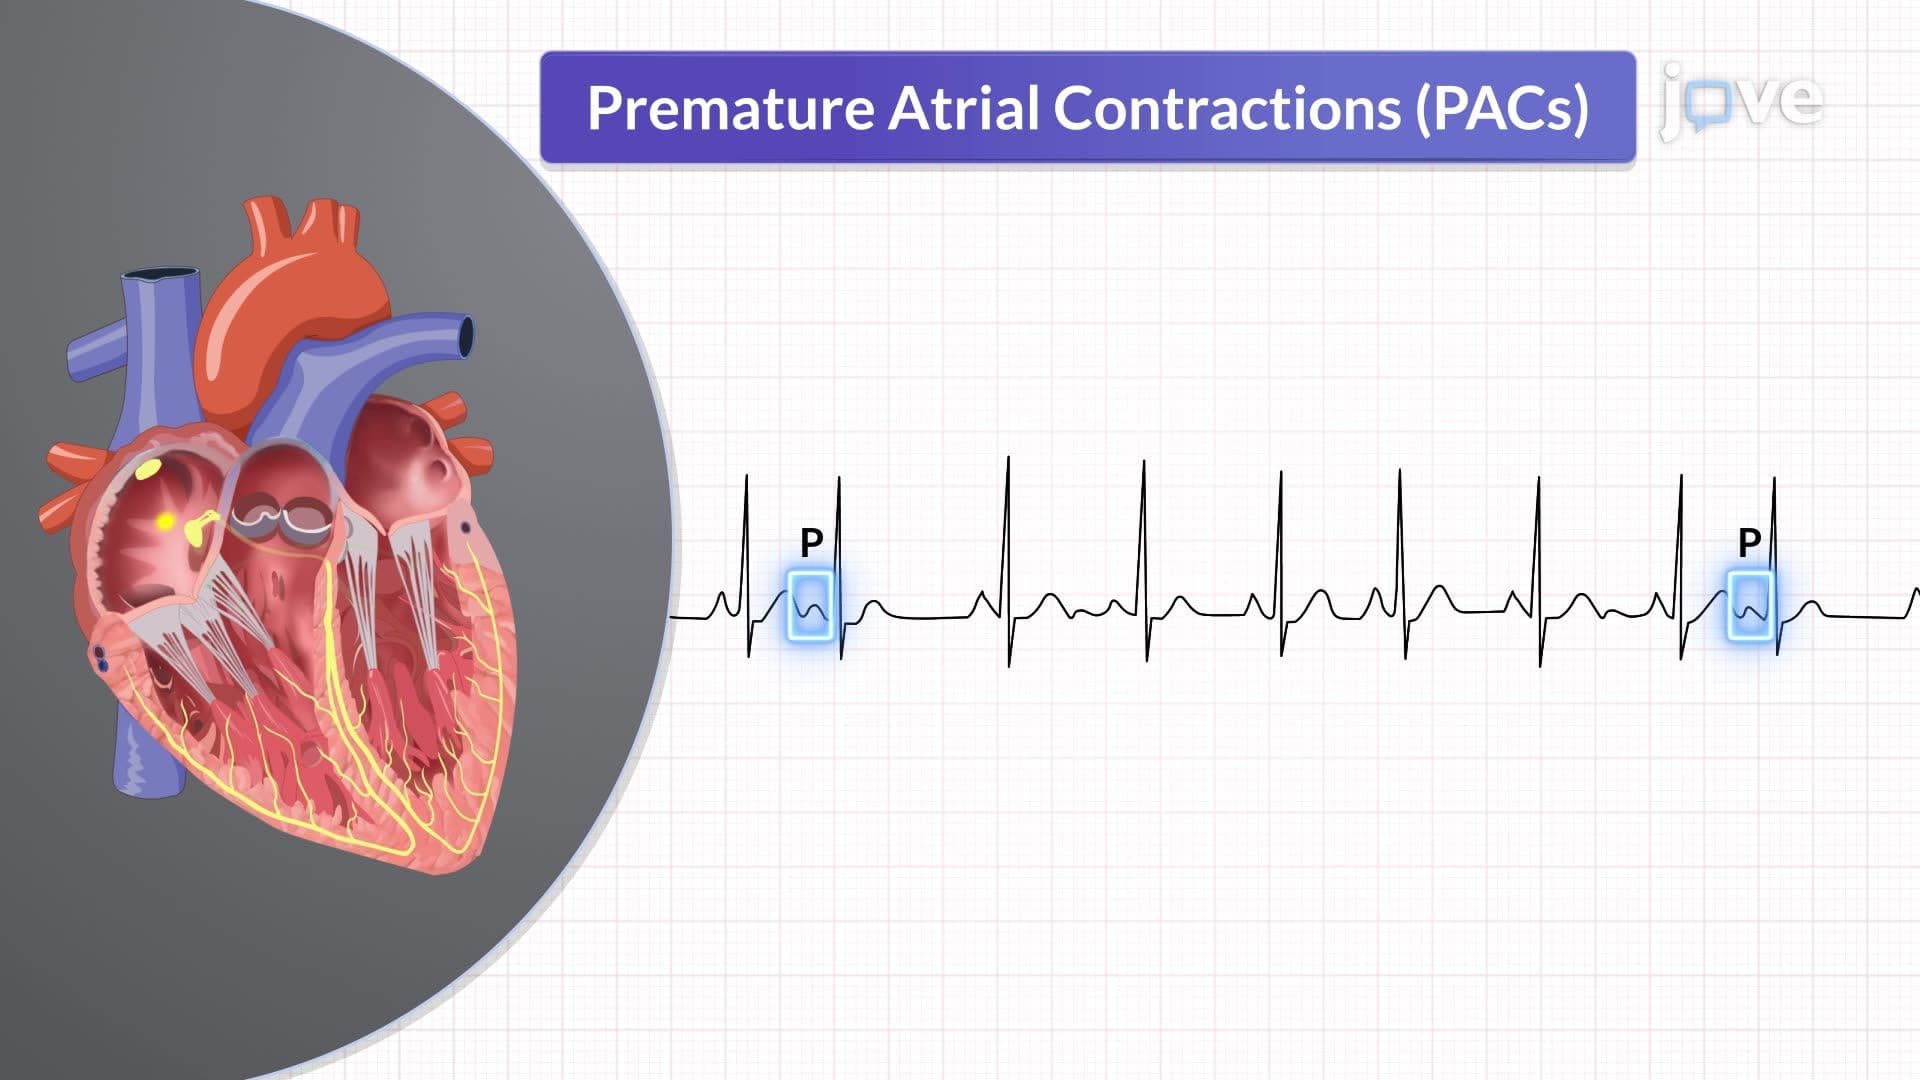 01:29
Dysrhythmias III: Characteristics of Dysrhythmias