Related Experiment Video
Updated: Apr 26, 2026

Modeling Posthemorrhagic Hydrocephalus of Prematurity in Rats
Published on: March 28, 2025
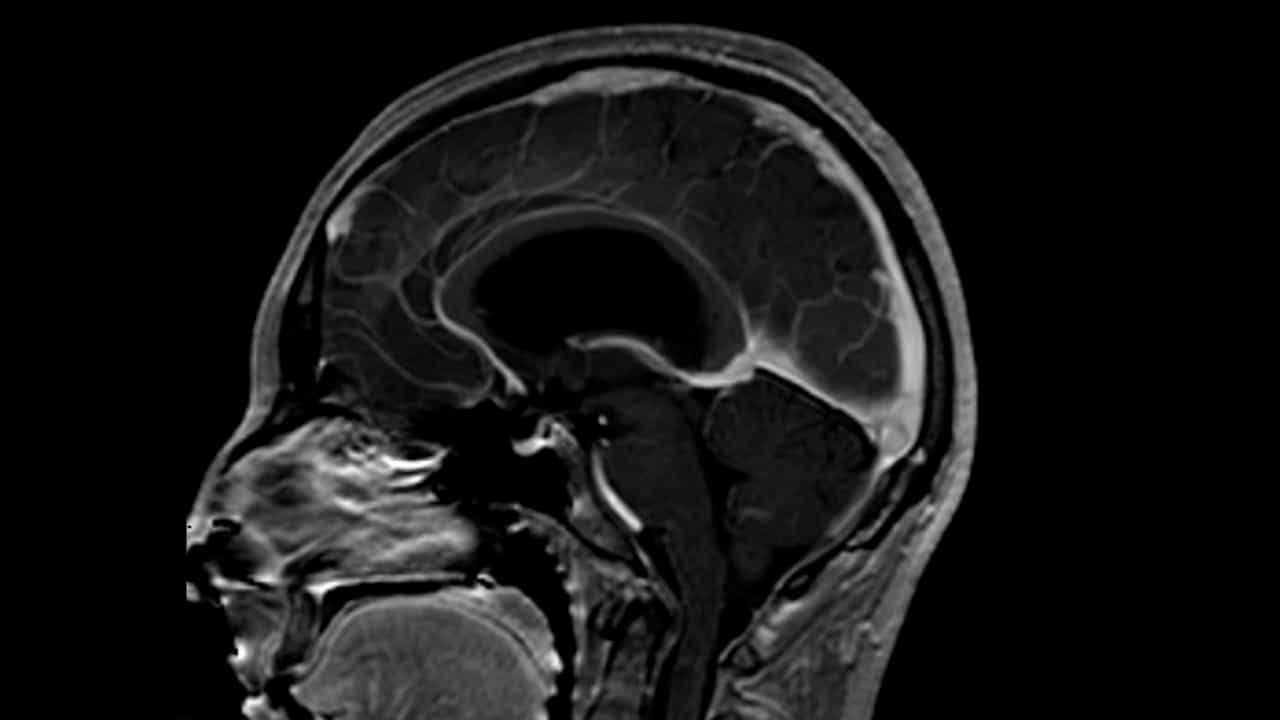
Retroclival arachnoid cyst in a preterm infant after ventriculitis and intraventricular hemorrhage-a case report
Matthias Preuß1, Ulrich Thome, Jens Kluge
1Department of Neurosurgery, Pediatric Neurosurgery, University Hospital Leipzig, Liebigstrasse 20, 04103, Leipzig, Germany, preuss@neurosurgeon.ch.

Insights
A preterm infant with complex hydrocephalus and a retroclival cyst underwent successful endoscopic surgery. This treatment established drainage, resolving the brainstem compression and leading to normal development.
Area of Science:
- Pediatric Neurosurgery
- Neuroendoscopy
- Hydrocephalus Management
Background:
- Posthemorrhagic hydrocephalus is a significant complication in preterm infants.
- Retroclival cysts can cause severe neurological deficits due to brainstem compression.
Observation:
- A 29-gestational-week preterm infant presented with complicated hydrocephalus and a retroclival cyst.
- Initial endoscopic third ventriculocisternocystostomy (ETVCC) provided temporary relief but failed due to stoma reclosure.
Findings:
- A second, navigated endoscopic ventriculocisternocystostomy with stent catheter placement connected to a ventriculoperitoneal (VP) shunt was performed.
- This procedure successfully created a communication between the retroclival cyst and the ventricular system, addressing multiloculated hydrocephalus.
Implications:
- This minimally invasive endoscopic strategy effectively treated a complex case of hydrocephalus with a retroclival cyst.
- The successful intervention facilitated the child's uneventful neurodevelopmental progression.
Discussion:
We present a case of a preterm boy of 29 gestational weeks with complicated posthemorrhagic hydrocephalus who developed a retroclival cyst extending to the upper cervical spinal canal and leading to brainstem compression. At the age of 2 months, third ventriculocisternocystostomy (ETVCC) resulted in temporary relief but was followed by reclosure of the stoma within weeks. At the age of 4 months, navigated endoscopic ventriculocisternocystostomy and endoscopy-guided stent catheter placement was performed with connection to a ventriculoperitoneal (VP) shunt system through a burr hole reservoir.
Conclusion:
This strategy improved the multiloculated hydrocephalus by establishing a communication between theretroclival subarachnoid cyst and the ventricular system, leading to uneventful further development of the child.