Related Experiment Video
Updated: Apr 25, 2026


Potentiodynamic Corrosion Testing
Published on: September 4, 2016
Systemic toxicity related to metal hip prostheses
S M Bradberry1, J M Wilkinson, R E Ferner
1West Midlands Poisons Unit, City Hospital , Birmingham , UK.

Introduction:
One in eight of all total hip replacements requires revision within 10 years, 60% because of wear-related complications. The bearing surfaces may be made of cobalt/chromium, stainless steel, ceramic, or polyethylene. Friction between bearing surfaces and corrosion of non-moving parts can result in increased local and systemic metal concentrations.
Objectives:
To identify and systematically review published reports of systemic toxicity attributed to metal released from hip implants and to propose criteria for the assessment of these patients.
Methods:
Medline (from 1950) and Embase (from 1980) were searched to 28 February 2014 using the search terms (text/abstract) chrom* or cobalt* and [toxic* or intox* or poison* or adverse effect or complication] and [prosthes* or 'joint replacement' or hip or arthroplast*] and PubMed (all available years) was searched using the search term (("Chromium/adverse effects"[Mesh] OR "Chromium/poisoning"[Mesh] OR "Chromium/toxicity"[Mesh]) OR ("Cobalt/adverse effects"[Mesh] OR "Cobalt/poisoning"[Mesh] OR "Cobalt/toxicity"[Mesh])) AND ("Arthroplasty, Replacement, Hip"[Mesh] OR "Hip Prosthesis"[Mesh]). These searches identified 281 unique references, of which 23 contained original case data. Three further reports were identified from the bibliographies of these papers. As some cases were reported repeatedly the 26 papers described only 18 individual cases. Systemic toxicity. Ten of these eighteen patients had undergone revision from a ceramic-containing bearing to one containing a metal component. The other eight had metal-on-metal prostheses. Systemic toxicity was first manifest months and often several years after placement of the metal-containing joint. The reported systemic features fell into three main categories: neuro-ocular toxicity (14 patients), cardiotoxicity (11 patients) and thyroid toxicity (9 patients). Neurotoxicity was manifest as peripheral neuropathy (8 cases), sensorineural hearing loss (7) and cognitive decline (5); ocular toxicity presented as visual impairment (6). All these neurological features, except cognitive decline, have been associated with cobalt poisoning previously. Type of prosthesis and blood metal concentrations. Where blood or serum metal concentrations were reported (n = 17 for cobalt and n = 14 for chromium), the median cobalt concentration was 398 (range, 13.6-6521) μg/L and the median chromium concentration was 48 μg/L (in whole blood) (range, 4.1-221 μg/L including serum and blood values). Those patients reported to have systemic features who had received a metal-on-metal prosthesis (n = 8) had a median peak blood cobalt concentration of 34.5 (range, 13.6-398.6) μg/L; those with a metal-containing revision of a failed ceramic prosthesis (n = 10) had a median blood cobalt concentration of 506 (range, 353-6521) μg/L. Management. The most common treatment was removal of the metal-containing prosthesis, undertaken in all but 2 patients. This was usually associated with a fall in circulating cobalt concentration and improvement in some or all features. Clinical and toxicological assessment of systemic features. We propose the following criteria for assessing the likelihood that clinical features are related to cobalt toxicity: clinical effects consistent with the known neurological, cardiac, or thyroidal effects of cobalt, and for which any other explanation is less likely; increased blood cobalt concentrations (substantially higher than those in patients with well-functioning prostheses) several months after hip replacement; a fall in the blood cobalt concentration, usually accompanied by signs of improvement in features. When judged by these criteria, the systemic features in 10 of the reported cases are likely to be related to cobalt exposure from a metal-containing hip prosthesis.
Conclusions:
Rarely, patients exposed to high circulating concentrations of cobalt from failed hip replacements develop neurological damage, hypothyroidism and/or cardiomyopathy, which may not resolve completely even after removal of the prosthesis. The greatest risk of systemic cobalt toxicity seems to result from accelerated wear of a cobalt-containing revision of a failed ceramic prosthesis, rather than from primary failure of a metal-on-metal prosthesis.
More Related Videos
 09:08
Biotribological Testing and Analysis of Articular Cartilage Sliding against Metal for Implants
Published on: May 14, 2020
 08:19
Protocol for the Evaluation of MRI Artifacts Caused by Metal Implants to Assess the Suitability of Implants and the Vulnerability of Pulse Sequences
Published on: May 17, 2018
Related Concept Videos
 01:26
Toxic Reactions: Overview
Toxicity falls into two primary categories: local and systemic.
Local toxicity appears at the exposure site, such as protein denaturation caused by caustic substances.
In contrast, systemic toxicity requires the toxic agent's absorption and distribution,...
 00:57
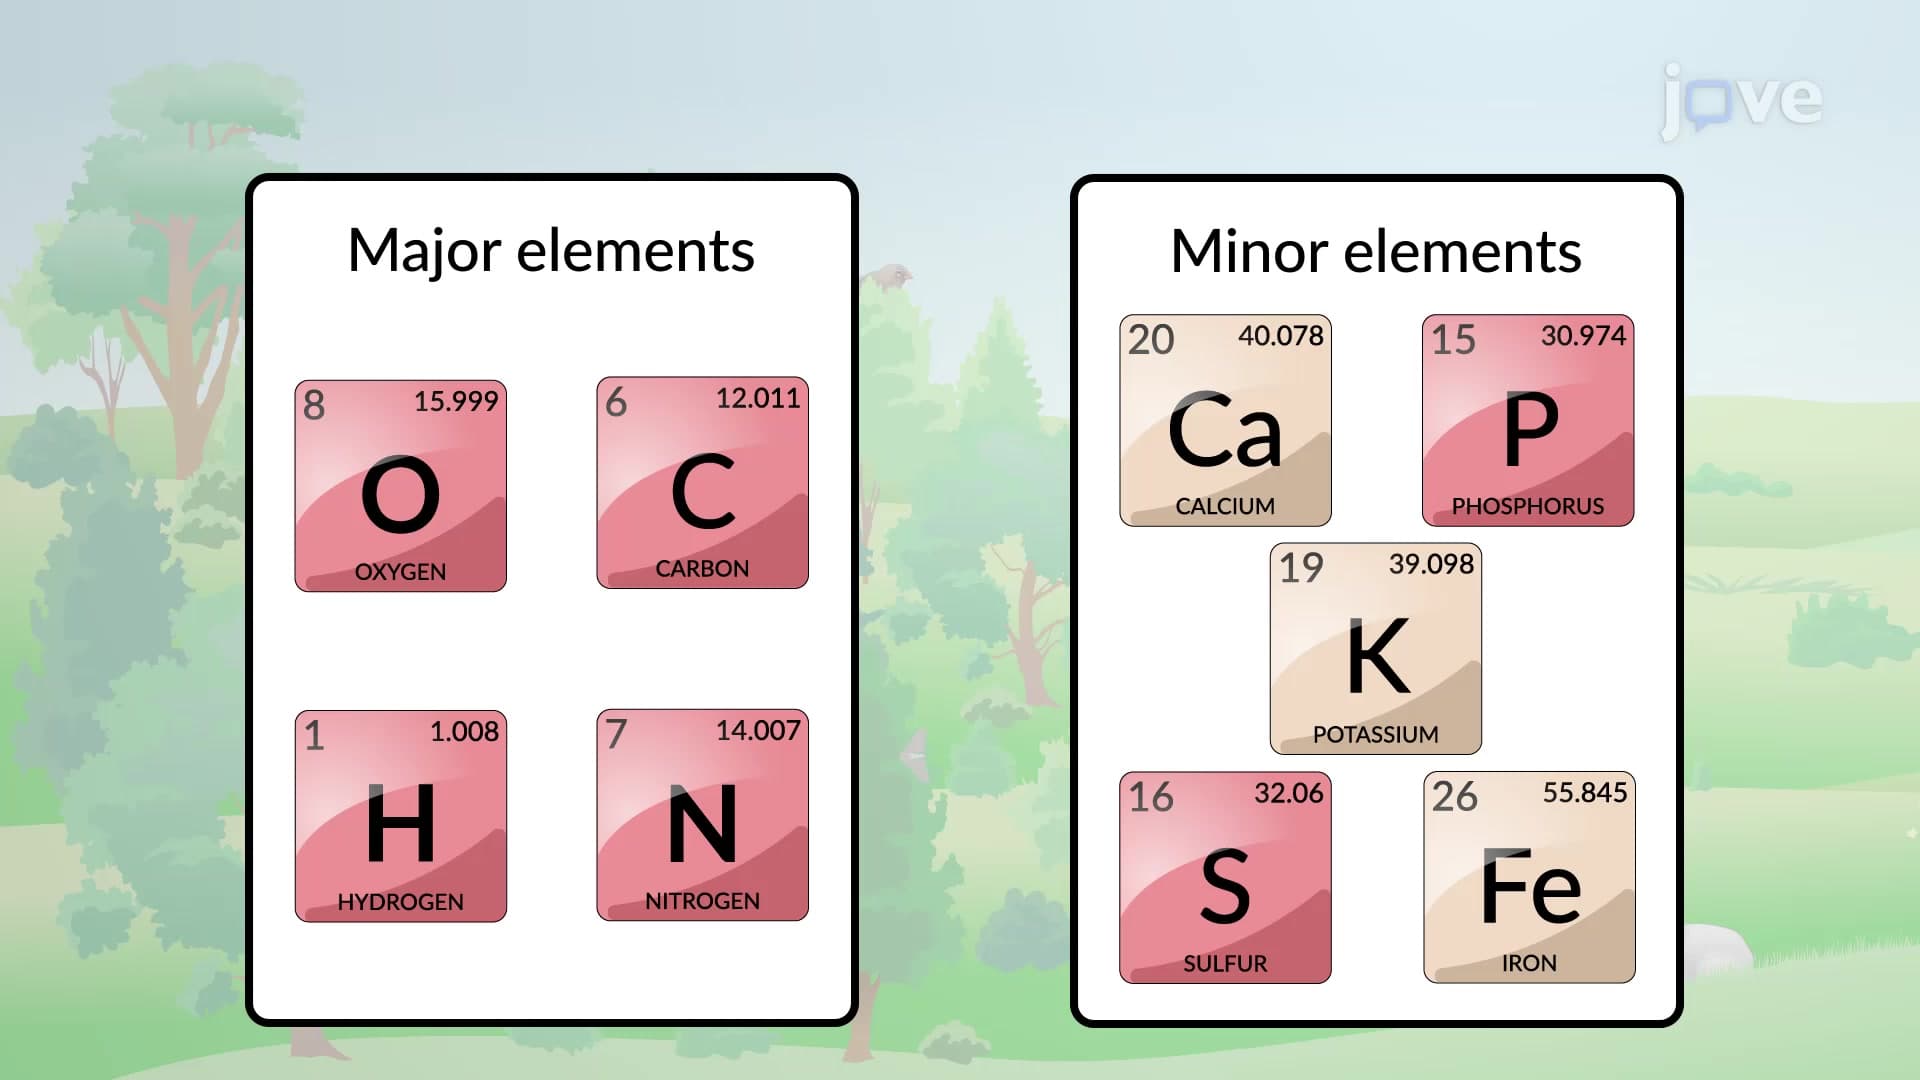
The Periodic Table and Organismal Elements
 01:27
The Periodic Table and Organismal Elements
Periodic Table Provides Information...
 01:24
Drug Toxicity: Dose-Dependent Reactions
 01:25
Bioactivation and Tissue Toxicity
 01:36
Types of Toxins
Air pollutants, primarily gases, pose significant threats to respiratory health, leading to conditions like hypoxia, lung cancer, and in extreme cases, death.
Environmental pollutants like...