Related Experiment Video
Updated: Apr 25, 2026


Author Spotlight: Translational Applications of Stimulated SFEMG in Rodent Models
Published on: March 8, 2024
[Effects of pri ming different low-dose rocurium on pharmacodynamics of mivacurium]
Yan Xin1, Ying Guo1, Yuge Jiang1
1Anesthesia and Operation Center, Chinese People's Liberation Army General Hospital, Beijing 100853, China.

Objective:
To explore the effects of pri ming rocuronium on neuromuscular blockade produced by mivacurium.
Methods:
Ethical approval was granted by the medical ethics committee of our hospital with a reference number of C-2013-018-01. A total of 120 ASA physical status I and II patients undergoing selective otorhinolaryngologic surgery under general anesthesia signed the form of informed consent. And they were randomly divided by a random number table into 4 groups. After a standardized imidazole-propofol-fentanyl induction, they received a saline placebo injection (GroupI) and a pri ming dose of rocuronium 0.06 mg/kg (GroupII) , rocuronium 0.075 mg/kg (Group III) and rocuronium 0.1 mg/kg (Group IV). An intubating dose of mivacurium 0.15 mg/kg was offered 3 minutes later. Anesthesia was maintained with propofol and remifentanyl continuous infusion. Neuromuscular block was monitored with train of four (TOF) stimulation. The onset time, reappearance of T1 (DUR TOFc 1), times of T1 25% and 75% recovery, recovery index and times of TOF25%, 75% and 90% recovery were recorded.
Results:
The onset time of mivacurium was significantly shorter and the times of T1 25% and 75% recovery were significantly longer in groups of II, III and IV than those in groupI. No significant difference existed in recovery index among 4 groups. The onset time of mivacurium became progressively shorter with the growing pri ming dose of rocurium among three experiment groups. And it was not statistically significant.
Conclusions:
Pri ming rocuronium decreases the onset and intubating times of mivacurium without effect on recovery index. No significant difference exists in drug effect among 3 experiment groups.
Insights
Priming with rocuronium speeds up the onset of neuromuscular blockade from mivacurium. This effect shortens intubation times but does not alter the recovery index, offering a potential anesthetic optimization.
Area of Science:
- Anesthesiology
- Pharmacology
- Neuromuscular blockade
Background:
- Neuromuscular blocking agents are crucial in general anesthesia.
- Optimizing the onset and recovery profiles of these agents is clinically significant.
- Rocuronium and mivacurium are commonly used neuromuscular blockers.
Purpose of the Study:
- To investigate the impact of priming doses of rocuronium on the neuromuscular blockade induced by mivacurium.
- To evaluate changes in onset time and recovery characteristics.
Main Methods:
- A randomized study involving 120 patients undergoing surgery.
- Patients received varying priming doses of rocuronium or a placebo before mivacurium administration.
- Neuromuscular blockade was monitored using train-of-four (TOF) stimulation.
Main Results:
- Priming with rocuronium significantly shortened the onset time of mivacurium.
- Recovery times (T1 25% and 75%) were prolonged in groups receiving rocuronium priming.
- No significant differences were observed in the recovery index across the groups.
Conclusions:
- Priming rocuronium effectively reduces the onset and intubating times of mivacurium.
- The recovery index of neuromuscular blockade remains unaffected by rocuronium priming.
- The observed effects were consistent across different priming doses of rocuronium.
More Related Videos
 07:02
A Computerized Test Battery to Study Pharmacodynamic Effects on the Central Nervous System of Cholinergic Drugs in Early Phase Drug Development
Published on: February 11, 2019
 08:49
Assessing Changes in Volatile General Anesthetic Sensitivity of Mice after Local or Systemic Pharmacological Intervention
Published on: October 16, 2013
Related Concept Videos
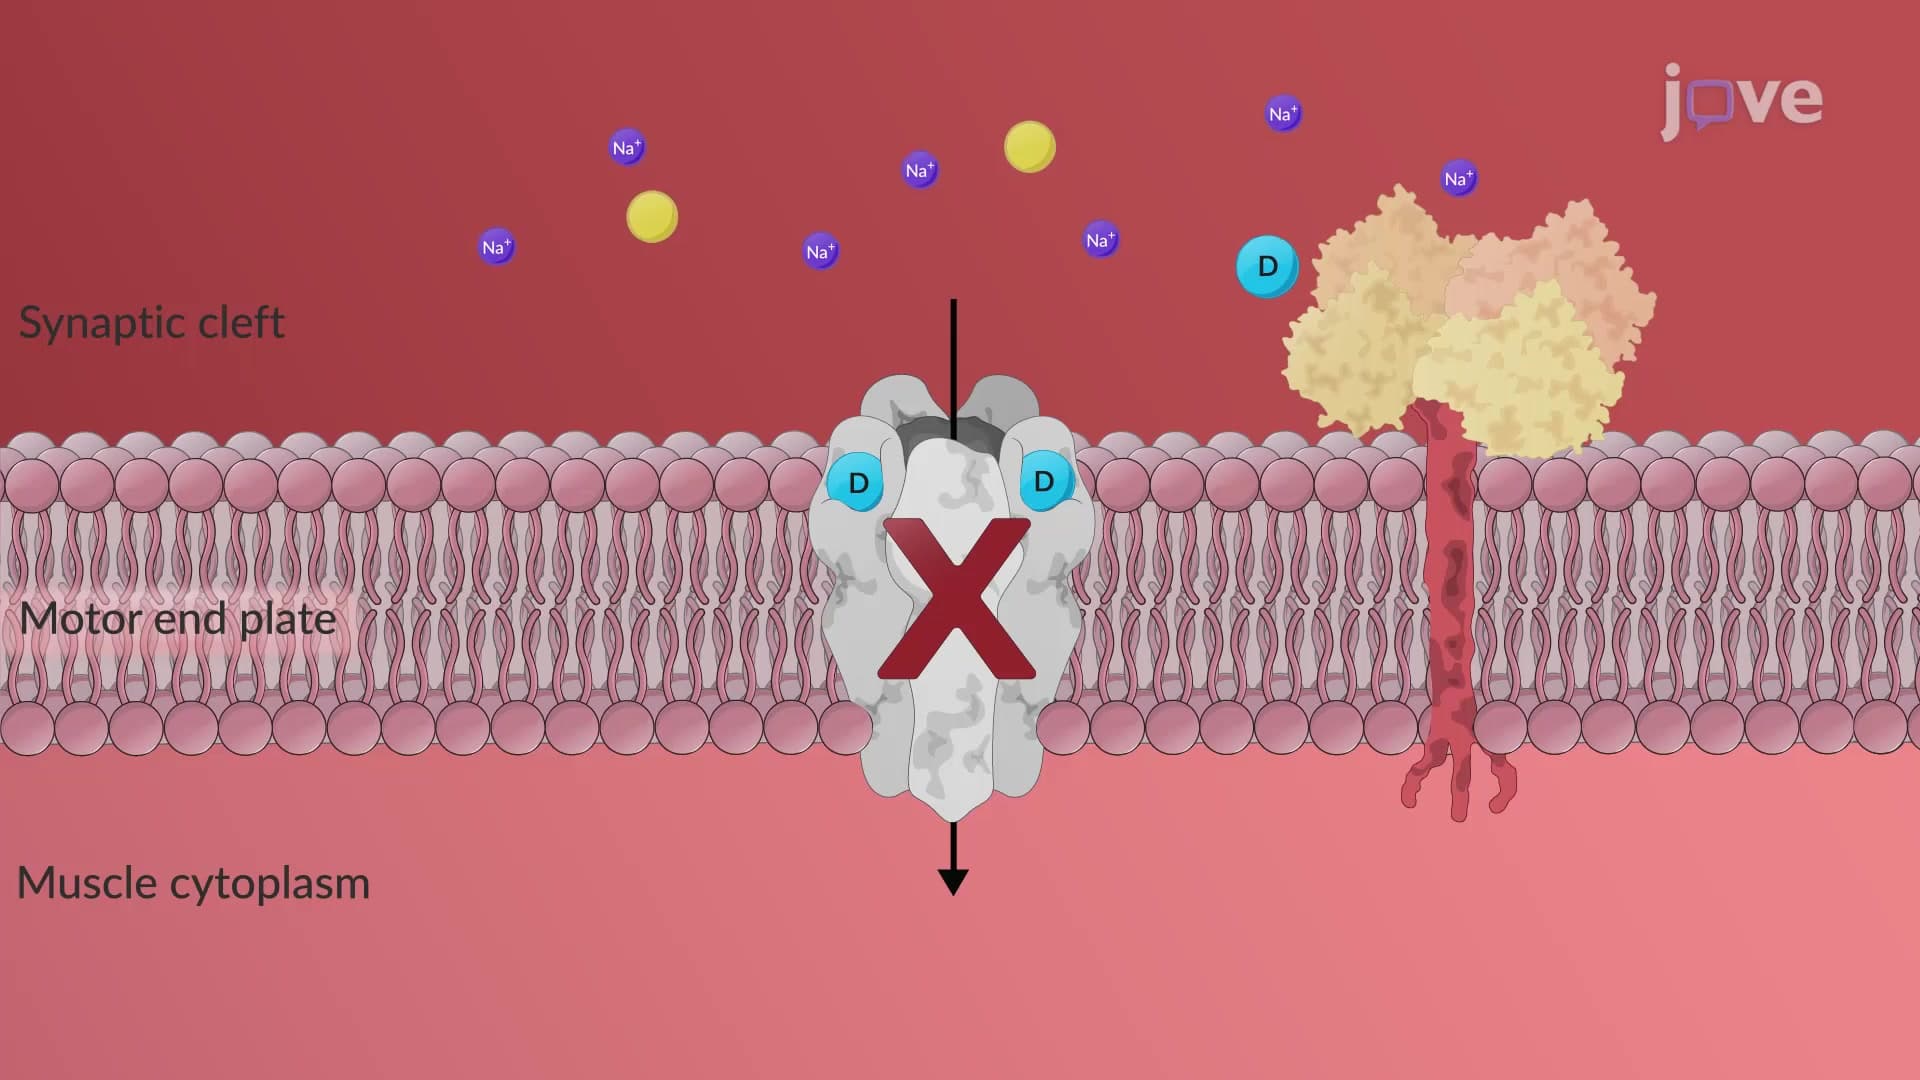 01:17
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:28
Depolarizing Blockers: Mechanism of Action
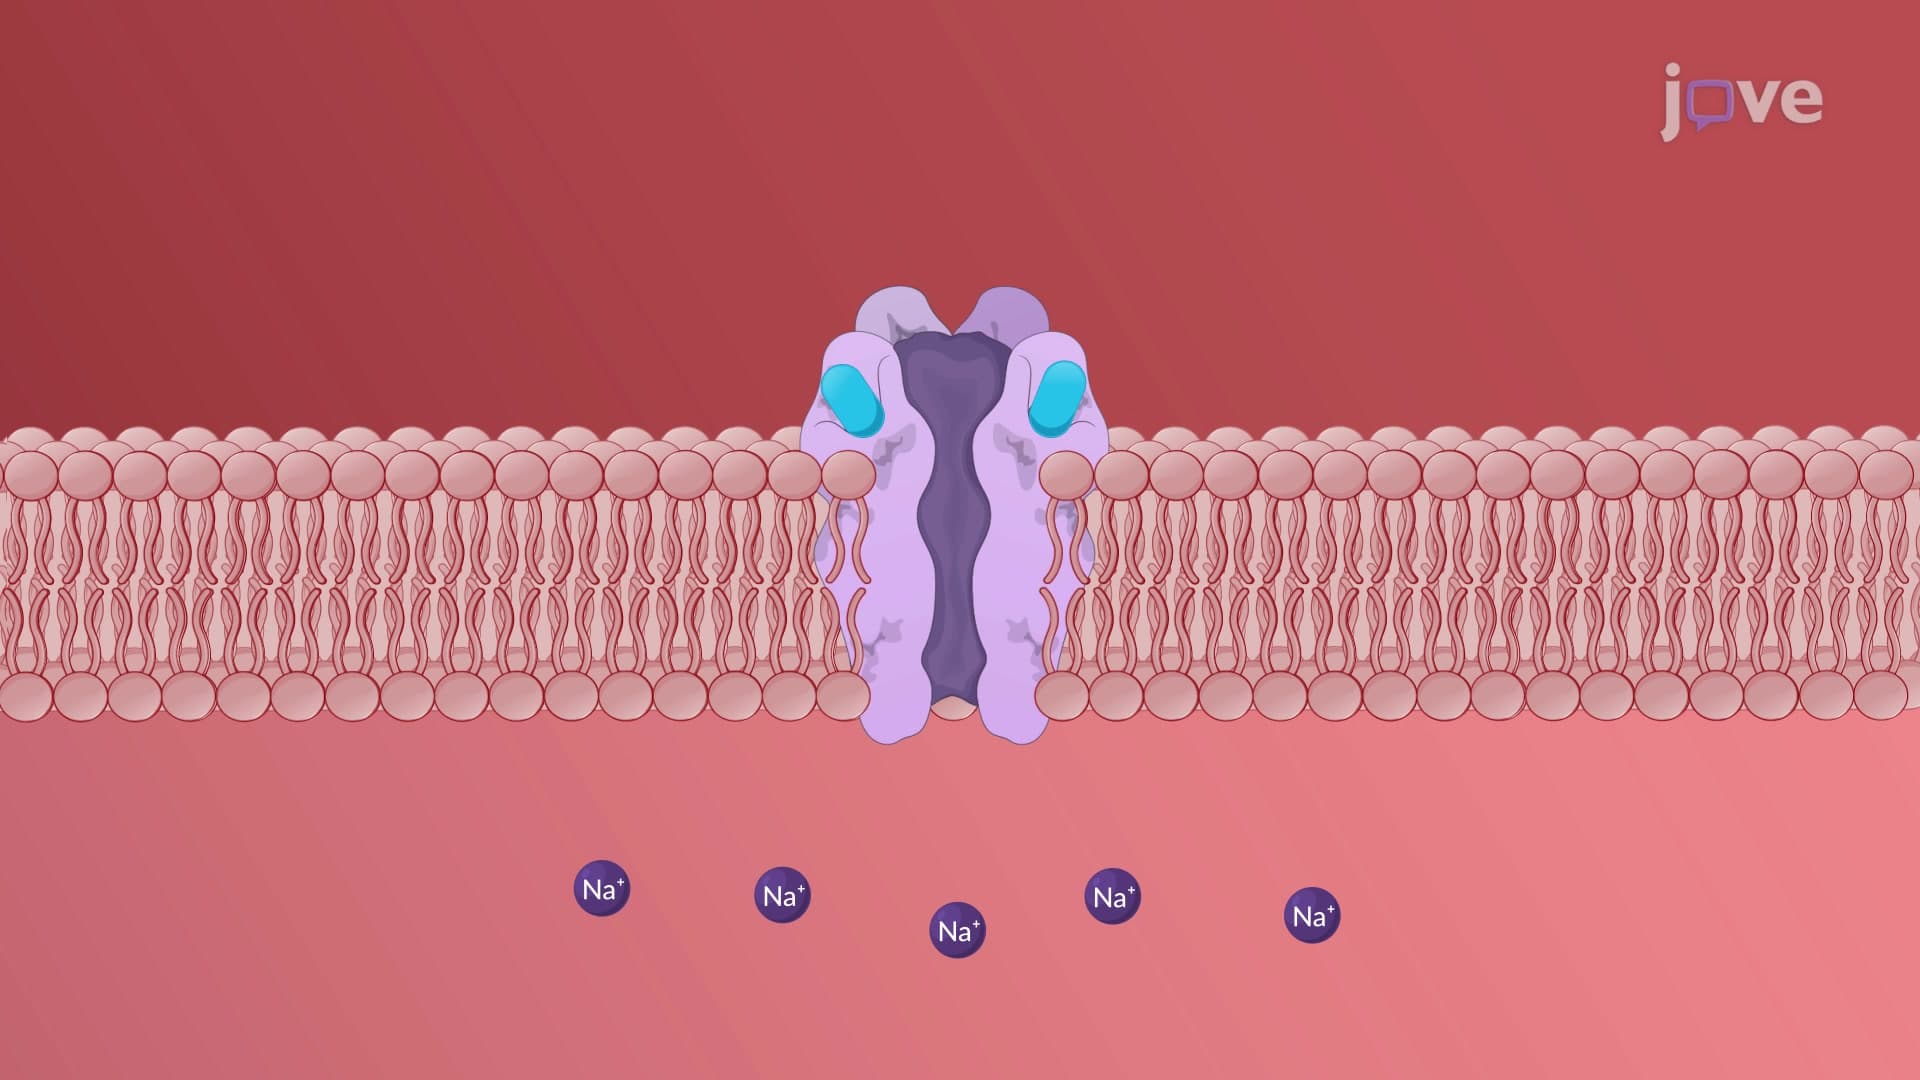
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...