Related Experiment Video
Updated: Apr 25, 2026
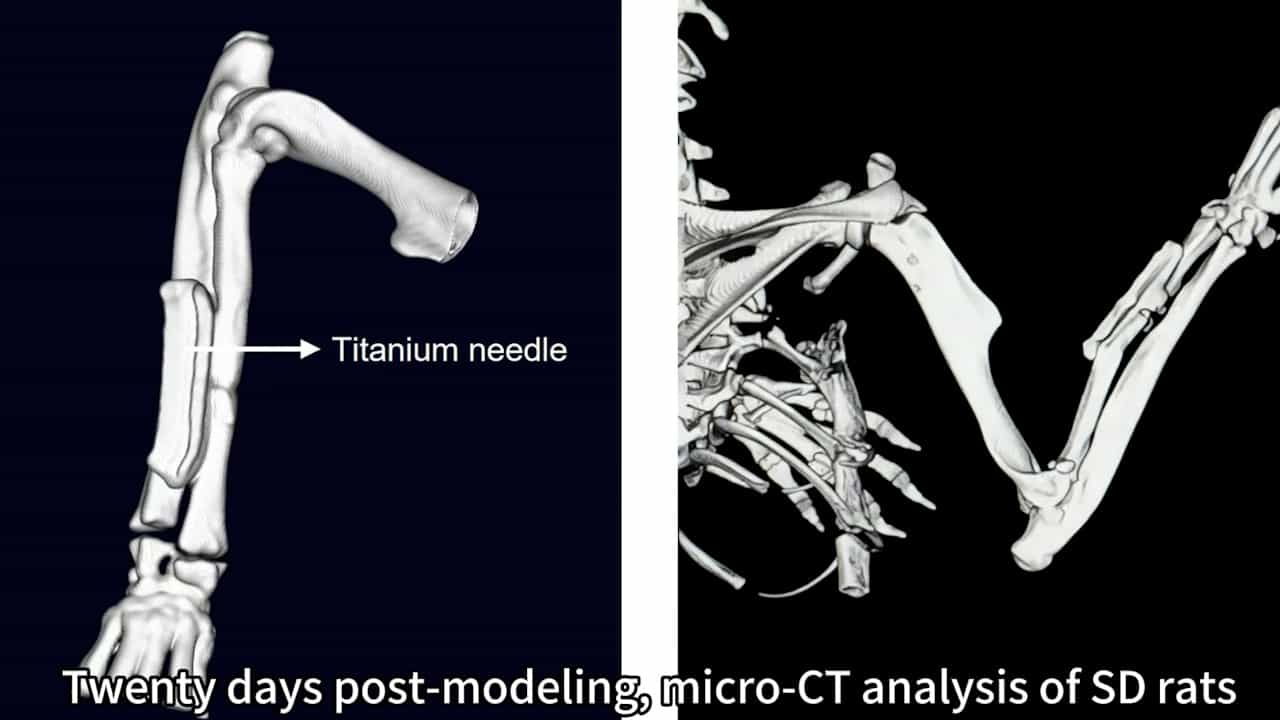

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Evidence-based protocol for prophylactic antibiotics in open fractures: improved antibiotic stewardship with no
Lauren Rodriguez1, Hee Soo Jung, James A Goulet
1From the Departments of Emergency Medicine (L.R.), and Orthopaedic Surgery (J.A.G.), University of Michigan Medical School; University of Michigan (A.C.); and Trauma and Surgical Critical Care (L.M.N.), and Department of Surgery (L.M.N.), University of Michigan Health System (D.A.M.-A.), University Hospital, Ann Arbor, Michigan; Section of Trauma and Acute Care Surgery (H.S.J.), Division of General Surgery, Department of Surgery, University of Wisconsin, Madison, Wisconsin.

Background:
Evidence-based guidelines for prophylactic antibiotic use in open fractures recommend short-course, narrow-spectrum antibiotics for Gustilo Grade I or II open fractures and broader gram-negative coverage for Grade III open fractures. No studies to date have assessed the impact of these guidelines on infection rates in open fractures. Infection rates before and after the new protocol implementation were examined.
Methods:
A new protocol was implemented including antibiotic prophylaxis based on grade of open fracture: Grade I/II fractures, cefazolin (clindamycin if allergy); Grade III fractures, ceftriaxone (clindamycin and aztreonam if allergy) for 48 hours. Aminoglycosides, vancomycin, and penicillin were removed from the protocol. Data for 174 femur and tibia/fibula open fractures (101 preprotocol and 73 postprotocol) were analyzed. Patients who were moribund or managed at another institution for greater than 24 hours were excluded. The National Healthcare Safety Network risk index was used to provide risk adjustment.
Results:
No significant differences in the study cohorts (preprotocol and postprotocol) were identified for demographics (age, 37.2 [14.8] years vs. 40.0 [17.9] years; male, 71.3% vs. 79.5%) or mechanism of injury (motor vehicle crash, 67.3% vs. 64.4%; other blunt, 28.7% vs. 32.9%; penetrating, 4.0% vs. 2.8%). After protocol implementation, the use of aminoglycoside and glycopeptide antibiotics was significantly reduced (53.5% vs. 16.4%, p = 0.0001). The skin and soft tissue infection rate per fracture event was 20.8% before and 24.7% after protocol implementation (p = 0.58). There was no statistically significant change after stratification for fracture grade, National Healthcare Safety Network risk index, or fracture site. The rate per fracture event of resistant gram-positive and gram-negative organisms (15.8% vs. 17.8%, p = 0.84) and methicillin-resistant Staphylococcus aureus (2.0% vs. 4.1%, p = 0.65) was not different.
Conclusion:
Implementation of an evidence-based protocol for open fracture antibiotic prophylaxis resulted in significantly decreased use of aminoglycoside and glycopeptide antibiotics with no increase in skin and soft tissue infection rates.
Level Of Evidence:
Therapeutic study, level IV.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:28
Inhibitors of Bacterial DNA Synthesis
 01:30
Urinary Tract Infection III: Diagnostic Studies and Interprofessional Care
 01:26
Tonsillitis II: Management
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...