

Early effect of NTBC on renal tubular dysfunction in hereditary tyrosinemia type 1
A Maiorana1, M Malamisura1, F Emma2
1Department of Pediatric Medicine, Division of Metabolism and Research Unit of Metabolic Biochemistry.

Background:
Hereditary tyrosinemia type 1 (HT1) is characterized by severe progressive liver disease and renal tubular dysfunction. NTBC therapy has revolutionized the management of HT1 but its effect on renal tubular function has so far been poorly investigated. The aim of this study was to describe the early effect of NTBC on renal tubular disease in patients with HT1.
Methods:
Five HT1 patients (age between 5 and 53 months) with different types of presentation were evaluated before and during the first 2 weeks of therapy with NTBC in a retrospective case analysis for phosphate metabolism and renal tubular function.
Results:
Before starting NTBC therapy, all children manifested signs of renal dysfunction which included hypophosphatemia, acidosis, reduced phosphate reabsorption, aminoaciduria, glycosuria (Fanconi syndrome), and variable degree of proteinuria. Some patients also presented increased urinary calcium/creatinine ratio and raised fractional excretion of sodium. Starting of NTBC therapy resulted in the rapid normalization of plasma phosphate within one week from its initiation in majority of patients and in all patients during the second week of therapy. TmP/GFR normalized in 48h, while the other markers of renal dysfunction showed an improving trend over 2 weeks.
Conclusions:
NTBC is an efficient treatment for renal tubular dysfunction in HT1, allowing the return to normal function within a few weeks. Its early effect on renal tubular cells appeared to be very rapid, particularly in normalizing plasma phosphate and TmP/GFR. In our series of patients, the TmP/GFR resulted as the most reliable index of tubular function.
More Related Videos
 09:40
Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
 06:32
Development of Human Renal Tubular Epithelial Cell Primary Cultures in Monolayers and Three-Dimensional Conditions
Published on: June 13, 2025
Related Concept Videos
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase
 01:20
Inborn Errors of Metabolism
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:28
Renal Drug Excretion: Tubular Secretion
 01:29
Acute Kidney Injury II: Pathophysiology
 01:29
Renal Regulation of Acid-Base Balance
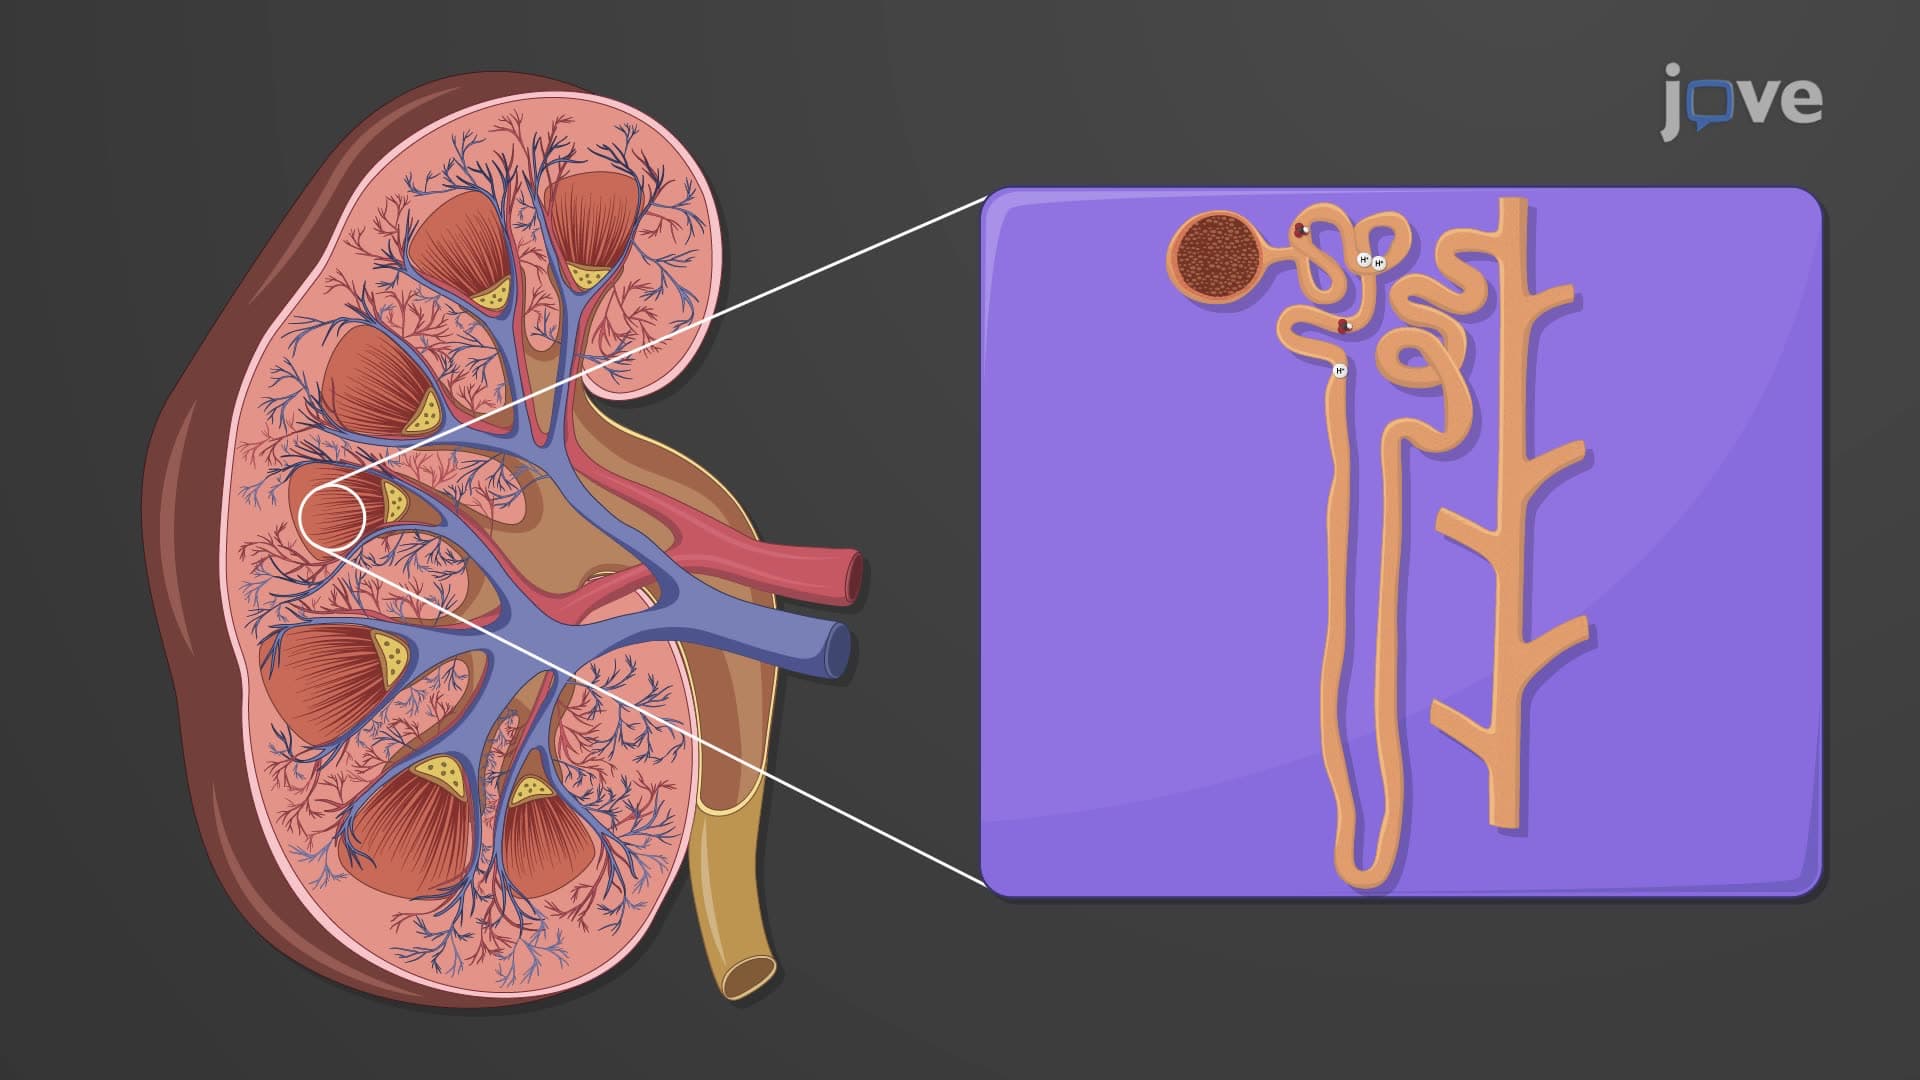
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...