Applicability of published guidelines for assessment of left ventricular diastolic function in adults to children with restrictive cardiomyopathy: an observational study
Related Experiment Video
Updated: Apr 24, 2026
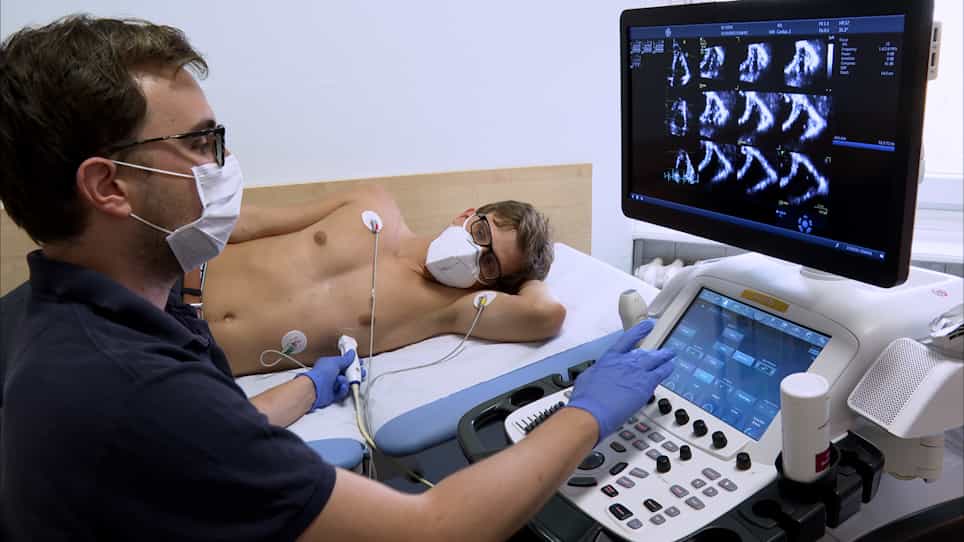
Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Nao Sasaki1, Mario Garcia, H Helen Ko
1Division of Pediatric Cardiology, Department of Pediatrics, Mount Sinai Medical Center, New York, NY, USA, naokimotosasaki@gmail.com.

Insights
Pediatric diastolic dysfunction (DD) lacks established diagnostic guidelines. Adult parameters are unreliable for children with restrictive cardiomyopathy (RCM), highlighting the need for new pediatric-specific DD criteria.
Area of Science:
- Pediatric Cardiology
- Cardiovascular Physiology
- Echocardiography
Background:
- Established guidelines for diagnosing and grading diastolic dysfunction (DD) in pediatric patients are lacking.
- Recent studies question the applicability of adult DD parameters to children.
- Restrictive cardiomyopathy (RCM) is a pediatric condition characterized by isolated, irreversible DD.
Purpose of the Study:
- To evaluate the effectiveness of current adult diastolic indices in diagnosing DD in pediatric RCM patients.
- To determine if established adult echocardiographic parameters reliably indicate DD in children with RCM.
- To identify specific echocardiographic abnormalities indicative of restrictive physiology in pediatric RCM.
Main Methods:
- Retrospective review of a clinical database (2002-2010) for pediatric RCM patients.
- Comprehensive echocardiographic assessment of diastolic function using mitral valve inflow Doppler and tissue Doppler imaging.
- Comparison of diastolic parameters (MV inflow E, A, DT, Vp, E', A', L' wave, LA area/BSA) between RCM patients and age/gender-matched controls.
Main Results:
- RCM patients exhibited significantly larger left atrial area indexed to body surface area (LA area/BSA) compared to controls.
- Mitral valve inflow E and A velocities were lower, and deceleration time (DT) was shorter in the RCM group.
- Higher septal E/E' ratio, absent A waves, and presence of L' waves were noted abnormalities in RCM patients, with poor sensitivity of individual cut-offs for restrictive physiology.
Conclusions:
- Poor left ventricular (LV) compliance is a key feature of pediatric RCM, even with normal early relaxation and filling.
- Current adult echocardiographic indices for diastolic function have limited sensitivity in diagnosing pediatric RCM.
- Development of specific guidelines and physiologic grading for pediatric diastolic dysfunction is necessary.
Abstract:
Guidelines for diagnosis and grading of diastolic dysfunction (DD) in children have not been established. The applicability of adult parameters of DD to children has been questioned by recent studies. Although normal diastolic parameters in children have been published, the data to support application of these indices for the non-invasive diagnosis of DD and quantifying its degree are still being developed. Restrictive cardiomyopathy (RCM) is the only recognized disease entity in children that presents with isolated, irreversible DD as the predominant finding. The aim of this study was to investigate the applicability of current diastolic indices used for assessment of diastolic function in adults as reliable indicators of DD in children with established RCM. Retrospective review of institutional clinical database for the period of 2002-2010 was performed to identify patients with RCM who had had a comprehensive echocardiographic assessment of diastolic function. The following parameters were obtained from apical four chamber view: mitral valve (MV) inflow Doppler early filling velocity (E), late filling velocity (A), deceleration time (DT), color M-mode flow propagation from MV to apex (Vp), Doppler tissue imaging derived early diastolic velocity E' and late diastolic velocity A' at the LV lateral wall at MV annulus, RV at the tricuspid valve annulus, septum, and LA area. All parameters were compared to age and gender matched controls using student t test. : LA area/BSA was significantly larger in RCM group than the control group, median 22.8 cm(2)/m(2) (range 16.9-28.6) versus 10.3 cm(2)/m(2) (range 8.3-12.3), p value <0.001. MV inflow E and A were lower, and DT was shorter in the RCM group (p = 0.04, 0.02, and 0.005, respectively). A wave was absent in 3 of 9 patients in the RCM group. Ratio of E to A (E/A) was not different between the two groups. E' was significantly lower at all three sites in RCM group; however, there was some overlap between the two groups. E/septal E' ratio was statistically significantly higher in RCM group. A' was absent either at lateral wall or at septum in five patients. 7 of 9 patients in RCM group had L' wave (at lateral wall or septum) defined as negative deflection during diastasis. Vp was higher in RCM group than in the control group 81.4 ± 44.5 versus 52.9 ± 10.9, p value <0.01. Combination of increased left atrial size, septal E/E', and lack of A wave and presence of mid-diastolic L'-wave are the noted abnormalities in this group. Individual cut-offs for Doppler indices have very poor sensitivity in identifying restrictive physiology. These findings suggest that poor LV compliance is the hallmark of restrictive cardiomyopathy in children even in the presence of normal early relaxation and ventricular filling. These findings support the need for development of guidelines for diagnosis and physiologic grading of diastolic dysfunction in children.

Related Concept Videos
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests