Related Experiment Video
Updated: Apr 23, 2026


Injectable Supramolecular Polymer-Nanoparticle Hydrogels for Cell and Drug Delivery Applications
Published on: February 7, 2021
Intestinal uptake of insulin nanoparticles: facts or myths?
Marlene A Lopes, Bárbara A Abrahim, Raquel Seiça
1Centre for Pharmaceutical Studies, Faculty of Pharmacy, University of Coimbra, Azinhaga de Santa Comba, 3000-548 Coimbra, Portugal. aribeiro@ff.uc.pt.

Abstract:
The oral route is the most suitable and physiological delivery route. Oral insulin delivery would minimize the health hazard implied in repeated injection, surpass complications arising from the need for sterile techniques associated with parenteral formulations and provide better glucose homeostasis. However, it is limited by various physiological barriers and still remains a scientific challenge. The desire to deliver insulin by the oral route in a conveniently and effectively way has led to the intense investigation of new delivery systems. Nanodelivery systems have been proposed to enhance the bioavailability of insulin after oral administration. This review article describes the gastrointestinal barriers to oral insulin delivery, including chemical, enzymatic and absorption barriers. The potential transport mechanisms of insulin delivered by nanoparticles across the intestinal epithelium are also addressed. Finally, how nanoparticles characteristics affect insulin pharmacological activity and bioavailability is discussed.
More Related Videos
 09:36
Polyethyleneimine-coated Iron Oxide Nanoparticles as a Vehicle for the Delivery of Small Interfering RNA to Macrophages In Vitro and In Vivo
Published on: February 5, 2019
 09:02
Author Spotlight: Innovative Cancer Therapies with Iron Oxide Nanoparticles for Glioblastoma Treatment
Published on: September 27, 2024
Related Concept Videos
 01:27
Insulin Formulations: Types and Delivery
Short-acting insulins are divided into...
 01:30
Production of Pharmaceuticals
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...
 01:05
Insulin Secretory Vesicles
 01:06
Oral Hypoglycemic Agents: Glinides
 01:30
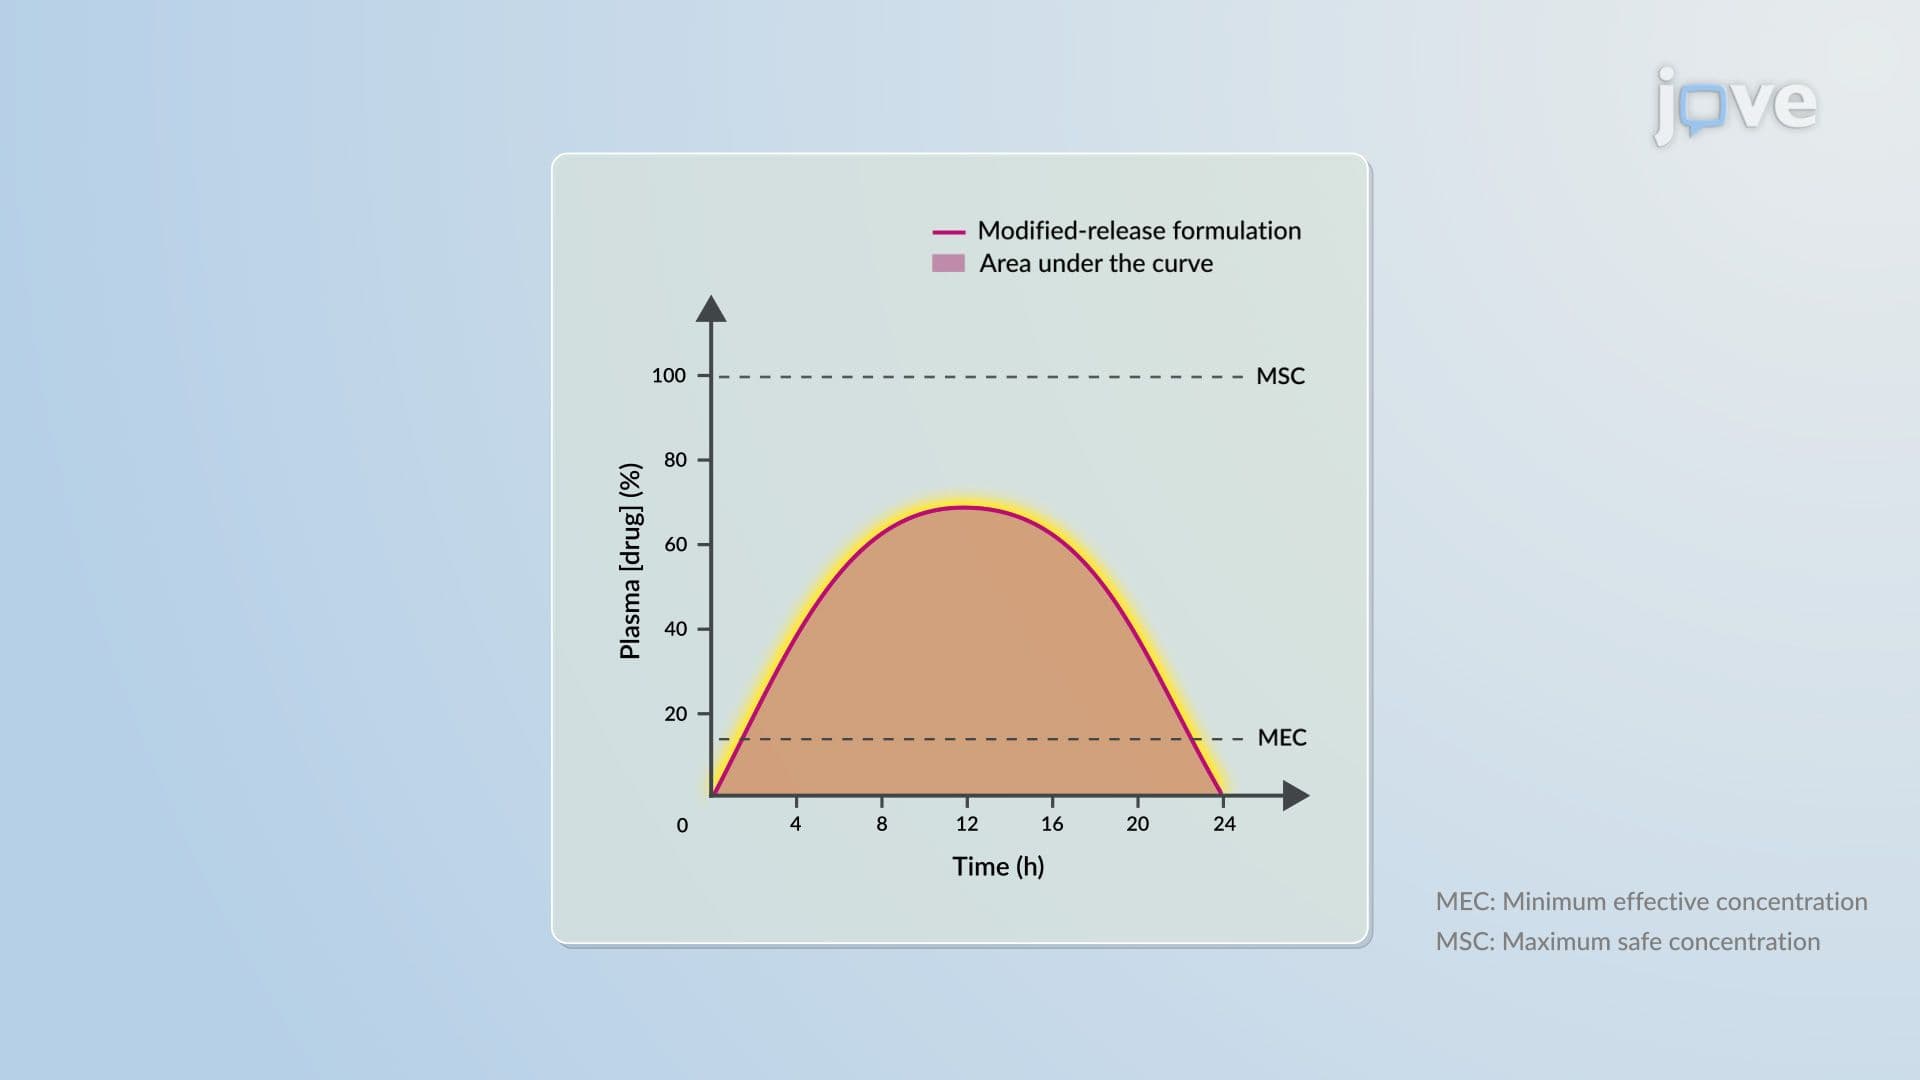
Modified-Release Drug Delivery Systems: Bioavailability