Related Experiment Video
Updated: Apr 23, 2026
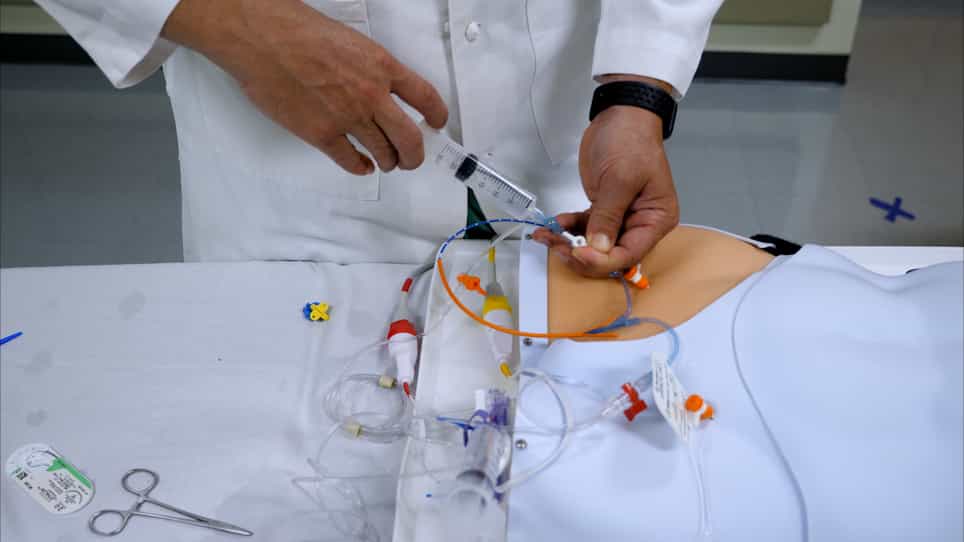

Complete and Partial Resuscitative Endovascular Balloon Occlusion of the Aorta for Hemorrhagic Shock
Published on: May 19, 2022
[Clinical observation of damage control resuscitation in rescue multiple fracture with hemorrhagic shock]

Objective:
To investigate clinical effects of damage contral resuscitation (DCR) in rescue multiple fracture with hemorrhagic shock.
Methods:
From January 2009 to May 2013, clinical data of 24 patients suffered from multiple fracture with hemorrhagic shock were retrospectively reviewed. Among them, 18 cases were male and 6 cases were female, aged from 21 to 48 years old with an average of (32.5 +/- 4.5). Small capacity of balanced salt solution were used to maintain systolic, pressure (80-90) mmHg before operation. After control of bleeding with operation, sufficient amount of liquid were rapidly use, and plasma were supplied according to proportion of plasma and red cell suspension (1 U:2 U-1 U:1 U). After remedy of shock, fluid infusion were sustained negative balance slightly and keep acid-base equilibrium of electrolyte. Dosage of balanced salt solution and blood transfusion before remedy shock were recorded, removal time of lactic acid, coagulation function, incidence and case fatality of DIC were observed.
Results:
Four patients were died after 6-18 h into hospital (2 cases died for acute respiratory distress syndrome and 2 cases for irreversible shock). Twenty patients with shock were corrected at 2-6 h after injury. Dosage of balanced salt solution was(4,259 +/- 268) ml,red cell suspension was (14 +/- 2) U, fresh frozen plasma was (800-1,600) ml (FFP: 1 U = 100 ml) averaged (900 + 300) ml, blood platelet was 4-6 U. Coagulation function and electrolyte were normal. Lactic acid was less than 2 mmol/L within 24 h,the success rate of recovery was 83.3% (20/24).
Conclusion:
Performing DCR can obvious improve success rate of remedy serious fracture combined with uncontrolled hemorrhagic shock. Supplementing FFP when correcting coagulation function should be carry out promptly in fluid resuscitation.

Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:24
Blood Pressure Imbalances and Circulatory Shock
Blood Pressure: Hypertension and Hypotension
Normal blood pressure is 120/80 mm Hg. Elevated blood pressure is 120-129/under 80 mm Hg. Hypertension, warranting treatment at 130/80 mm Hg, is often asymptomatic and can lead to severe cardiovascular events, aneurysms, peripheral arterial disease, chronic renal disease, or cardiac...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:30
Venous Thrombosis IV: Nursing Management
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:29
Hemorrhagic Stroke ll: Pathophysiology