Related Experiment Video
Updated: Apr 23, 2026
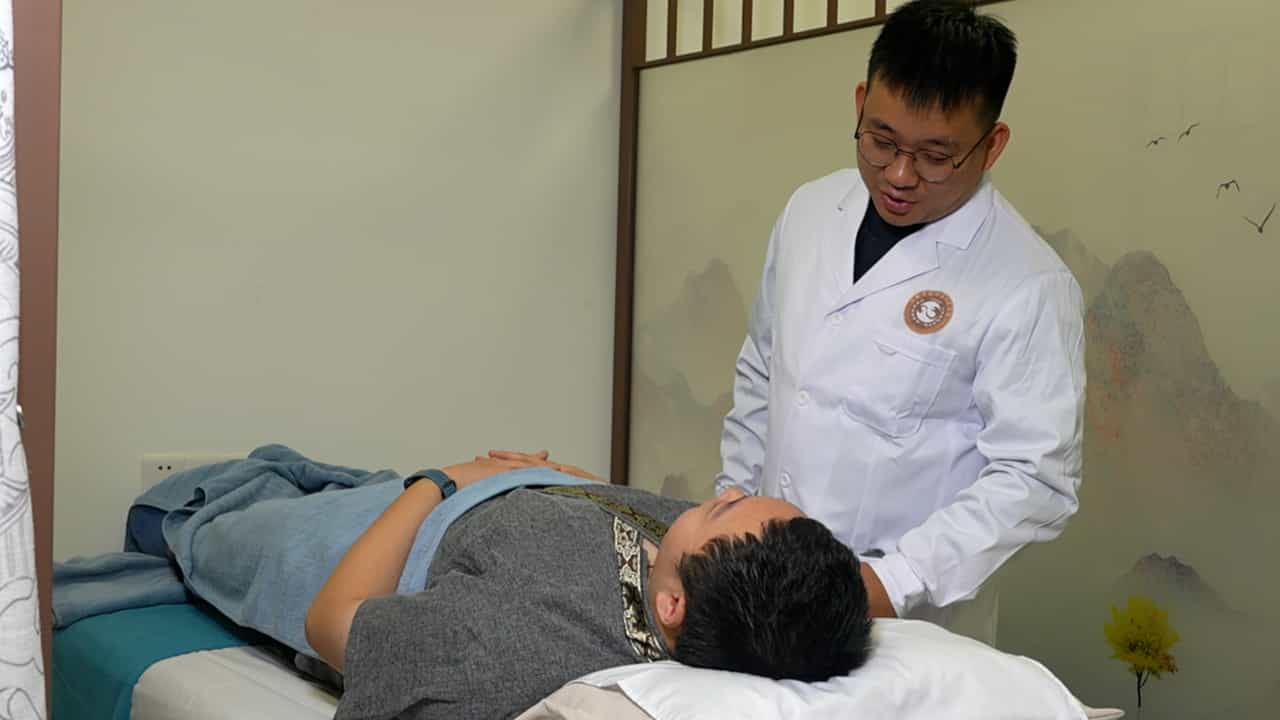

Author Spotlight: Evaluating the Therapeutic Efficacy of Moving Cupping Along Meridians for Acute Exacerbation of COPD
Published on: September 27, 2024
Fluticasone propionate/salmeterol 250/50 μg versus salmeterol 50 μg after chronic obstructive pulmonary disease
Jill A Ohar1, Glenn D Crater, Amanda Emmett
1Wake Forest University Medical Center, 1 Medical Center Boulevard, Winston-Salem, NC, USA. johar@wakehealth.edu.

Background:
Inhaled long-acting beta2 agonists used alone and in combination with an inhaled corticosteroid reduce the risk of exacerbations in patients with stable COPD. However, the relative efficacy of these agents in preventing recurrent exacerbations in those recovering from an initial episode is not known. This study compared the rate of COPD exacerbations over the 26 weeks after an initial exacerbation in patients receiving the combination of fluticasone propionate and salmeterol (FP/SAL) or SAL alone.
Methods:
Patients (n = 639) aged ≥40 years were randomized to either twice-daily inhaled FP/SAL 250/50 μg or SAL 50 μg. Primary, and secondary, endpoints were rates of recurrent severe, and moderate/severe, exacerbations of COPD. Lung function, health outcomes and levels of biomarkers of systemic inflammation were also assessed.
Results:
There was no statistically significant treatment difference in rates of recurrent severe exacerbations (treatment ratio 0.92 [95% CI: 0.58, 1.45]) and moderate/severe exacerbations (0.82 [0.64, 1.06]) between FP/SAL and SAL in the intent-to-treat population. Pre-dose morning FEV1 change from baseline was greater (0.10 L [0.04, 0.16]) with FP/SAL than SAL. No treatment difference was seen for other endpoints including patient-reported health outcomes and biomarker levels for the full cohort.
Conclusions:
No significant treatment difference between FP/SAL and SAL was seen in COPD exacerbation recurrence for the complete cohort. Treatment benefit with FP/SAL over SAL (treatment ratio 0.68 [0.47, 0.97]) was seen in patients having FEV1 ≥ 30% and prior exposure to ICS. No unexpected safety issues were identified with either treatment. Patients with the most severe COPD may be more refractory to treatment.
Trial Registration:
ClinicalTrials.gov (identifier NCT01110200). This study was funded by GlaxoSmithKline (study number ADC113874).

Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:25
Antiasthma Drugs: Inhaled Corticosteroids and Glucocorticoids
ICS work through a multifaceted mechanism of action. They suppress the inflammatory response caused by the proliferation of TH cells. They also reduce the transcription of the IL-2 gene, which is involved in the...
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:23
Inhaled Medications
 01:25
Antiasthma Drugs: β2-Adrenoceptor Agonists
One class of bronchodilators includes β2-adrenoceptor agonists. These agents target the β2-adrenoceptors located on bronchial smooth muscle cells. By stimulating these receptors, β2-agonists induce...
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.