Related Experiment Video
Updated: Apr 23, 2026
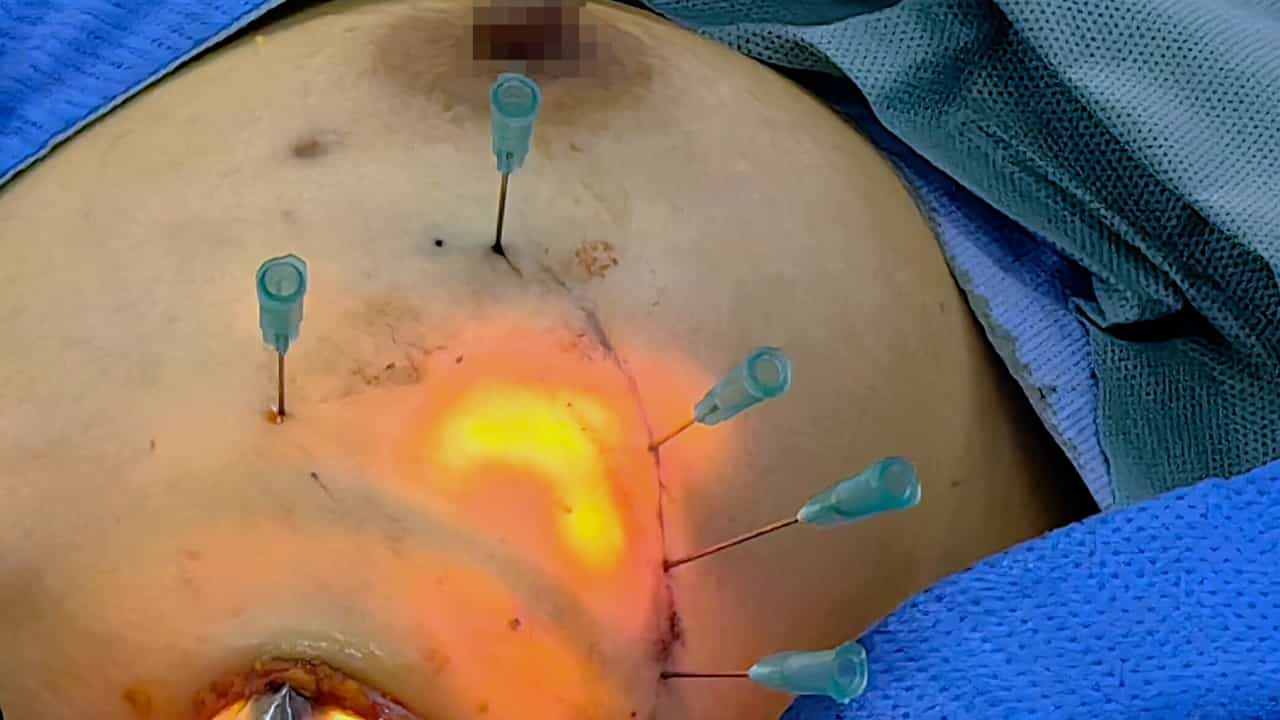
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Impact of neoadjuvant chemotherapy on axillary nodal involvement in patients with clinically node negative triple
Carol S Connor1, Bruce F Kimler, Joshua M V Mammen
1Department of Surgery, University of Kansas Medical Center, Kansas City, Kansas.

Background:
We evaluated the impact of Neoadjuvant Chemotherapy (NAC) versus primary surgery (PS) on axillary disease burden/surgery in clinically node negative Triple Negative Breast Cancer (TNBC).
Methods:
Two hundred forty-three Stage I-III TNBC patients have enrolled on an IRB approved multisite prospective registry. Clinical and treatment information was collected.
Results:
One hundred fifty-five patients with clinically node negative TNBC were identified. 47%, 49%, and 4% of patients had T1, T2, and T3 disease, respectively. Patients underwent PS (103/155, 66%) or NAC (52/155, 34%) at the discretion of treating physicians. 17% of PS and 0% of NAC patients were node positive at surgery (P=0.006). For T2 disease, 32% of PS and 0% of NAC patients were node positive at surgery (P=0.001). NAC patients had a lower chance of positive SLNB (0% vs. 12%, P=0.004) and undergoing ALND (2% vs. 22%, P=0.001) than PS patients.
Conclusion:
In this clinically node negative TNBC cohort, all NAC-treated patients were node negative at surgery, whereas 17% of PS patients had involved axillary nodes. NAC should be considered for clinically node negative TNBC to reduce the extent of axillary surgery even if breast conservation is not planned.