Related Experiment Video
Updated: Apr 20, 2026
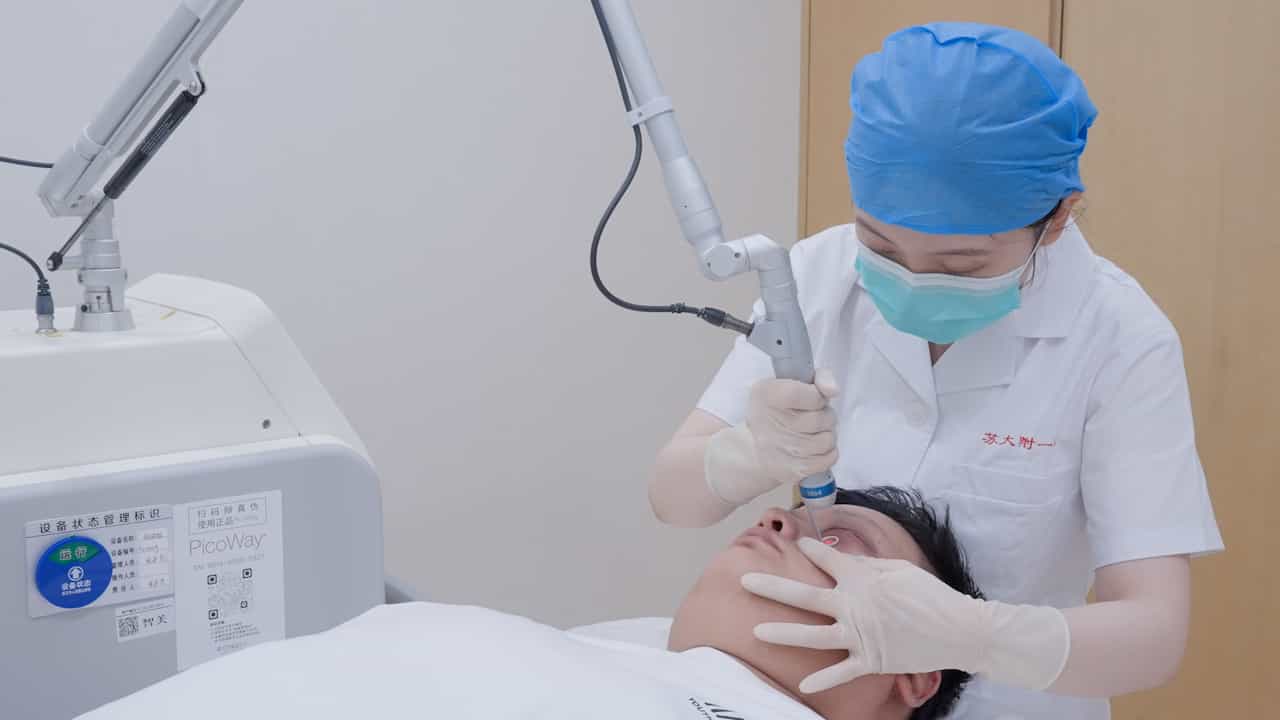

Using a 1064-nm Picosecond Neodymium-Doped Yttrium Aluminum Garnet Laser for Periorbital Hyperpigmentation
Published on: May 23, 2025
Periorbital burns – a 6 year review of management and outcome
Edmund Fitzgerald O'Connor1, Q Frew1, A Din2
1St. Andrews Centre for Burns & Plastic Surgery, Mid Essex NHS Hospitals Trust, Broomfield, Chelmsford, Essex CM1 7ET, United Kingdom; St Andrew's Anglia Ruskin (StAAR) Research Group.

Insights
Periorbital burns are rare but serious injuries. Early intervention and reconstruction are key to preserving vision and function, with most patients achieving good outcomes.
Area of Science:
- Ophthalmology
- Plastic Surgery
- Burn Management
Background:
- Periorbital burns represent infrequent yet severe injuries.
- Management focuses on restoring function and form after injury.
Purpose of the Study:
- To analyze the spectrum of periorbital burn injuries.
- To evaluate outcomes of periorbital reconstruction for function and form restoration.
Main Methods:
- Retrospective study of patients with periorbital burns (2005-2011) at a UK burns centre.
- Data collected from patient records, theatre logs, and burn databases.
- Assessment of burn characteristics, surgical interventions, and outcomes.
Main Results:
- 103 of 167 facial burn patients had eyelid burns; mean burn size 33% TBSA.
- Eyelid burn depths varied: 67% superficial partial thickness, 17% deep dermal, 16% full thickness.
- 16 patients required periorbital reconstruction (avg. 1.8 operations); 5 needed late intervention (>3 months).
Conclusions:
- Primary goals: preserve vision, prevent complications, achieve aesthetic restoration.
- Total vision loss is rare, but early ophthalmology input is crucial due to corneal damage risk.
- Timely intervention, including reconstruction, is vital for optimal patient outcomes.
Introduction:
Periorbital burns are an infrequent but potentially devastating injury. This study aimed to elucidate the spectrum of such injuries presenting to a UK burns centre and the outcome achieved in the cases requiring periorbital reconstruction for the restoration of function and form.
Methods:
Patients admitted to a UK regional burns centre between January 2005 and January 2011 with periorbital burns were identified from the Patient Administration System (PAS), theatre logs and the International Burns Injury database (IBID). Multiple parameters were assessed using patient notes, ITU and hospital image databases.
Results:
Over 6 years, 167 patients with facial burns requiring surgery were treated, including 103 patients with eyelid burns. The mean burn size was 33% total body surface area. The eyelid burn depth varied; 67% superficial partial thickness, 17% deep dermal and 16% full thickness. Two patients lost complete vision in one eye, one patient underwent amniotic membrane grafting. In total 16 patients required periorbital reconstruction to maintain eye closure, with 1.8 operations on average per patient. Acute surgery was required in 11 patients, whilst late intervention (>3 months) was needed in 5, 2 patients had both acute and delayed surgery. Of the 5 late intervention patients 4 were treated with full thickness skin grafts and 1 with a Z plasty. Average time for final reconstruction with delayed surgery was 4.5 months.
Conclusion:
The goal in management of periorbital burns is preservation of vision, prevention of future complications and restoration of an acceptable aesthetic outcome. Total visual loss is thankfully rare, but early ophthalmology intervention is vital given the evidence of corneal damage as a brief therapeutic window exists.