Related Experiment Video
Updated: Apr 20, 2026


Integrated Compensatory Responses in a Human Model of Hemorrhage
Published on: November 20, 2016
Detection of low-volume blood loss: compensatory reserve versus traditional vital signs
Camille L Stewart1, Jane Mulligan, Greg Z Grudic
1From the Department of Surgery (C.L.S., S.L.M.), School of Medicine, University of Colorado; and Flashback Technologies, Inc. (J.M., G.Z.G., S.L.M.), Boulder; and Division of Pediatric Surgery (S.L.M.), Children's Hospital of Colorado, Aurora, Colorado; and US Army Institute of Surgical Research (V.A.C.), Fort Sam Houston, San Antonio, Texas.

Background:
Humans are able to compensate for low-volume blood loss with minimal change in traditional vital signs. We hypothesized that a novel algorithm, which analyzes photoplethysmogram (PPG) wave forms to continuously estimate compensatory reserve would provide greater sensitivity and specificity to detect low-volume blood loss compared with traditional vital signs. The compensatory reserve index (CRI) is a measure of the reserve remaining to compensate for reduced central blood volume, where a CRI of 1 represents supine normovolemia and 0 represents the circulating blood volume at which hemodynamic decompensation occurs; values between 1 and 0 indicate the proportion of reserve remaining.
Methods:
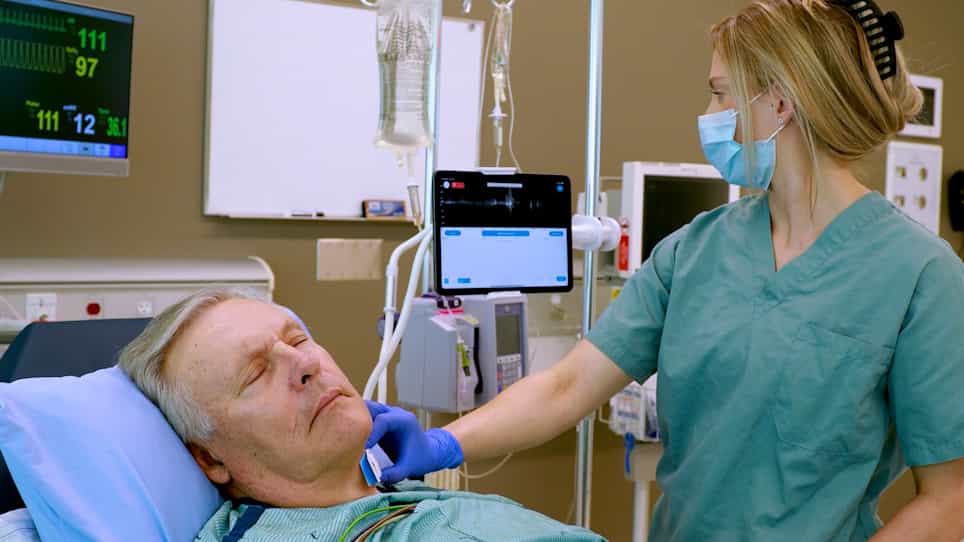
Subjects underwent voluntary donation of 1 U (approximately 450 mL) of blood. Demographic and continuous noninvasive vital sign wave form data were collected, including PPG, heart rate, systolic blood pressure, cardiac output, and stroke volume. PPG wave forms were later processed by the algorithm to estimate CRI values.
Results:
Data were collected from 244 healthy subjects (79 males and 165 females), with a mean (SD) age of 40.1 (14.2) years and mean (SD) body mass index of 25.6 (4.7). After blood donation, CRI significantly decreased in 92% (α = 0.05; 95% confidence interval [CI], 88-95%) of the subjects. With the use of a threshold decrease in CRI of 0.05 or greater for the detection of 1 U of blood loss, the receiver operating characteristic area under the curve was 0.90, with a sensitivity of 0.84 and specificity of 0.86. In comparison, systolic blood pressure (52%; 95% CI, 45-59%), heart rate (65%; 95% CI, 58-72%), cardiac output (47%; 95% CI, 40-54%), and stroke volume (74%; 95% CI, 67-80%) changed in fewer subjects, had significantly lower receiver operating characteristic area under the curve values, and significantly lower specificities for detecting the same volume of blood loss.
Conclusion:
Consistent with our hypothesis, CRI detected low-volume blood loss with significantly greater specificity than other traditional physiologic measures. These findings warrant further evaluation of the CRI algorithm in actual trauma settings.
Level Of Evidence:
Diagnostic study, level II.
Related Concept Videos
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:17
Measurement of Blood Pressure
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:30
Equipments Used To Measure Blood Pressure
This invasive approach involves cannulating a peripheral artery. During each cardiac contraction, pressure generates mechanical motion within the catheter, transmitted through rigid, fluid-filled tubing to a transducer. This transducer converts mechanical motion into electrical signals displayed as waveforms on a monitor. An automatic flushing system prevents blood backflow. Due to the potential risk of unexpected arterial blood loss, this method is primarily used in intensive...
 01:25
Introduction to Vital Signs
Vital signs help healthcare professionals assess an individual's well-being and detect any functional changes...