Related Experiment Video
Updated: Apr 20, 2026
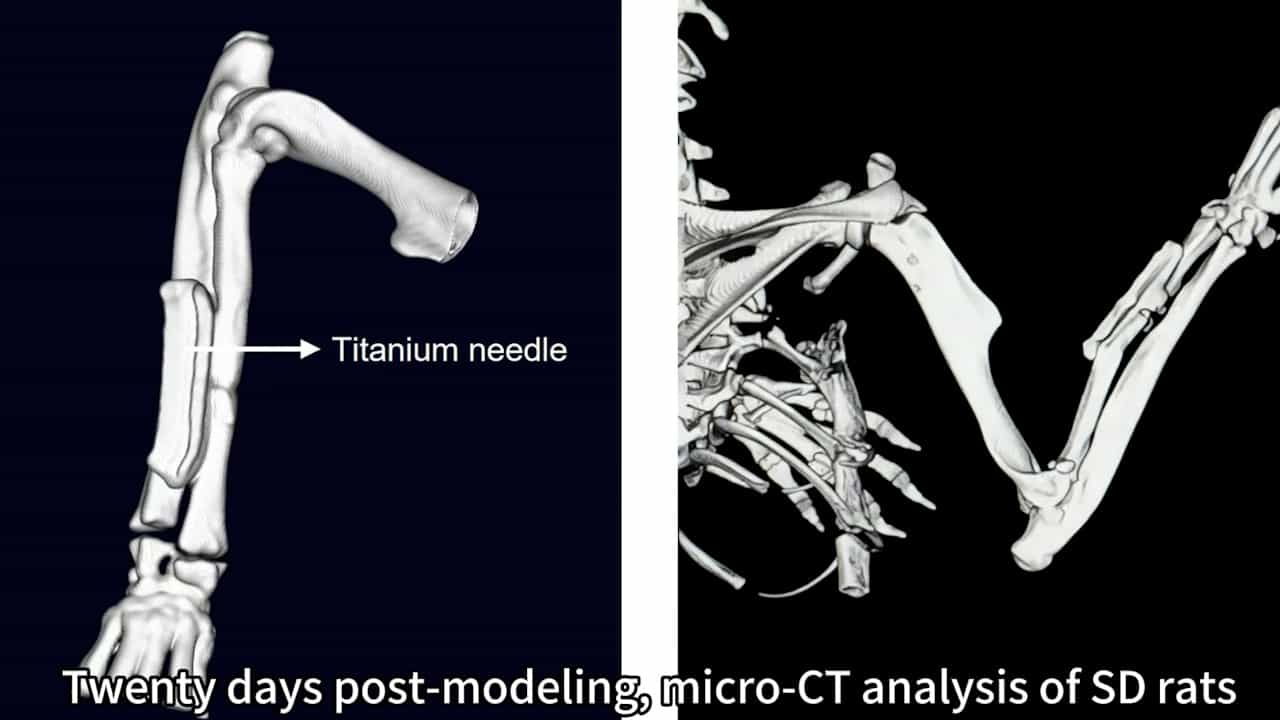
Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
[Growth behaviour after fractures of the proximal radius: differences to the rest of the skeleton]
1Kinderorthopädie, Operatives Kinderzentrum, Universitätsmedizin Göttingen, 37099, Göttingen, Deutschland, anna.hell@med.uni-goettingen.de.

Background:
Fractures of the proximal end of the radius in the growth phase have three characteristics: the head of the radius articulates with two joint partners and is therefore indispensable for an undisturbed function of the elbow. The blood supply of the proximal end of the radius is via periosteal vessels in the sense of a terminal circulation which makes it extremely vulnerable. Severe trauma caused either by accidents or treatment, can result in partial or complete necrosis with deformity of the head and neck region of the radius.
Injury Patterns:
Radioulnar synostosis and chronic epiphysiolysis are irreversible complications which can occur after excessive physiotherapy. Despite a low potency growth plate, in young patients the proximal end of the radius shows an enormous spontaneous correction of dislocations. Side to side shifts, however, will not be remodeled.
Therapy:
Therapy should be as atraumatic as possible. Due to the blood supply situation, with the appropriate indications the spontaneous correction and a brief period of immobilization without physiotherapy should be integrated into the therapy concept. If an operation is necessary, repeated traumatic repositioning maneuvers should be avoided and in case of doubt closed or careful open repositioning can be achieved with intramedullary nailing.
Conclusion:
In order to take the special characteristics of the proximal radius into consideration, the vulnerability and correction potential must be weighed up against each other. Therapy must be as atraumatic as possible. The spontaneous correction potential should be integrated into the primary therapy without overestimating this potential with respect to the extent and age of the patient.

Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:15
Bones of the Upper Limb: Ulna
 01:27
Growth of Cartilage and Bone Tissue
 01:31
Bone Remodeling and Repair