Related Experiment Video
Updated: Apr 20, 2026

Author Spotlight: Assessing the Cardiovascular Profile of Patients with Metabolic Syndrome
Published on: September 27, 2024
Carotid artery intima-media thickness measurements in the youth: reproducibility and technical considerations
Elif Seda Selamet Tierney1, Kimberlee Gauvreau2, Michael R Jaff3
1Department of Cardiology, Children's Hospital Boston, Boston, Massachusetts; Department of Pediatrics, Harvard Medical School, Boston, Massachusetts; Division of Pediatric Cardiology, Department of Pediatrics, Stanford University, Palo Alto, California.

Insights
Standardizing carotid artery intima-media thickness (CIMT) measurements in youth is crucial for cardiovascular disease research. Electrocardiographic timing improves reproducibility, highlighting the need for consistent pediatric study protocols.
Area of Science:
- Pediatric cardiovascular research
- Medical imaging analysis
- Atherosclerosis research
Background:
- Carotid artery intima-media thickness (CIMT) is a key indicator of atherosclerosis in at-risk youth.
- Standardization of CIMT measurement methodology in pediatric studies is currently limited.
- Existing pediatric studies have utilized CIMT as a primary outcome, necessitating reliable measurement techniques.
Purpose of the Study:
- To evaluate the reproducibility of CIMT measurements in children and adolescents.
- To compare two distinct CIMT measurement techniques: optimal cardiac cycle timing (Opt-CIMT) and R-wave timing (R-CIMT).
- To assess interobserver variability in CIMT measurements.
Main Methods:
- Retrospective analysis of carotid artery ultrasound studies from 184 pediatric subjects.
- CIMT measurements were performed by sonographers using Opt-CIMT and R-CIMT methods.
- Independent observers remeasured studies to assess interobserver and intraobserver reproducibility for both methods.
Main Results:
- Both Opt-CIMT and R-CIMT demonstrated excellent reproducibility (intraclass correlation coefficients > 0.85).
- R-CIMT measurements were significantly thicker than Opt-CIMT measurements in both right and left common carotid arteries (P < .001).
- Interobserver variability was high for both methods, but R-CIMT showed slightly better reproducibility for the left CCA.
Conclusions:
- Pediatric CIMT measurements exhibit excellent reproducibility when consistent methodology is applied.
- Significant variations in CIMT measurements occur throughout the cardiac cycle.
- Standardization of CIMT measurement, particularly using electrocardiographic R-wave timing, is recommended for pediatric longitudinal studies.
Background:
Carotid artery intima-media thickness (CIMT), a marker of atherosclerosis, is increased in youth at risk for future cardiovascular disease. Some pediatric studies have used CIMT as a primary outcome in clinical trials, yet data are limited on the standardization of methodology in children. The goal of this study was to evaluate reproducibility of CIMT measurements using two different measurement techniques.
Methods:
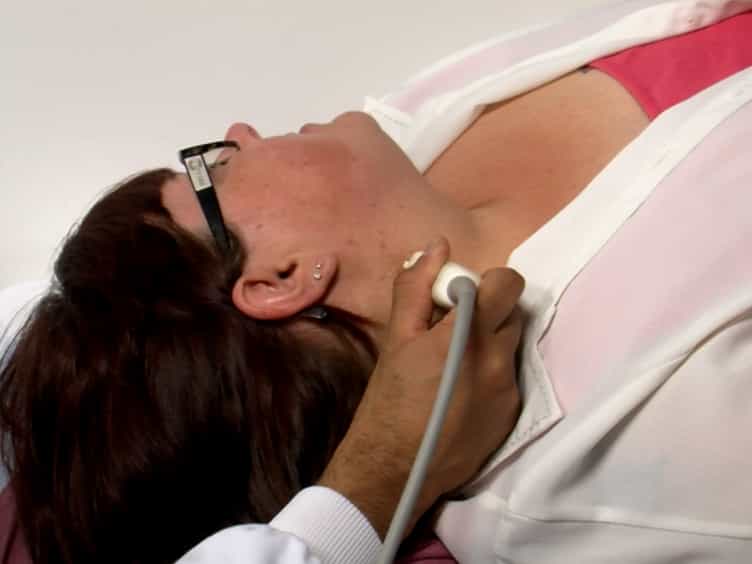
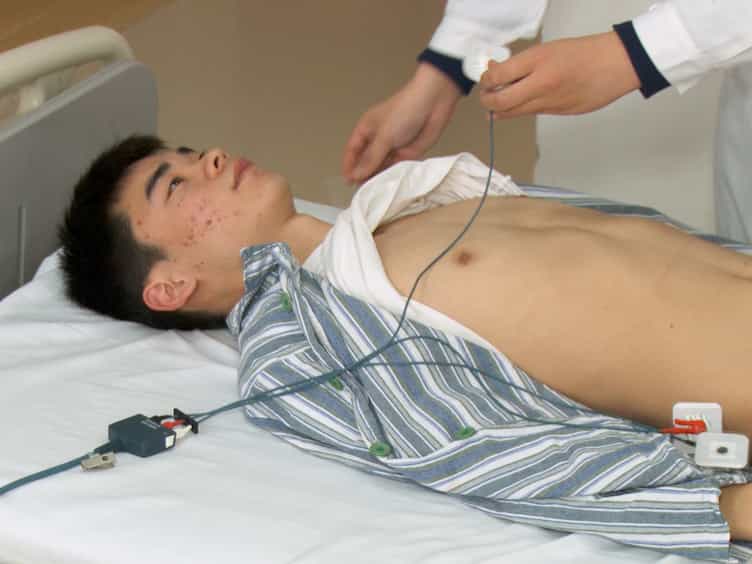
Carotid artery ultrasound studies of children and adolescents obtained as a component of a research study in Kawasaki syndrome were retrospectively analyzed. The CIMTs of both common carotid arteries (CCAs) were measured by one of two sonographers at the time in the cardiac cycle when resolution subjectively was determined to be optimal (Opt-CIMT). These sonographers blindly remeasured a random sample of studies of their own and each other's, using the same method. Another observer made CIMT measurements using exclusively frames on the R wave (R-CIMT). A fourth observer independently measured a random sample of studies twice with the R-CIMT method.
Results:
Carotid artery images from 184 subjects (mean age, 14.7 ± 2.2 years) were analyzed. The intraclass correlation coefficient for interobserver variability was 0.86 (95% confidence interval [CI], 0.69-0.94) compared with 0.85 (95% CI, 0.65-0.93) for the right and 0.86 (95% CI, 0.67-0.94) versus 0.95 (95% CI, 0.87-0.98) for the left CCA for Opt-CIMT and R-CIMT, respectively. R-CIMT was significantly thicker than Opt-CIMT (right CCA, 0.439 ± 0.030 vs 0.428 ± 0.024 mm, P < .001; left CCA, 0.446 ± 0.030 vs 0.434 ± 0.025 mm, P < .001).
Conclusion:
Pediatric CIMT measurements have excellent reproducibility when the same methodology is applied but vary significantly throughout the cardiac cycle. This report highlights the need to standardize CIMT measurements in the youth and supports the use of electrocardiographic timing, as recommended in adults, in pediatric longitudinal studies.
Related Concept Videos
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:23
Assessment of blood pressure in brachial artery(two-step method)