Related Experiment Video
Updated: Apr 20, 2026
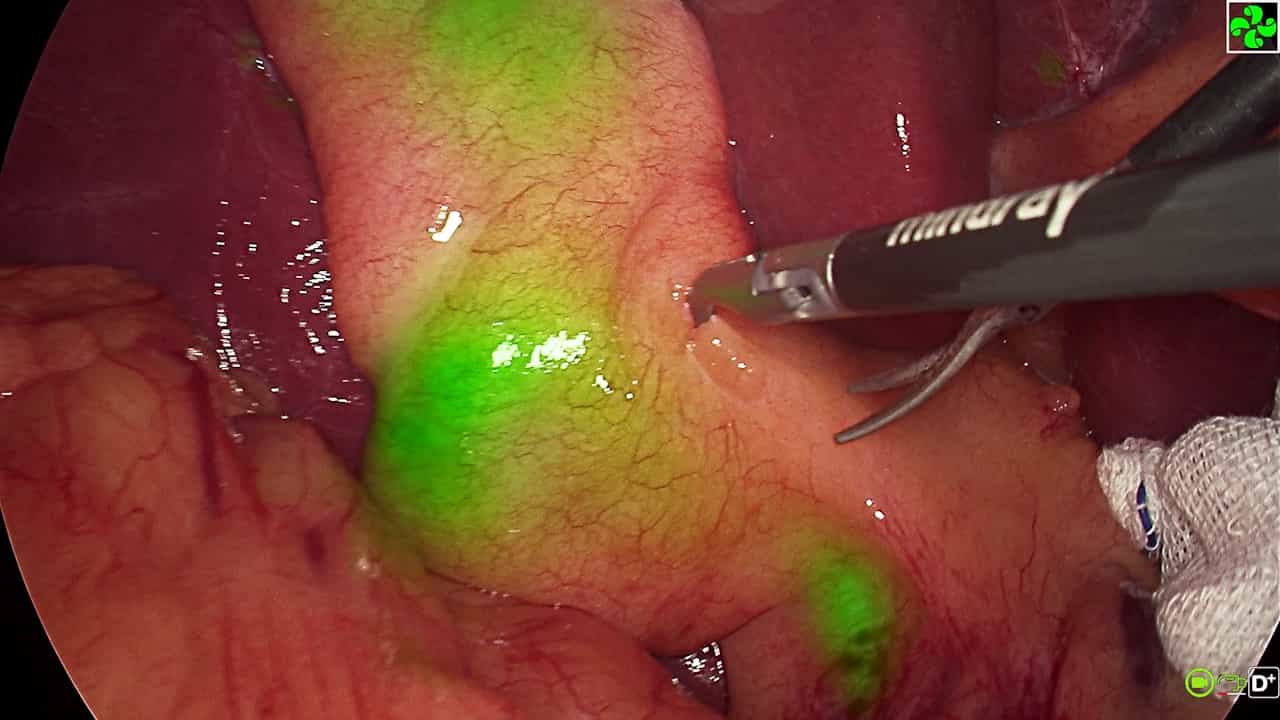

Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
Published on: November 25, 2025
Routine coagulation screening is an unnecessary step prior to ERCP in patients without biochemical evidence of
Richard J Egan1, Jonathan Nicholls, Sarah Walker
1Department of General Surgery, University Hospital of Wales, Cardiff, Wales CF14 4XW, UK. richardjohnegan@hotmail.com

Insights
Routine coagulation screening before endoscopic retrograde cholangiopancreatography (ERCP) for choledocholithiasis is often unnecessary. Only patients with elevated bilirubin or a history of bleeding require pre-procedure coagulation tests, potentially saving costs.
Area of Science:
- Gastroenterology
- Hepatology
- Clinical Diagnostics
Background:
- Current guidelines recommend coagulation screening for all patients with choledocholithiasis before ERCP.
- This practice is questioned due to the low incidence of bleeding complications related to coagulation status.
Purpose of the Study:
- To determine the incidence of abnormal coagulation in patients with choledocholithiasis undergoing ERCP.
- To assess the relationship between deranged coagulation and bleeding complications.
- To evaluate the cost-effectiveness of routine coagulation screening.
Main Methods:
- A retrospective analysis of consecutive patients undergoing ERCP at two NHS sites.
- Exclusion criteria included anticoagulation use, bleeding disorders, or incomplete data.
- Patients were stratified into jaundiced and non-jaundiced groups, with demographic, laboratory, and procedural data analyzed.
Main Results:
- Of 793 patients, elevated prothrombin time (PT) was more frequent in the jaundiced group (26.7%) compared to the non-jaundiced group (5.9%).
- Bleeding complications (5 major, 32 minor) did not differ significantly between groups.
- Only one minor bleeding complication occurred in a patient with abnormal coagulation.
Conclusions:
- Normal pre-ERCP bilirubin levels are highly sensitive (99.7%) in predicting a normal PT (<16.8s).
- Selective coagulation screening, based on bilirubin levels, can lead to significant cost savings (£14,350).
- Pre-ERCP coagulation screening should be reserved for patients with elevated bilirubin, on anticoagulation, or with a history of bleeding diathesis.
Introduction:
Guidelines suggest that all patients with choledocholithiasis should have a coagulation screen prior to endoscopic retrograde cholangiopancreatography (ERCP). This study aims to establish the incidence of deranged coagulation in such patients and its relationship with bleeding complications.
Methods:
Analysis of consecutive patients undergoing ERCP procedures at two NHS sites was undertaken. Exclusion criteria were anti-coagulation use, bleeding disorders or incomplete data. Demographic data, pre-procedure bilirubin and prothrombin time (PT), ERCP procedural information, and bleeding complications were recorded for each. The cohort was divided into jaundice and non-jaundiced groups. Statistical analysis was performed using the student's t-test, Chi-squared test and Fisher's exact test.
Results:
793 patients (419 jaundiced; 374 non-jaundiced) were included. PT was significantly higher in the jaundiced group (greater by 2 (1.35-2.64) seconds; p < 0.001). PT was prolonged in 26.7 per cent of the jaundiced group; 28 patients (6.7 per cent) had a PT of >16.8 s 5.9 per cent of the non-jaundiced group had prolonged PT, with 1 patient having a PT >16.8 s. There were 5 major, and 32 minor bleeding complications with no differences between groups. In those with abnormal coagulation, only 1 minor bleeding complication occurred in a jaundiced patient.
Discussion:
Normal pre-ERCP bilirubin was 99.7% (98.5-100) sensitive to predict a PT <16.8 s. Cost savings of £14,350 could have been achieved with judicial use of coagulation screening.
Conclusion:
Pre-ERCP coagulation screening should only be indicated in patients with a raised bilirubin or individuals on anticoagulation therapy or with a history of bleeding diathesis.