Related Experiment Video
Updated: Apr 20, 2026


Ultrasound Imaging of the Thoracic and Abdominal Aorta in Mice to Determine Aneurysm Dimensions
Published on: March 8, 2019
Determining the normal aorta size in children
Shilpa V Hegde1, Shelly Y Lensing, S Bruce Greenberg
1From the Department of Radiology, Section of Pediatric Radiology (S.V.H., S.B.G.), and Department of Biostatistics (S.Y.L.), Arkansas Children's Hospital, University of Arkansas for Medical Sciences, 1 Children's Way, Little Rock, AR 72202.

Insights
This study establishes normal effective aorta and common iliac artery diameter standards for children and young adults using CT data. These standards help identify potential aneurysms or hypoplasia in pediatric patients.
Area of Science:
- Radiology and Imaging
- Pediatric Cardiology
- Vascular Biology
Background:
- Establishing normative data for vascular structures is crucial for diagnosing conditions like aneurysms and hypoplasia.
- Computed tomography (CT) is a key imaging modality for assessing aortic dimensions.
Purpose of the Study:
- To create effective aorta diameter standards at multiple thoracic, abdominal, and common iliac artery levels.
- To develop z-score calculable standards for healthy children and young adults across a wide size range.
Main Methods:
- Retrospective analysis of 88 thoracic and 110 abdominal CT examinations in children (0-20 years).
- Effective diameter (average of anteroposterior and lateral diameters) measured by two radiologists.
- Polynomial regression models incorporating body surface area (BSA) and sex were used to establish standards.
Main Results:
- Excellent interrater reliability (correlation coefficients 0.95-0.98) was achieved.
- A polynomial regression model including linear, quadratic, and cubic BSA terms and sex best predicted effective diameter.
- Z-scores were calculated using observed and expected effective diameters and mean squared error (MSE).
Conclusions:
- Normal ranges for effective aorta and common iliac artery diameters were determined for children of varying sizes and sexes.
- Deviations from these established normal ranges may indicate aortic aneurysm or hypoplasia.
Purpose:
To establish effective aorta diameter standards at multiple levels of the thoracic aorta, abdominal aorta, and common iliac arteries by using computed tomographic (CT) data in healthy children (infants, children, adolescents) through young adults (hereafter referred to collectively as "children") of a wide range of sizes so that z scores may be calculated.
Materials And Methods:
This retrospective study was approved by the institutional review board. The effective diameter, the average of aortic anteroposterior and lateral diameters, was independently measured at multiple levels of the aorta and common iliac arteries by two radiologists using 1-mm-collimation double-oblique reconstructions. Ordinary least squares regression methods were used to investigate models with various functional forms that related effective diameters at each level to patient body surface area (BSA) and sex. The best model was selected by using R(2), and formulas for deriving the expected diameter and estimates of the mean squared error (MSE) were generated.
Results:
Results from 88 thoracic and 110 abdominal contrast material-enhanced CT examinations were analyzed in children without known cardiovascular disease who ranged in age from 0 to 20 years (mean, 9.9 years; standard deviation, 5.7), with BSA ranging from 0.19 to 2.52 m(2). Excellent interrater reliability was present (correlation coefficients ranged from 0.95 to 0.98). The best model was a polynomial regression model of the natural log transformation of the effective diameter that included linear, quadratic, and cubic BSA terms and a sex main effect as independent variables. The z scores were calculated by using the observed and expected effective diameters and the MSE.
Conclusion:
The range of normal effective diameters of the aorta at multiple levels and the common iliac arteries was determined for children of different sizes and both sexes. Measurements outside of the normal ranges are consistent with aneurysm or hypoplasia.
More Related Videos
Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:14
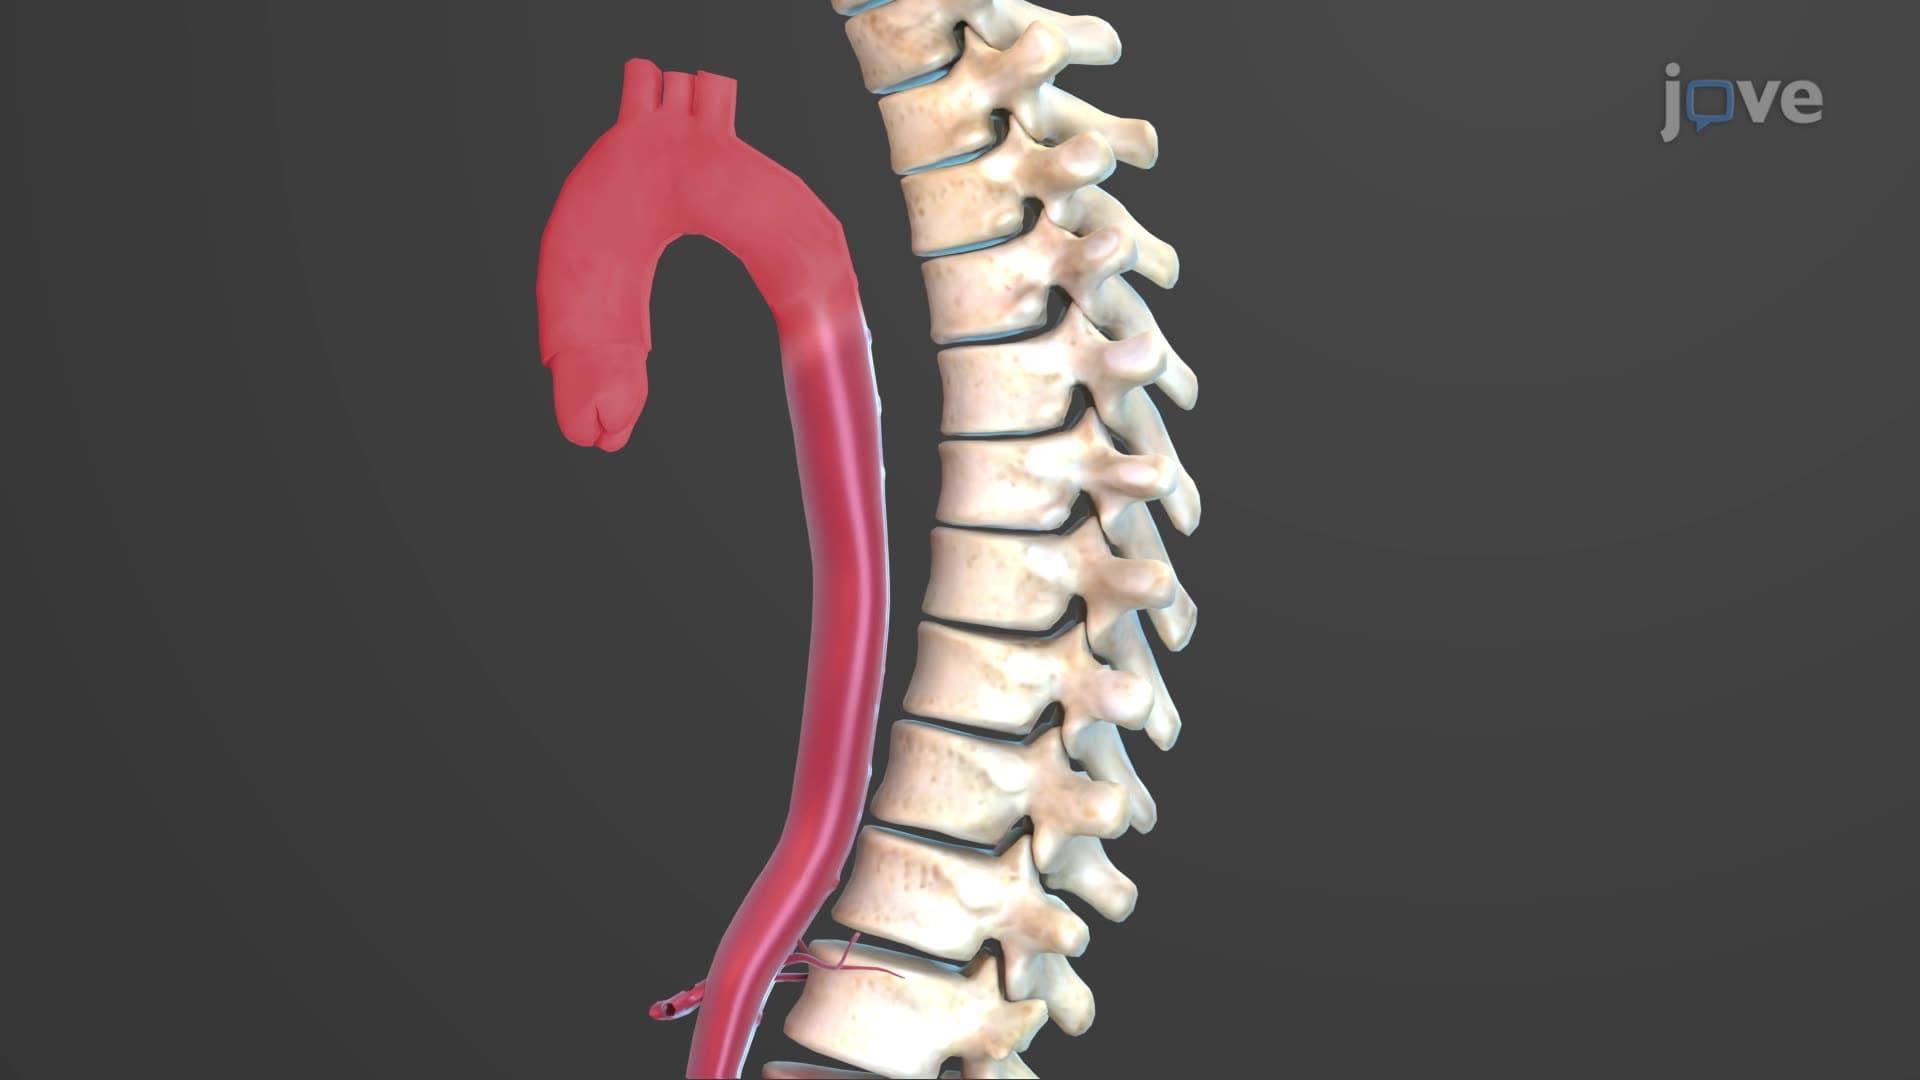
The Aorta
The average diameter of the aorta is approximately 2-3 cm, but the size can vary depending on the section of the aorta and the individual's age, sex, and body size. The aorta is...
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests