Related Experiment Video
Updated: Apr 19, 2026
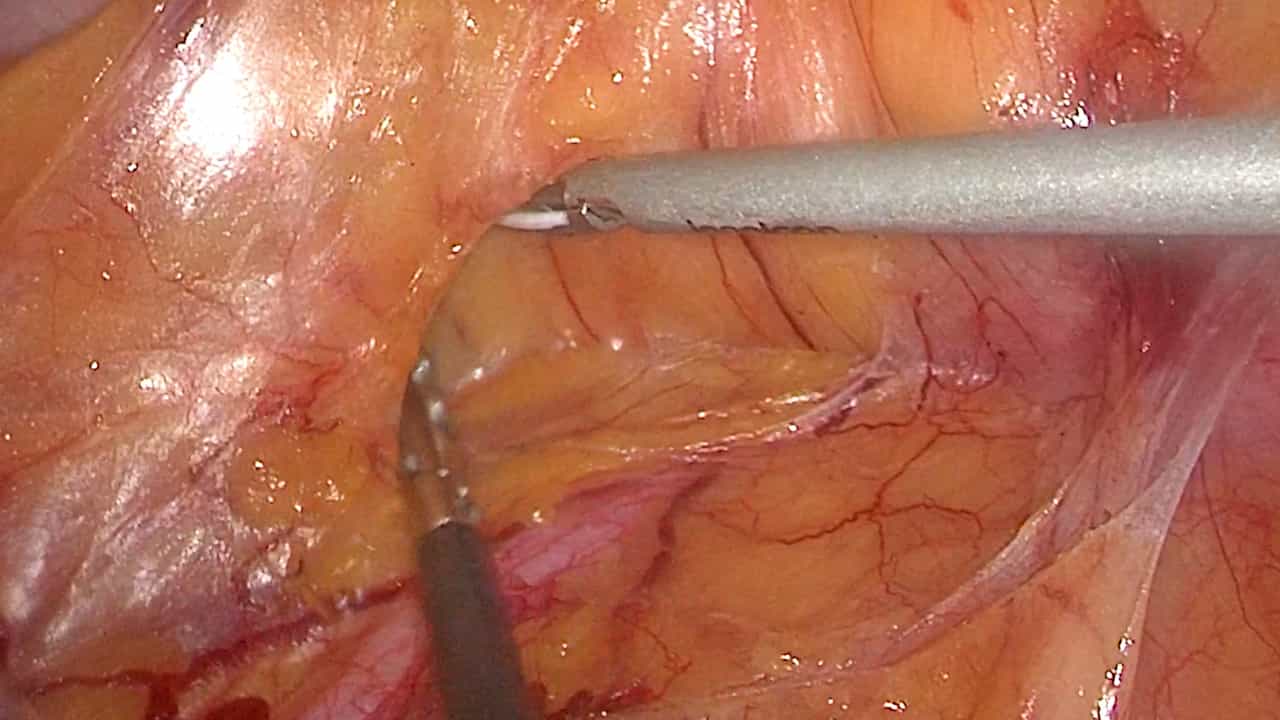

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Timing of discharge: a key to understanding the reason for readmission after colorectal surgery
Kristin N Kelly1, James C Iannuzzi, Christopher T Aquina
1Surgical Health Outcomes and Research Enterprise, Department of Surgery, University of Rochester Medical Center, 601 Elmwood Ave., Box SURG, Rochester, NY, 14642, USA, Kristin_Kelly@URMC.rochester.edu.

Purpose:
There is a growing interest in surgery regarding the balance between appropriate hospital length of stay (LOS) and prevention of unnecessary readmissions. This study examines the relationship between postoperative LOS and unplanned readmission after colorectal resection, exploring whether patients discharged earlier have different readmission risk profiles.
Methods:
Patients undergoing colorectal resection were selected by Common Procedural Terminology (CPT) code from the 2012 ACS National Surgical Quality Improvement Program (NSQIP) database. Patients were stratified by LOS quartile. Kaplan-Meier analysis was used to examine characteristics associated with 30-day unplanned readmission. Factors with a p < 0.1 were included in the Cox proportional hazards model. Subsequently, chi-square analysis compared LOS, patient, and perioperative factors with the primary reason for readmission. Factors with a p < 0.2 were included in a multivariable logistic regression for each readmission reason.
Results:
For 33,033 patients undergoing colorectal resection, the overall 30-day unplanned readmission rate was 11 %. After adjusting for patient and perioperative factors, a postoperative LOS ≥8 days was associated with a 55 % increase in the relative hazard of readmission. Patients with a ≤3-day LOS were more likely to be readmitted with ileus/obstruction (odds ratio (OR): 1.8, p = 0.001) and pain (OR: 2.2, p = 0.007). LOS was not significantly associated with readmission for intraabdominal infection or medical complications.
Conclusions:
Patients with longer LOS and complicated hospital courses continue to be high risk post-discharge, while straightforward early discharges have a different readmission risk profile. More targeted readmission prevention strategies are critical to focusing resource utilization for colorectal surgery patients.
More Related Videos
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:25
Endoscopic Procedures II: Colonoscopy
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:22
Aneurysm IV: Nursing Management
 01:31
Discharge Summary Forms
Here's a detailed look at the key components and guidelines for preparing a discharge summary:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: