Related Experiment Video
Updated: Apr 18, 2026
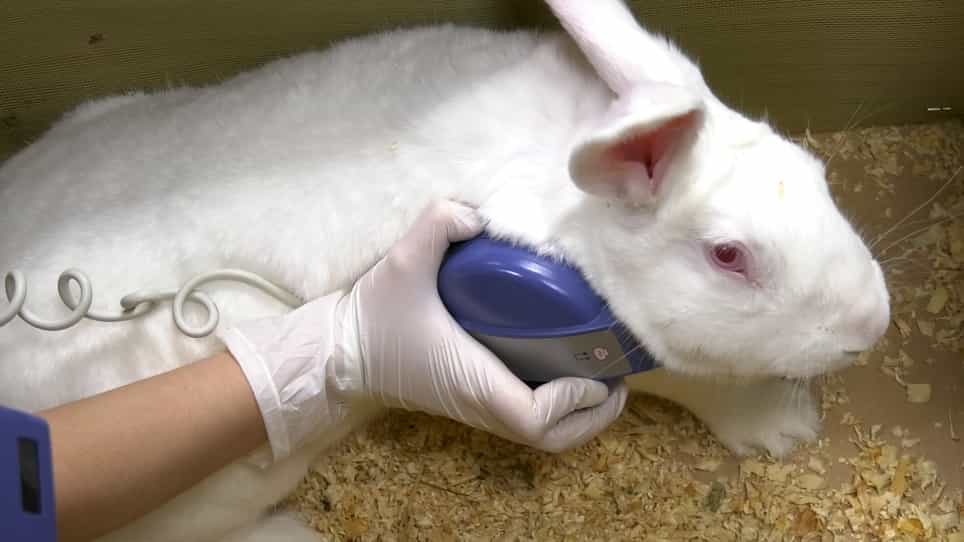

Translational Rabbit Model of Chronic Cardiac Pacing
Published on: January 6, 2023
Lead erosion in permanent pacemaker: a cumbersome complication
Bakhtawar Shah1, Zahid Aslam Awan, Zahoor Ahmed Khan
1Department of Cardiology, Hayatabad Medical Complex, Peshwar, Pakistan. drbakhtawarshah@hotmail.com

Insights
Lead erosion in pacemakers is a difficult complication. Careful three-layer lead burial during initial implantation can prevent premature device replacement.
Area of Science:
- Cardiology
- Medical Devices
- Surgical Complications
Background:
- Lead erosion is a significant complication of pacemaker implantation.
- It often necessitates premature device explantation and replacement.
- Effective prevention strategies are crucial for patient outcomes.
Purpose of the Study:
- To evaluate the incidence of lead erosion in pacemaker patients.
- To assess the effectiveness of different surgical techniques in preventing lead erosion.
- To identify an optimal method for lead implantation to minimize erosion.
Main Methods:
- A retrospective study of 415 pacemaker implantations from 2005 to 2011.
- Patients were followed regularly, with wound site inspection and device analysis.
- Surgical strategies included two-layer closure and submuscular lead burial.
Main Results:
- Three cases of lead erosion occurred during the study period.
- Two of these cases experienced recurrent erosion despite repositioning and submuscular burial.
- The implemented change strategies for lead placement proved unsuccessful in preventing recurrence.
Conclusions:
- Careful three-layer lead burial is essential for preventing pacemaker lead erosion.
- This technique involves initial muscle implantation, followed by subcutaneous placement, and skin suturing.
- Proper initial implantation technique can reduce the incidence of lead erosion and subsequent complications.
Background:
Lead erosion is one of the troublesome complications which are very difficult to treat and most of the time leads to device explanation and replacement prematurely.
Methods:
From 2005 to 2011, total 415 pacemakers were implanted in our cardiology department at Hayatabad Medical Complex Peshawar. The patients were followed regularly at six month interval or more frequently in case there were complications. At every visit we inspected the wound site, electrocardiography was done and device was analyzed with compatible programmer for the device. If there was soreness at the site of implantation, patient was seen more frequently and if there was erosion of skin, wound was reopened margin refreshed and wound closed. Initially we closed the wound in two layers after reopening but we got repeated erosion with this method and so we buried the leads sub-muscularly as change strategy which again proved unsuccessful. Results: During the six years study about 415 permanent pacemakers were implanted. During this time period, we received: three lead erosion, which were repositioned. There were recurrence in two cases and they were again subjected to procedure with a change strategy; by burying the leads in muscles, which proved unsuccessful.
Conclusion:
Leads erosion can be prevented by carefully burying leads in three layers first in muscle followed by subcutaneous tissue and then closing the wound by suturing the skin during initial implantation.

