[The relationship between pulmonary arterial and small airway inflammation in smokers with and without chronic obstructive pulmonary disease]
Related Experiment Video
Updated: Apr 18, 2026

Generation of a Chronic Obstructive Pulmonary Disease Model in Mice by Repeated Ozone Exposure
Published on: August 25, 2017
Qifang Lao1, Xiaoliang Zeng1, Xiaoning Zhong1
1Department of Respiratory Diseases, the First Affiliated Hospital of Guangxi Medical University, Nanning 530021, China.

Objective:
To investigate the relationship between pulmonary arterial and small airway inflammation in smokers with normal lung function and smokers with chronic obstructive pulmonary disease (COPD).
Methods:
Patients requiring lung resection for peripheral lung cancer were divided into group A (nonsmokers with normal lung function, n = 10), group B (smokers with normal lung function, n = 13) and group C (smokers with stable COPD, n = 10). Normal pulmonary tissue was obtained more than 5 cm away from cancer lesion. The pathomorphological changes of the pulmonary muscularized arteries (MA) and small airways were observed by HE and Victoria blue-Van Gieson's stains.Lymphocytes infiltrated in the MA and small airways were observed by immunohistochemical methods. The characteristics and the correlations between pulmonary arterial inflammation and small airway inflammation were analyzed.
Results:
The thickness of MA wall in the three groups was (119 ± 11), (139 ± 25) and (172 ± 28) µm respectively. The total small airway pathology score was (49 ± 10), (101 ± 34) and (163 ± 36) respectively. The score in group B and C was significantly higher than that in group A (P < 0.05), and the thickness of MA wall and total small airway pathology score in group C was significantly higher than that in group B (P < 0.05). The degree of CD(+)(3) T-lymphocytes and CD(+)(8) T-lymphocytes infiltration in the intima, media and adventitia of MA and epithelial layer, lamina propria and adventitia of small airway in group B and C was more significant than that in group A, especially CD(+)(8) T-lymphocytes infiltration in adventitia of MA and small airway (P < 0.05). Expression of CD(+)(4) T-lymphocytes on epithelial layer, lamina propria and adventitia of small airway in group C was higher than that in group A (P < 0.05), but the CD(+)(4)/CD(+)(8) ratio in the whole layer of airway wall declined (P < 0.01). Among three groups, the infiltration of B-lymphocytes in three layers compared each other had no statistical differences (P > 0.05). The infiltration of CD(+)(3)T-lymphocytes and CD(+)(8)T-lymphocytes in the whole layer of MA was positively correlated with the total small airway pathology score respectively (r = 0.431,0.633, P < 0.05), and the degree of CD(+)(3)T-lymphocytes and CD(+)(8)T-lymphocytes infiltration in MA showed positive correlation with that in small airway (r = 0.655,0.725, P < 0.01). The degree of CD(+)(8)T-lymphocytes infiltration in MA and small airway was positively correlated with thickness of MA (r = 0.589,0.556, P < 0.01).
Conclusions:
Both in smokers with normal lung function and smokers with stable COPD, CD(+)(8)T-lymphocytes infiltration in the whole layer of pulmonary arteries and small airways is the same kind of inflammation, mainly in the adventitia of pulmonary arteries and small airways. They are a part of pulmonary inflammation in COPD and promote the development of COPD.
More Related Videos
 09:15
Studying Effects of Cigarette Smoke on Pseudomonas Infection in Lung Epithelial Cells
Published on: May 11, 2020
 09:07
Author Spotlight: Development and Characterization of an In Vitro Model to Study Chronic Cigarette Smoke Exposure and Its Impact on Airway Epithelial Cells in COPD Research
Published on: July 12, 2024
Related Concept Videos
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
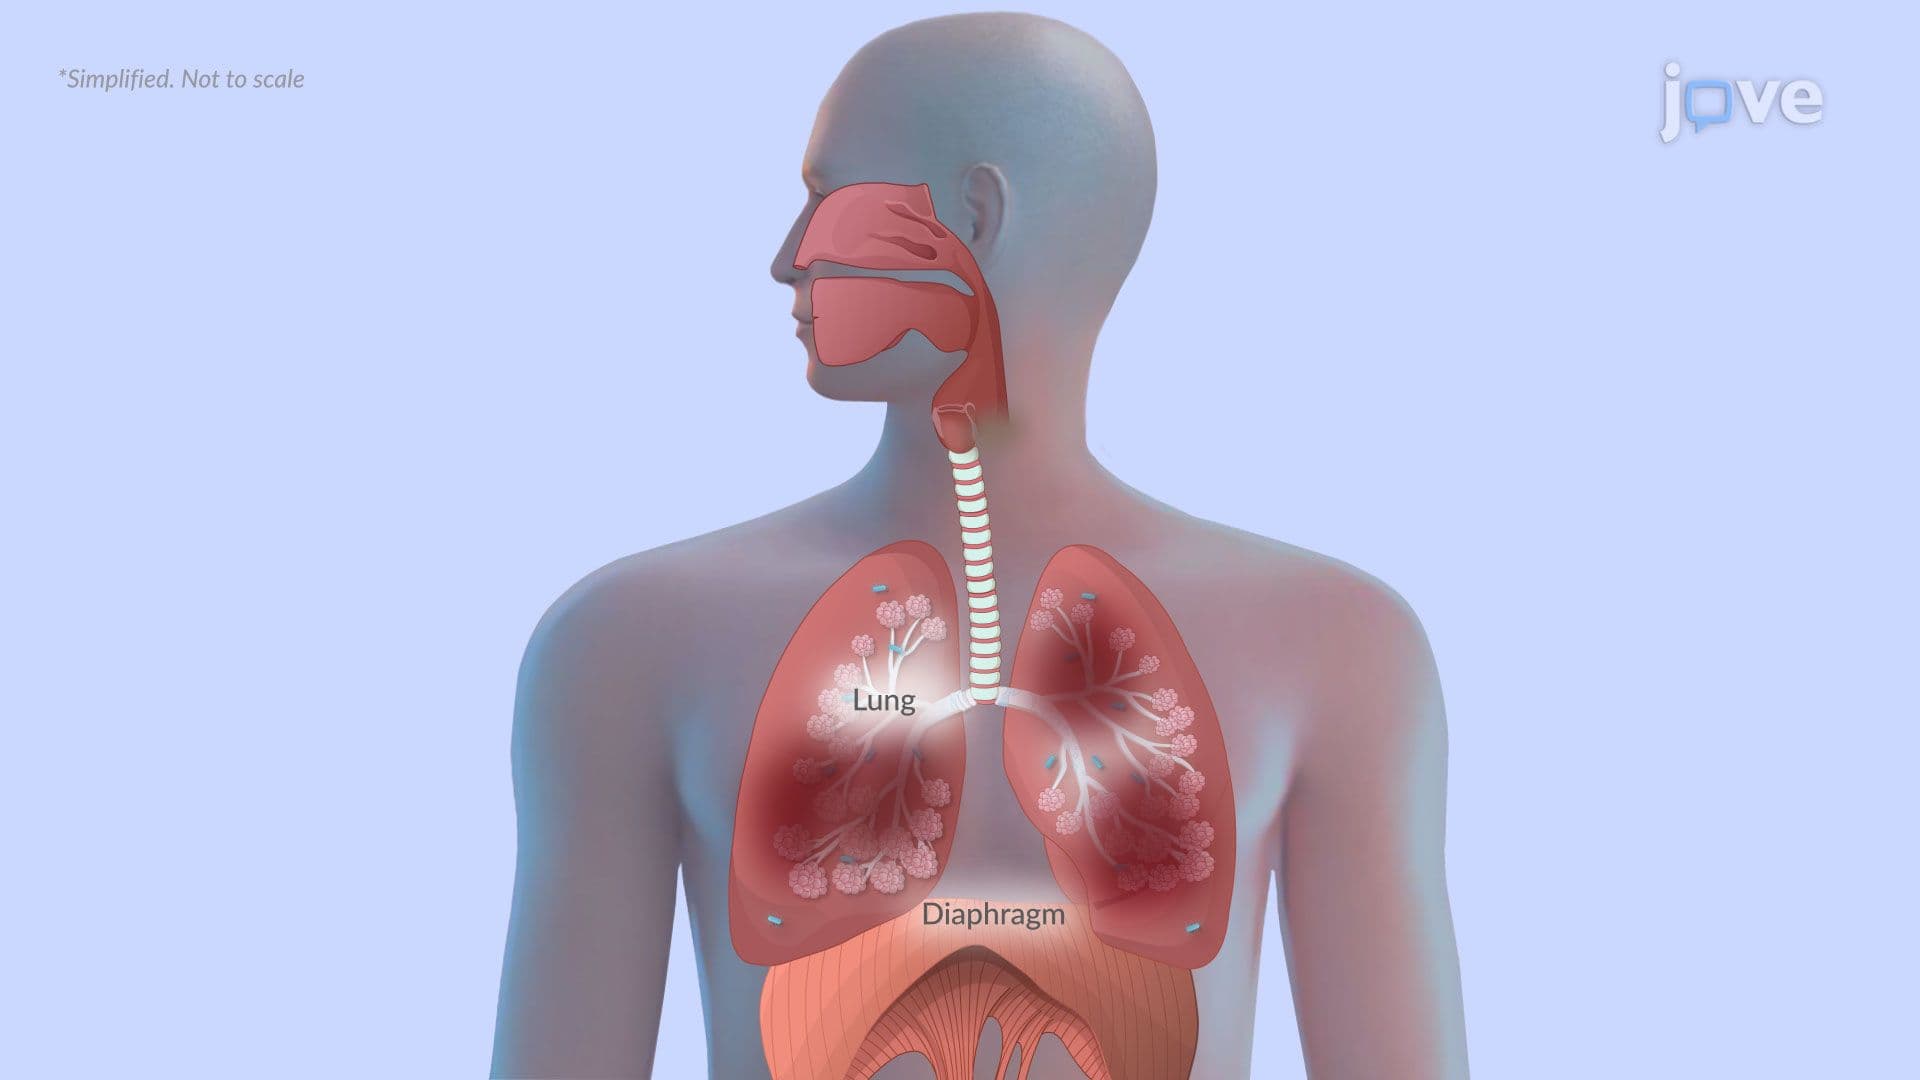
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:23
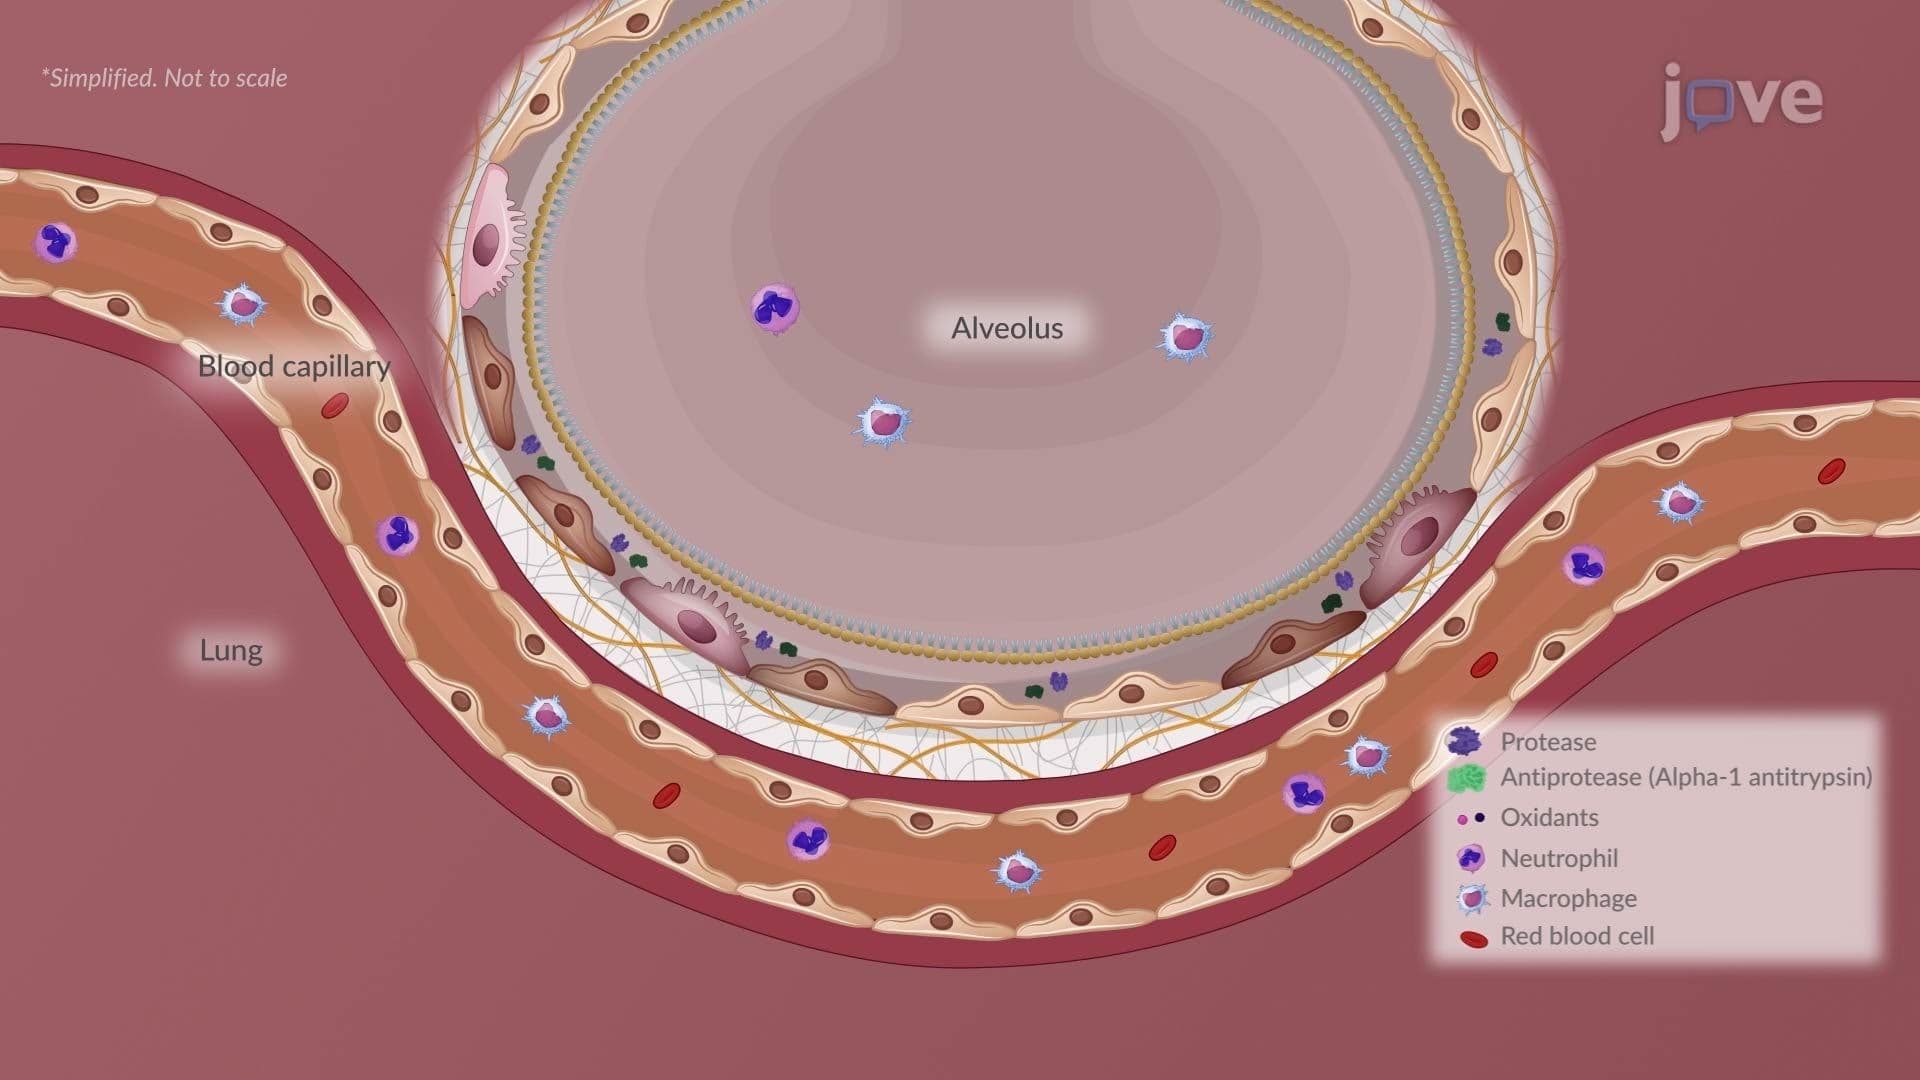
Chronic Obstructive Pulmonary Disease II: Emphysema