Related Experiment Video
Updated: Apr 17, 2026
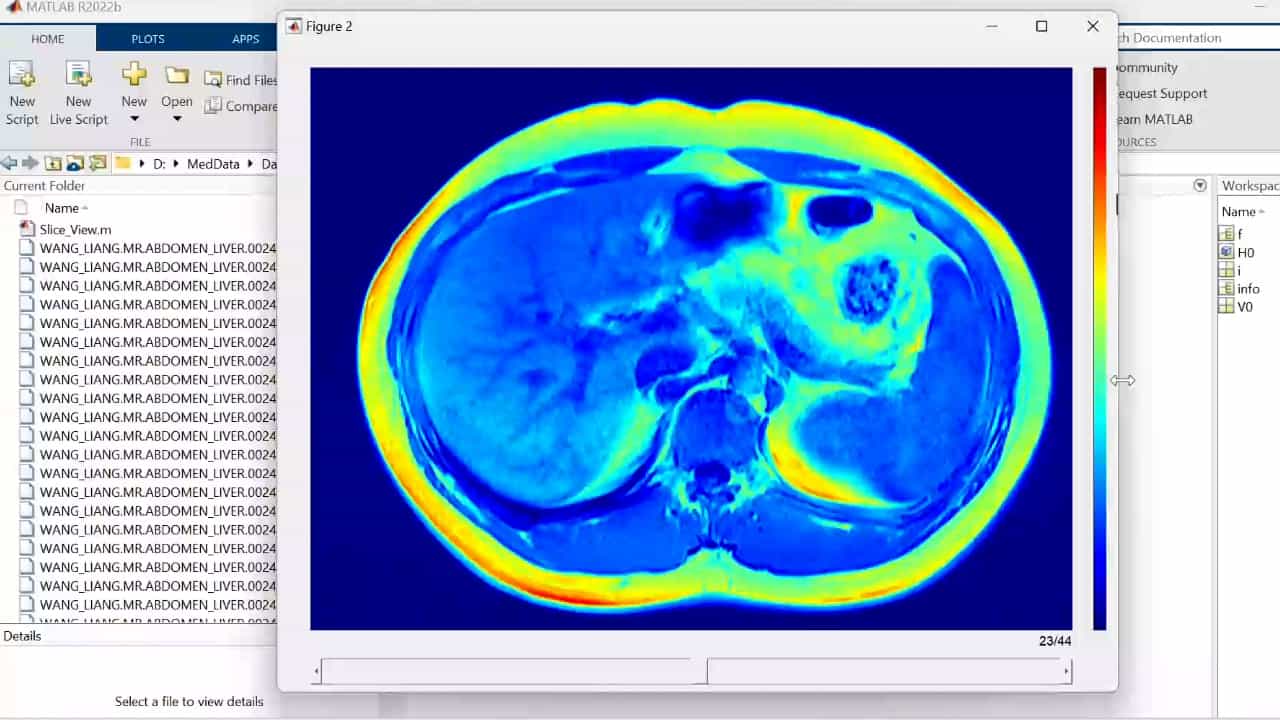

Author Spotlight: A Non-Invasive Tool to Assess and Differentiate Fat Patterns in Liver Using 3D Dixon MRI
Published on: October 20, 2023
[A multi-center clinical study of a novel controlled attenuation parameter for assessment of fatty liver]
Feng Shen1, Ruidan Zheng, Yuqiang Mi
1Department of Gastroenterology, Xinhua Hospital, Shanghai Jiaotong Univerity School of Medicine, Shanghai 200092, China.

Objective:
To evaluate the controlled attenuation parameter (CAP) assessment of fatty liver and choose a cut-off value of hepatic steatosis more than 5%.
Methods:
Consecutive patients, 18 years or older, who had undergone percutaneous liver biopsy and CAP measurement were recruited from five liver healthcare centers in China. All enrollees were categorized as hepatic steatosis grade S0 (<5%) or S1 (5%). An M-probe equipped FibroScan 502 was used to capture CAP values. Receiver operating characteristic (ROC) curves were plotted, and the areas under (AU) the curves were calculated to determine the diagnostic efficacy. The CAP cut-off values at the optimal thresholds were defined by maximum Youden indices; sensitivity and specificity were also calculated.
Results:
A total of 332 patients were enrolled in the study, including 67 patients with non-alcoholic fatty liver disease (NAFLD) and 265 with chronic hepatitis B (CHB) viru: infection. The median age (inter quartile range, IQR) of the study cohort was 39.0 (32.0-50.5) years-old. There were 46 males (68.7%) in the NAFLD group, with a median age of 37.0 (28.0-45.0) years-old, and 182 males (68.7%) in the CHB group; the differences between the two groups in median age and male: female ratio did not reach statistical significance. Multivariate linear regression analysis identified steatosis grade and body mass index (BMI) as independently associated with CAP. The median (IQR) CAP values among patients with S0 and S1 grade steatosis were 215.0 (190.0-241.0) dB/m and 294.0 (255.0-325.5) dB/m (P<0.001), respectively. For all patients, when BMI was <25 kg/m2, the ability of the AUROC of the CAP to discriminate hepatic steatosis more than or equal to 5% was 0.853, and the optimal cut-off value was 244.5 dB/m; however, when BMI≥25 kg/m2, the AUROC was 0.835 and the optimal cut-off value 269.5 dB/m.
Conclusion:
CAP can identify hepatic steatosis more than or equal to 5% and is applicable for the diagnosis of fatty liver if it is adjusted for BMI.
More Related Videos
 08:41
Novel In Vivo Micro-Computed Tomography Imaging Techniques for Assessing the Progression of Non-Alcoholic Fatty Liver Disease
Published on: March 24, 2023
 05:56
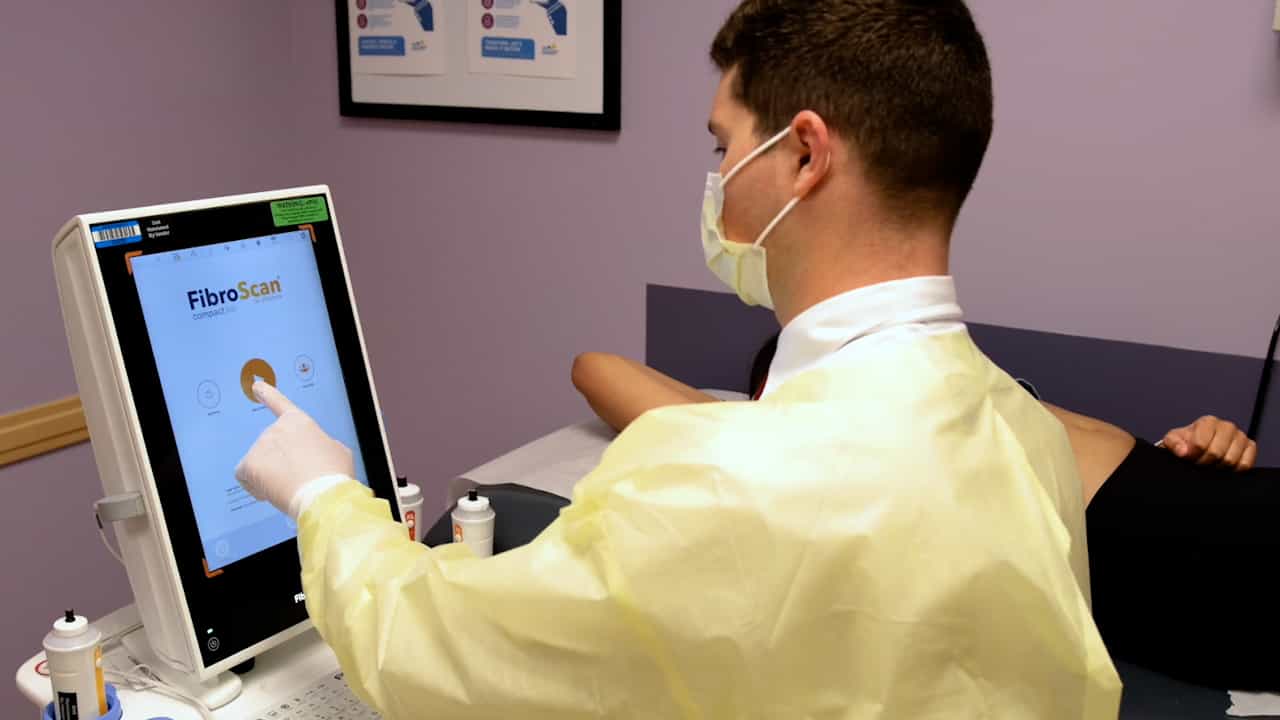
Implementation of Non-invasive Point of Care Transient Elastography for Evaluation of Liver Disease in Pediatric Populations with Cystic Fibrosis
Published on: August 29, 2025
Related Concept Videos
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test