Related Experiment Video
Updated: Apr 17, 2026
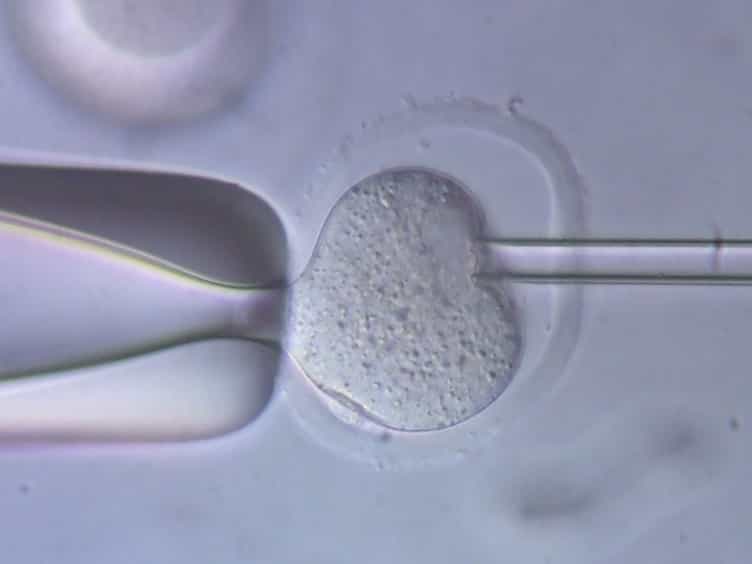
Combinational Treatment of Trichostatin A and Vitamin C Improves the Efficiency of Cloning Mice by Somatic Cell Nuclear Transfer
Published on: April 26, 2018
Trichosanthin benefits the treatment of caesarean scar pregnancies
1a Department of Gynecology and Obstetrics , International Peace Maternity & Child Health Hospital Affiliated to Shanghai Jiao Tong University School of Medicine , Shanghai , P. R. China.

This retrospective study aimed to assess the efficacy of trichosanthin (TCS) in combination with or without uterine arteries embolisation (UAE), uterine curettage and sac aspiration for the treatment of caesarean scar pregnancies (CSPs). We enrolled 200 patients at 4-17 weeks' postmenstrual age with suspected CSP. CSP was diagnosed based on serum β-human chorionic gonadotropin (β-hCG) level and transvaginal ultrasound. The patients were divided into TCS group and non-TCS group, who were treated with TCS and methotrexate, respectively, in combination with UAE and uterine curettage. TCS treatment had a success rate of 96.1% (50 of 52), similar to that in non-TCS group (98.6%, 146/148). Serum β-hCG levels on days 3, 5 and 7 in TCS group were significantly decreased. The complications were fever and pain, which were alleviated with symptomatic treatment. At follow-up, all 52 patients except one case with hysterectomy from TCS treatment group had resumed normal menstruation. In conclusion, TCS combined with bilateral UAE and uterine curettage is a safe and effective treatment for CSP, especially in patients with dangerously high serum β-hCG levels.
This retrospective study aimed to assess the efficacy of trichosanthin (TCS) in combination with or without uterine arteries embolisation (UAE), uterine curettage and sac aspiration for the treatment of caesarean scar pregnancies (CSPs). We enrolled 200 patients at 4-17 weeks' postmenstrual age with suspected CSP. CSP was diagnosed based on serum β-human chorionic gonadotropin (β-hCG) level and transvaginal ultrasound. The patients were divided into TCS group and non-TCS group, who were treated with TCS and methotrexate, respectively, in combination with UAE and uterine curettage. TCS treatment had a success rate of 96.1% (50 of 52), similar to that in non-TCS group (98.6%, 146/148). Serum β-hCG levels on days 3, 5 and 7 in TCS group were significantly decreased. The complications were fever and pain, which were alleviated with symptomatic treatment. At follow-up, all 52 patients except one case with hysterectomy from TCS treatment group had resumed normal menstruation. In conclusion, TCS combined with bilateral UAE and uterine curettage is a safe and effective treatment for CSP, especially in patients with dangerously high serum β-hCG levels.
Related Concept Videos
 01:27
Acne Infection
 01:19
Clinical Applications of Epidermal Stem Cells