Related Experiment Video
Updated: Apr 17, 2026

Detection and Quantification of Calcitonin Gene-Related Peptide CGRP in Human Plasma Using a Modified Enzyme-Linked Immunosorbent Assay
Published on: June 16, 2023
[Use of procalcitonin as diagnostic marker in acute gastroenteritis]

Insights
Procalcitonin (PCT) and C-reactive protein (CRP) are elevated in bacterial gastroenteritis, but do not predict hospitalization. These markers can help differentiate bacterial from nonbacterial causes in children.
Area of Science:
- Pediatric Gastroenterology
- Infectious Diseases
- Clinical Diagnostics
Background:
- Distinguishing bacterial from nonbacterial acute gastroenteritis (AGE) in children lacks reliable hematological markers.
- Procalcitonin (PCT) is investigated as a potential biomarker for bacterial AGE.
Purpose of the Study:
- To evaluate procalcitonin (PCT) as a marker for bacterial AGE in children.
- To analyze the relationship between PCT, C-reactive protein (CRP), and hospital admission probability.
Main Methods:
- Prospective study of 45 children diagnosed with AGE in an emergency room setting.
- Analysis of epidemiological, clinical, and analytical variables, including blood and stool samples.
- Exclusion of patients with chronic digestive disease, prolonged diarrhea, immunodeficiency, or prior antibiotic treatment.
Main Results:
- Children with bacterial AGE were older and had higher median PCT and CRP levels (p=0.001).
- Optimal discrimination values were PCT ≥0.05 mg/L and CRP ≥3 mg/dL.
- No significant association was found between elevated PCT or CRP and increased hospitalization probability.
Conclusions:
- Procalcitonin (PCT) and C-reactive protein (CRP) are elevated in bacterial gastroenteritis.
- Neither PCT nor CRP reliably predicts the likelihood of hospitalization in pediatric AGE.
Introduction:
There is no hematological marker that reliably differentiates between bacterial and nonbacterial acute gastroenteritis (AGE). The objective of this study is to evaluate procalcitonin (PCT) as a marker for bacterial AGE and analyze its relationship with hospital admission.
Patients And Method:
A prospective study of children diagnosed with AGE was conducted at the emergency room during a period of seven months, which required blood and stool samples. Epidemiological, clinical and analytical variables were analyzed. Patients with chronic digestive disease, prolonged diarrhea, immunodeficiency or prior antibiotic treatment were excluded. The study was approved by the Ethics Committee and an informed consent was requested.
Results:
45 patients were analyzed. Children with bacterial GEA were older (p=0.027) and presented higher median PCT and C-reactive protein concentrations (CRP) (p=0.001). The PCT and CRP values that best discriminated bacterial infection were PCT≥0.05 mg/L (sensibility 64.3%, specificity 83.9%, positive probability coefficient (PPC): 4), and CRP≥3 mg/dL (sensibility 78.6%, specificity 90.3%, PPC: 8). No association between the elevation of these markers and higher hospitalization probability was found.
Conclusion:
Procalcitonin, like CRP, is elevated in bacterial gastroenteritis (p=0.001), but these markers are not a predictor of hospitalization.

Related Concept Videos
 00:51
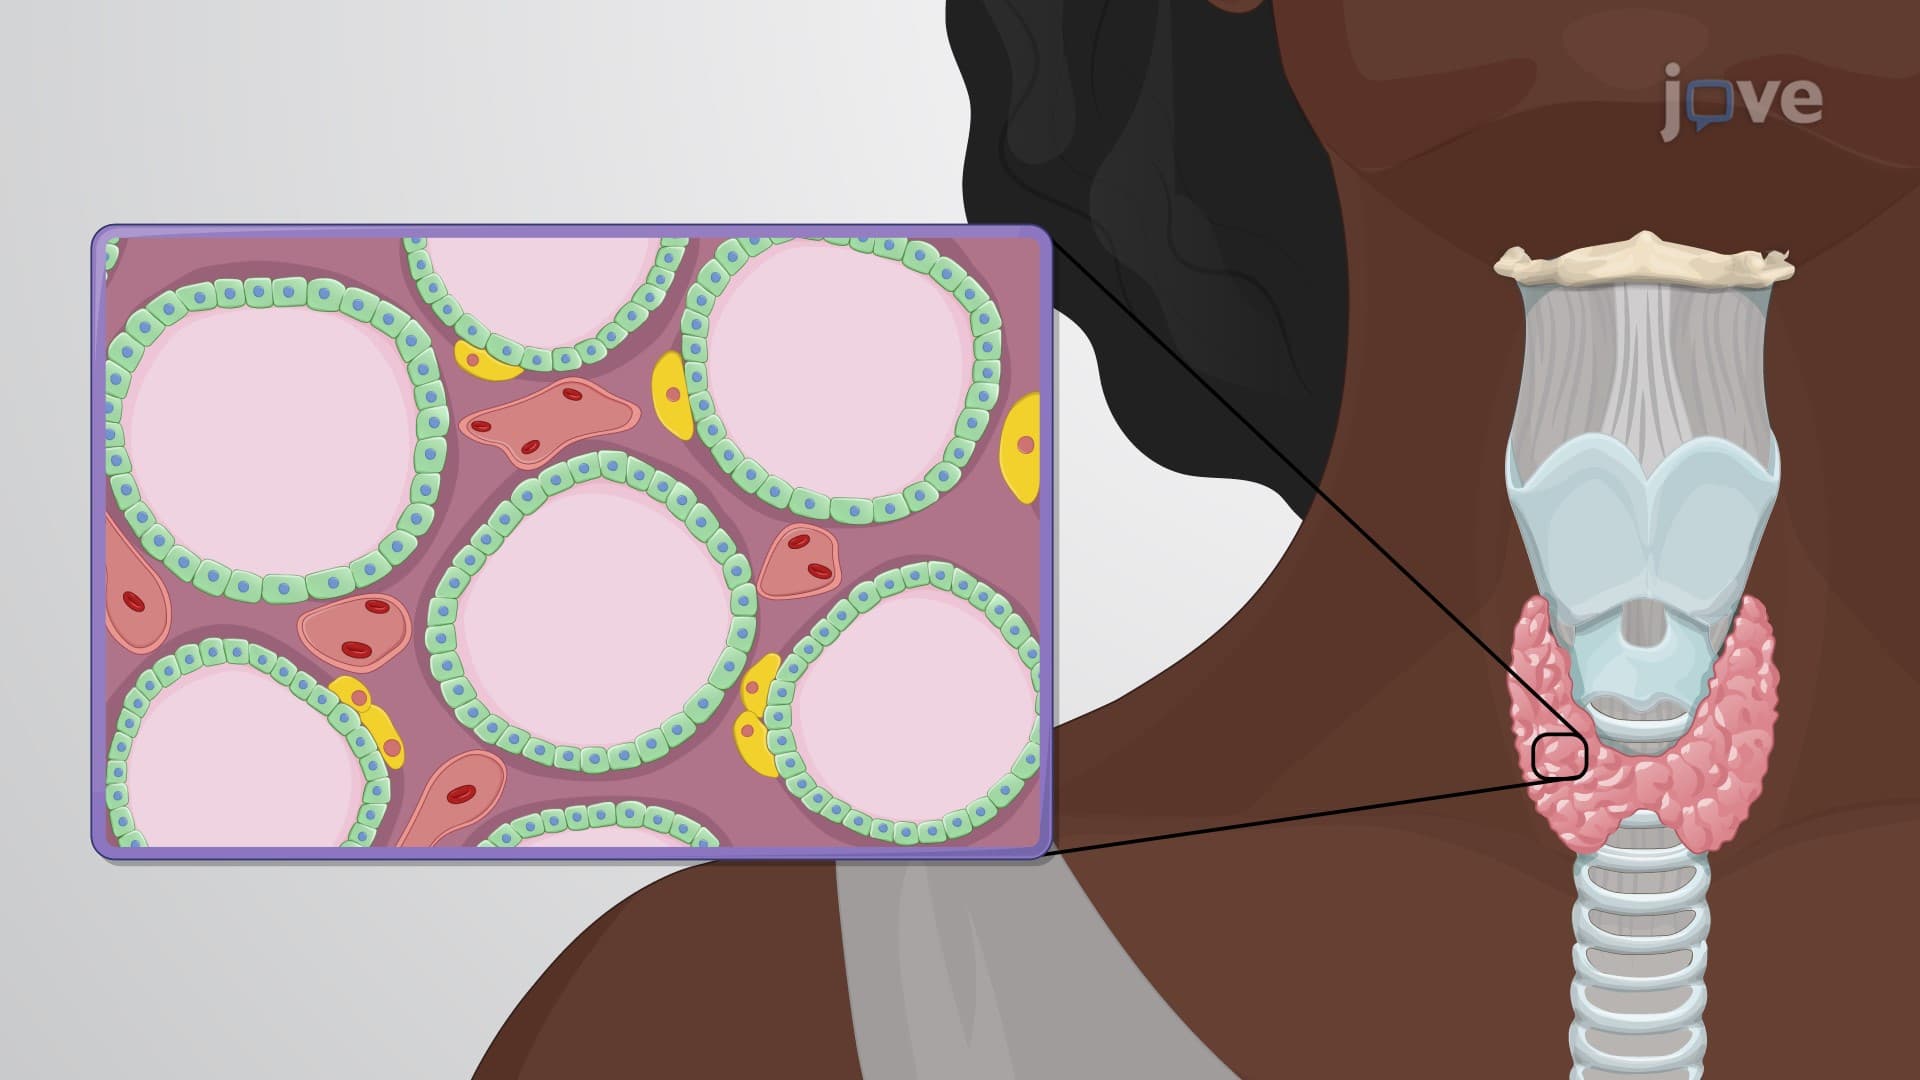
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:30
Serum Laboratory Studies, Stool Test, Breath Test
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.