Related Experiment Video
Updated: Apr 15, 2026

A Neonatal Imaging Model of Gram-Negative Bacterial Sepsis
Published on: August 12, 2020
Lack of Accuracy of Biomarkers and Physical Examination to Detect Bacterial Infection in Febrile Infants
Marta Germán Díaz1, Rosa Pavo García, Daniel Blázquez Gamero
1From the Pediatrics Department, 12 de Octubre University Hospital, Madrid, Spain.

Insights
Procalcitonin (PCT) shows promise in diagnosing invasive bacterial infections (IBI) in febrile infants under 3 months. However, combining PCT with other markers and physical exams may improve diagnostic accuracy for IBI in infants.
Area of Science:
- Pediatrics
- Infectious Diseases
- Diagnostic Medicine
Background:
- Fever without source (FWS) in infants younger than 3 months necessitates accurate diagnosis of invasive bacterial infections (IBI).
- Evaluating diagnostic markers like physical examination, C-reactive protein (CRP), procalcitonin (PCT), white blood cell (WBC) count, and absolute neutrophils counts (ANCs) is crucial.
Purpose of the Study:
- To assess the diagnostic utility of physical examination and laboratory markers for IBIs and potentially serious bacterial infections in febrile infants under 3 months.
- To compare the performance of PCT, CRP, WBC, and ANC in diagnosing IBIs in this vulnerable population.
Main Methods:
- A retrospective study analyzed data from 318 infants younger than 3 months presenting with FWS.
- Diagnostic performance was evaluated using receiver operating characteristic (ROC) curve analysis.
- Sensitivity, specificity, and likelihood ratios were calculated for each diagnostic test.
Main Results:
- Invasive bacterial infections were diagnosed in 3.5% of infants (11 bacteremia, 76 UTIs).
- Procalcitonin (PCT) demonstrated the highest area under the curve (0.77) for detecting IBI, outperforming CRP, ANC, and WBC.
- For potentially serious bacterial infections, PCT, CRP, and WBC showed similar diagnostic performance (AUCs ranging from 0.66 to 0.68).
Conclusions:
- Procalcitonin (PCT) is a more effective biomarker than CRP, WBC, and ANC for ruling in or out IBIs in febrile infants under 3 months.
- Despite its utility, PCT alone could not identify all infants with IBI, with nearly 30% missed.
- Combining analytical parameters and physical examination findings is recommended to enhance the reliability of IBI diagnosis in infants.
Objectives:
The aim of this study was to analyze the usefulness of physical examination, C-reactive protein (CRP), procalcitonin (PCT), white blood cell (WBC) count, and absolute neutrophils counts (ANCs) for the diagnosis of invasive bacterial infections (IBIs) and potentially serious bacterial infections in infants younger than the age of 3 months presenting with fever without source (FWS) to the emergency department (ED).
Methods:
A descriptive retrospective study that includes all infants aged younger than 3 months who presented with FWS to the ED between July 2008 and January 2012. We evaluated diagnostic performance for each test by receiver operating characteristic curve analysis. Sensitivity, specificity, positive likelihood ratio, and negative likelihood ratio were also calculated.
Results:
Three hundred eighteen patients met the inclusion criteria. Eleven bacteremia (3.5%) and 76 urinary tract infections (23.9%) were diagnosed. To detect IBI, the areas under the curve for the different tests were as follows: PCT, 0.77 (95% confidence interval [CI], 0.57-0.96); CRP, 0.54 (95% CI, 0.36-0.73); ANC, 0.53 (95% CI, 0.34-0.71); and WBC, 0.42 (0.24-0.61). To detect potentially serious bacterial infections, the areas under the curve were as follows: PCT, 0.66 (95% CI, 0.59-0.74); CRP, 0.68 (0.60-0.76); ANC, 0.64 (0.56-0.71); and WBC, 0.66 (0.58-0.72).
Conclusions:
Procalcitonin is better than CRP, WBC, and ANC to confirm or dismiss the presence of an IBI in infants aged younger than 3 months presenting with FWS to the ED. However, it could not identify almost 30% of infants with IBI. Most patients diagnosed with IBI (10 of 11) presented abnormal values in at least one of the analytical parameters and/or physical appearance. Four of 5 patients with IBI and well appearing presented abnormal results in at least one of the analytical parameters. Therefore, the development of tools combining different tests including the new biomarkers could increase the reliability of the tests for the diagnosis of IBI in these patients.
More Related Videos

Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:14
Temperature Measurement Sites
Oral: When assessing oral temperature, the thermometer tip should be placed under the tongue in the posterior sublingual pocket. It offers accurate readings and can be...
 01:30
Serum Laboratory Studies, Stool Test, Breath Test
 01:28
Methods of Classification and Identification
 01:27
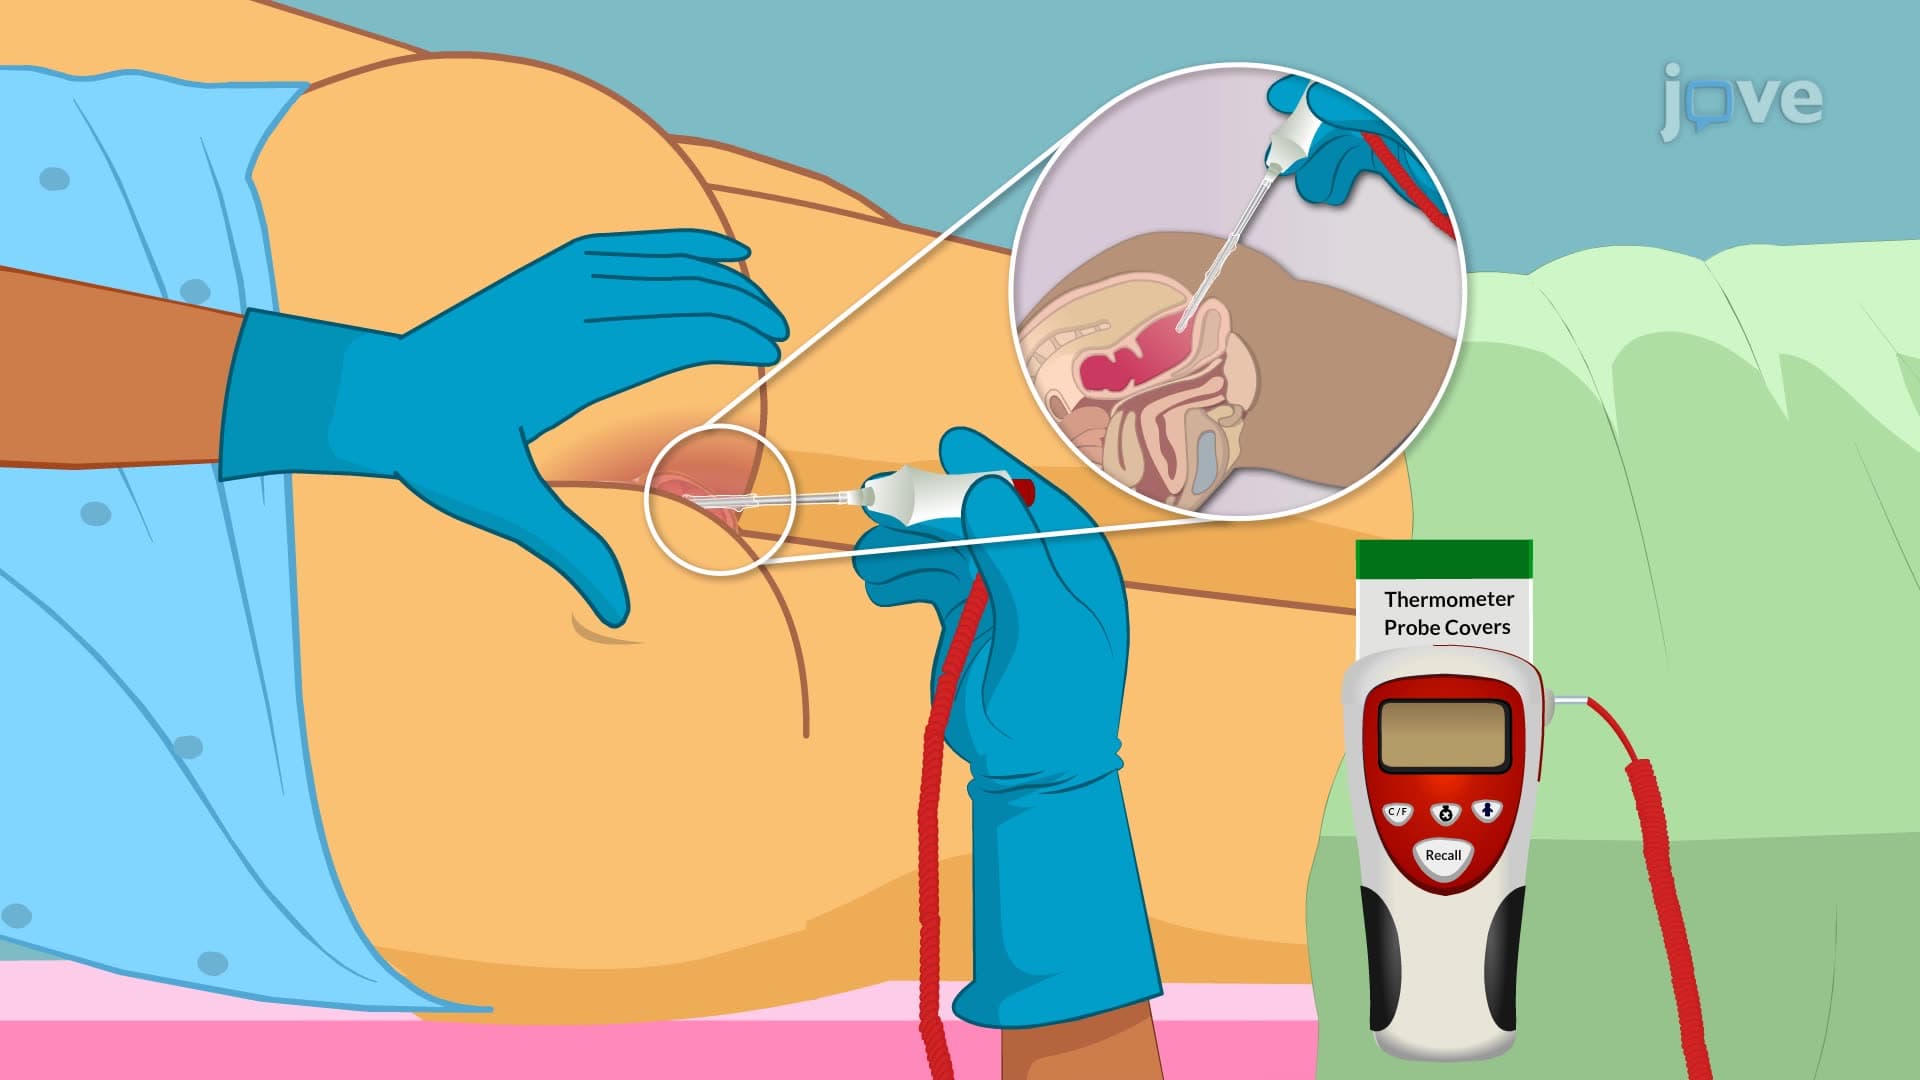
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:13
Equipments Used to Measure Body Temperature
Glass-bulb Thermometer:
Glass-bulb thermometers are hollow glass tubes with a bulb tip containing liquid such as ethanol or mercury. Historically, glass bulb mercury thermometers were the standard device to measure body temperature. Today, mercury thermometers are prohibited in many countries due to the hazardous effects of mercury and the risk of exposure if the glass bulb breaks. In general,...